Related Experiment Video
Updated: Oct 7, 2025
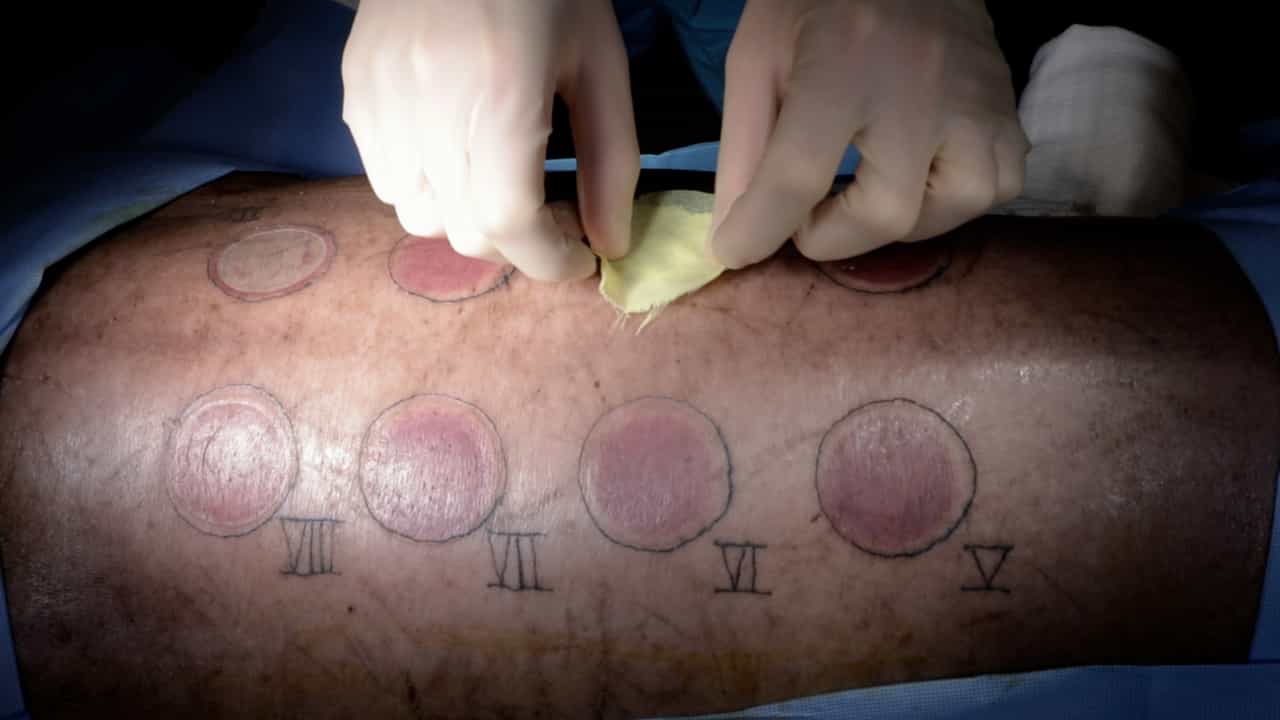

Author Spotlight: A Multi-Depth Porcine Model for Comprehensive Study of Burn Injuries and Healing Processes
Published on: February 23, 2024
[Preliminary discussion on the prevention and treatment of shock after severe burns]
1Department of Burns and Plastic Surgery, the Fourth Medical Center of PLA General Hospital, Beijing 100048, China.

Abstract:
Shock is one of the most common complications and one of the main causes of death after severe burns. The prevention and treatment of shock runs through the whole process of severe burn treatment. Shocks after severe burns, based on their causes, are mainly classified as follows: hypovolemic shock characterized by elevated hematocrit, also known as burn shock, and caused by serious leakage of intravascular fluid to body surface and interstitial spaces in the early stage of burns; hemorrhagic shock caused by large scale of incision and tension reduction, gastrointestinal stress ulcer, or large area of escharectomy and tangential excision surgery; septic shock caused by various microbial invasion; anaphylactic shock caused by infusion of drugs or blood. From the perspective of the reduction of effective circulating volume, burn shock and hemorrhagic shock are hypovolemic shocks, and septic shock and anaphylactic shock are vasodilatory shocks. As the aforementioned shocks vary in terms of occurrence timing, occurrence mechanism, and clinical manifestations, individualized strategies should be adopted for the prevention and treatment.

Related Concept Videos
 01:22
Burn Injuries
The damage results in the death of skin cells, which can lead to a massive loss of fluid. Dehydration, electrolyte imbalance, and renal and circulatory failure follow, which can be fatal. Burn patients are treated with intravenous fluids to offset...
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:22
Methods of reducing fever
Pharmacological Methods of Reducing Fever:
 01:28
Acute Coronary Syndrome IV: Interprofessional Care