Related Experiment Video
Updated: Oct 6, 2025
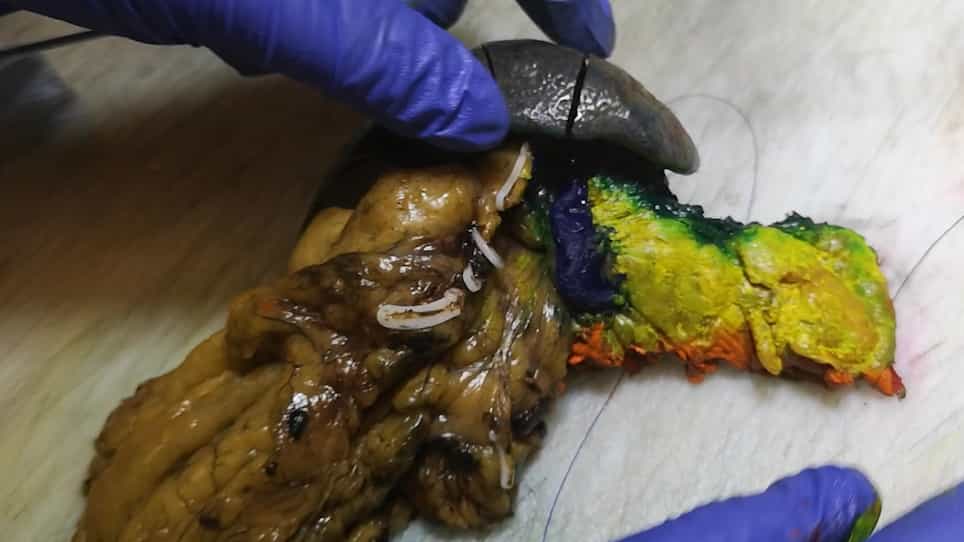

DIPLOMA Approach for Standardized Pathology Assessment of Distal Pancreatectomy Specimens
Published on: February 1, 2020
Iterative Changes in Risk-Stratified Pancreatectomy Clinical Pathways and Accelerated Discharge After
Andrew D Newton1, Timothy E Newhook1, Morgan L Bruno1
1Department of Surgical Oncology, The University of Texas MD Anderson Cancer Center, 1400 Pressler Street, Unit 1484, Houston, TX, 77030, USA.

Background:
Previous implementation of risk-stratified pancreatectomy clinical pathways (RSPCPs) decreased length of stay (LOS) following pancreaticoduodenectomy (PD). This study's primary aim was to measure the association of iterative RSPCP revisions with accelerated discharge and early postoperative outcomes.
Methods:
This is a retrospective cohort study of a prospectively maintained surgical database (10/2016-9/2020). In February 2019, revised RSPCPs were implemented with earlier nasogastric tube (NGT) removal (postoperative day [POD] 1 for low risk; POD 2 for high risk) and updated drain fluid amylase cutoffs for POD 1/POD 3 removal. Perioperative outcomes between original and revised pathways were compared. Predictors of accelerated discharge (defined as ≤ POD 5 for low risk; ≤ POD 6 for high risk) were identified.
Results:
There were 233 (36% high risk) patients in original and 131 (32% high risk) in revised RSPCPs. After revision, the rate of POD 1 NGT removal was higher while POD ≤ 3 drain removal was similar. Median LOS decreased for low risk (5 vs. 6 days, p = 0.011) and high risk (6 vs. 9 days, p = 0.005) with no increase in delayed gastric emptying, postoperative pancreatic fistula, or readmissions. With POD 1 NGT removal, diet tolerance was earlier without increased NGT reinsertions. In low-risk patients, younger age, POD 1 NGT removal, and POD ≤ 3 drain removal were independent predictors of accelerated discharge. In high-risk patients, POD 1 NGT removal and POD ≤ 3 drain removal were independent predictors of accelerated discharge.
Conclusions:
Following iterative revisions in RSPCPs, LOS after PD decreased further without increasing readmissions, and NGTs were removed earlier without increased reinsertions. Early NGT and drain removal are modifiable practices within RSPCPs that are associated with accelerated discharge.
Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management