Related Experiment Video
Updated: Oct 6, 2025

Autologous Microfractured and Purified Adipose Tissue for Arthroscopic Management of Osteochondral Lesions of the Talus
Published on: January 23, 2018
Talus Visualization in Ankle Fractures: How Much Are We Really Seeing?
Nathaniel B Hinckley1, Jeffrey D Hassebrock1, Phillip J Karsen1
1Department of Orthopaedic Surgery, Mayo Clinic Arizona, Phoenix, Arizona, USA.

Background:
Despite appropriate care, a subset of patients with ankle fractures has persistent pain. This condition may be associated with intra-articular pathology, which is present up to 65% of the time.
Purpose:
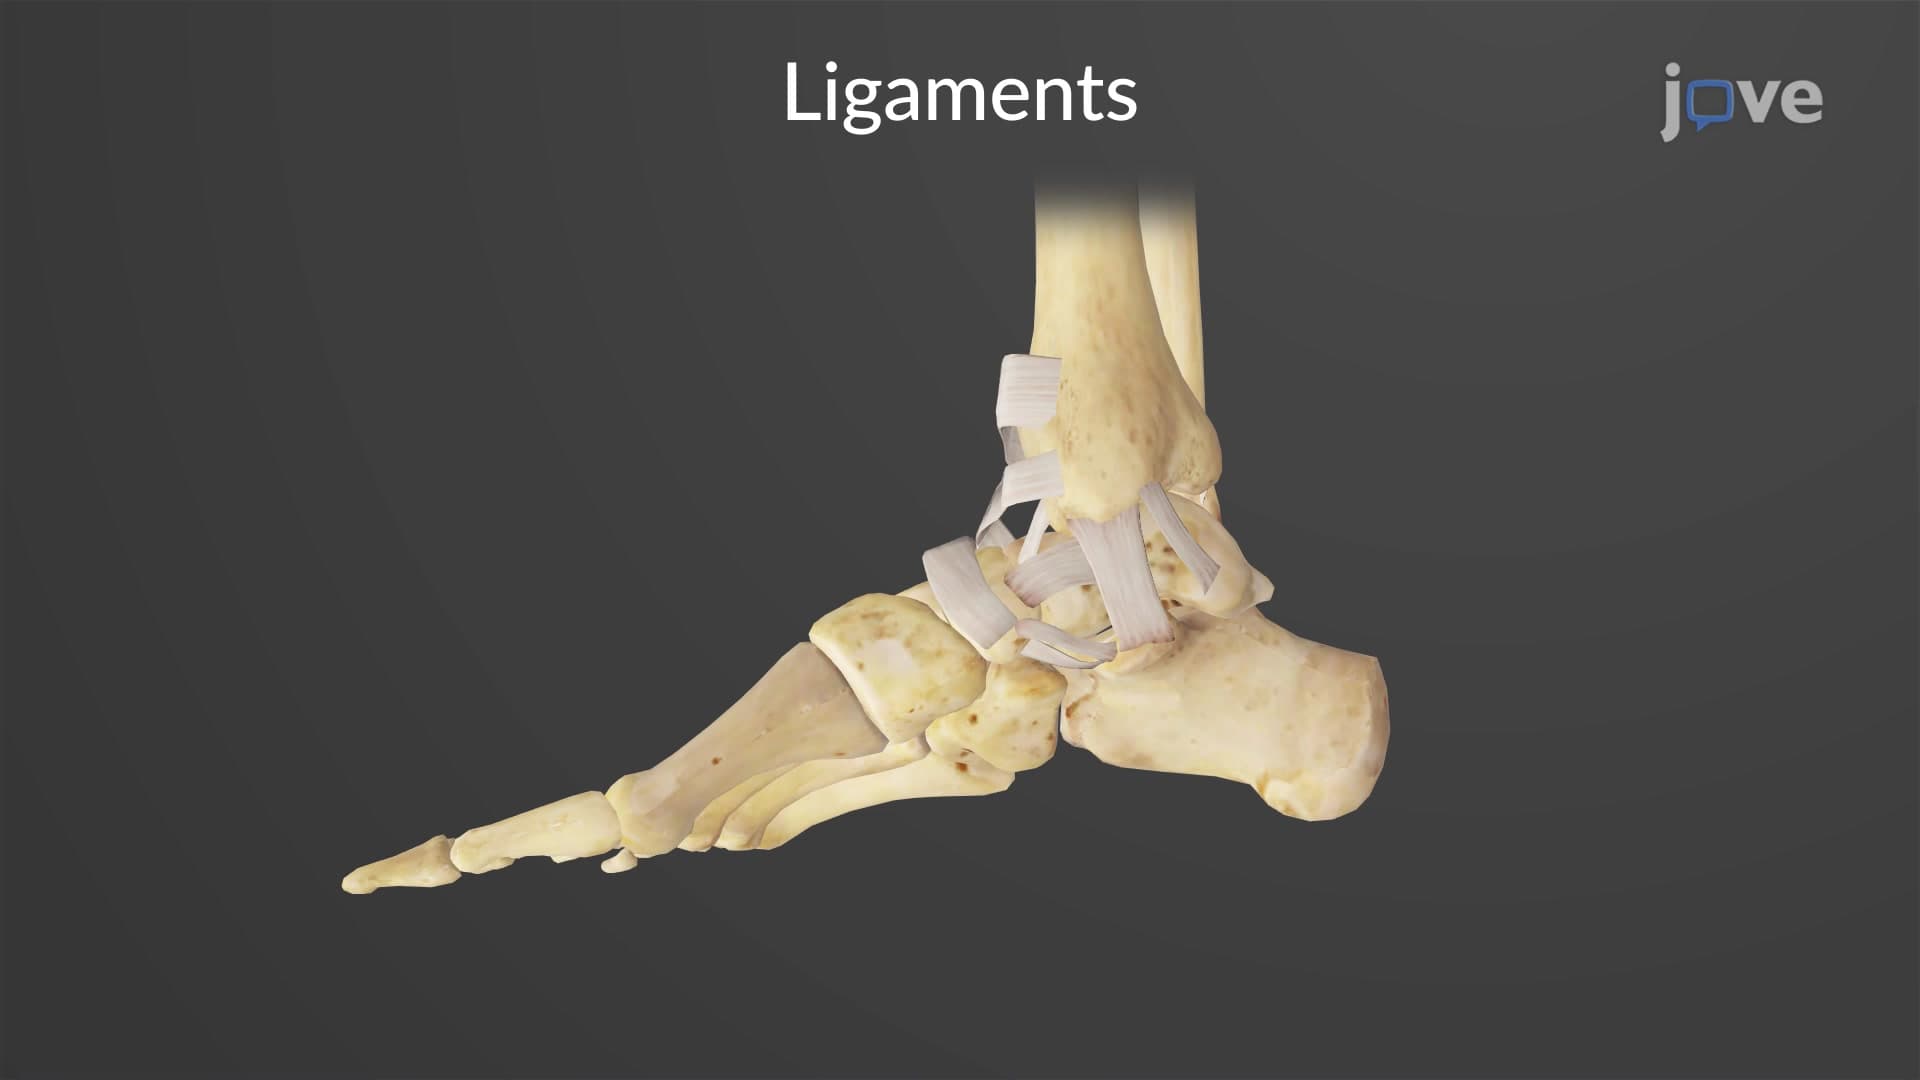
To quantify how much of the talus is visible through an open approach to a standard supination external rotation bimalleolar ankle fracture as a percentage of the entire weightbearing surface of the talus.
Study Design:
Descriptive laboratory study.
Methods:
Standard ankle approaches to lateral and medial malleolar fractures were performed in 4 cadaveric ankles from 2 cadavers. Osteotomies were made to simulate a supination external rotation bimalleolar ankle fracture based on the Lauge-Hansen classification. The visible segments of talar cartilage were removed. The tali were then exhumed, and the entire weightbearing superior portion of the talus was assessed and compared with the amount of cartilage removed by an open approach. The mean of the data points as well as the 95% confidence interval were calculated.
Results:
Four ankle specimens from 2 cadavers were used for these measurements. The mean surface area of the talus was 14.0 cm2 (95% CI, 13.3-14.7 cm2), while the mean area visible via an open approach was 2.1 cm2 (95% CI, 0.5-3.6 cm2). The mean proportion of the talus visualized via an open approach was 14.8% (95% CI, 3.6-26.1%).
Conclusion:
These findings indicate that the true area of weightbearing talar surface visible during an open exposure may be less than what many surgeons postulate.
Clinical Relevance:
Only a small fracture of the talus is visible via an open approach to the talus during fracture fixation. This could warrant arthroscopic evaluation of these injuries to evaluate and treat osteocondral lesions resulting from ankle fractures.