Artificial intelligence prediction of cholecystectomy operative course from automated identification of gallbladder
Thomas M Ward1, Daniel A Hashimoto2, Yutong Ban2,3
1Surgical Artificial Intelligence and Innovation Laboratory, Department of Surgery, Massachusetts General Hospital, 15 Parkman St., WAC 460, Boston, MA, 02114, USA. tmward@mgh.harvard.edu.

Background:
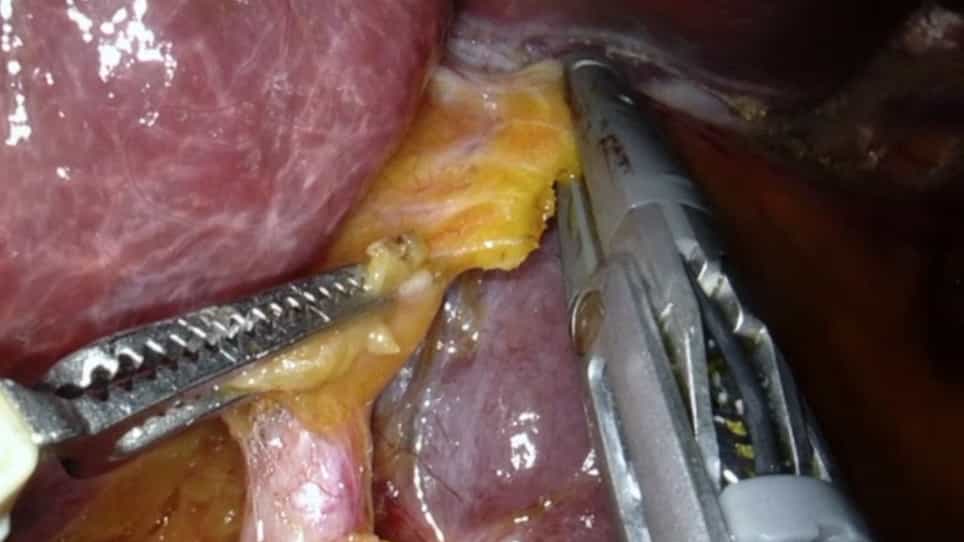
Operative courses of laparoscopic cholecystectomies vary widely due to differing pathologies. Efforts to assess intra-operative difficulty include the Parkland grading scale (PGS), which scores inflammation from the initial view of the gallbladder on a 1-5 scale. We investigated the impact of PGS on intra-operative outcomes, including laparoscopic duration, attainment of the critical view of safety (CVS), and gallbladder injury. We additionally trained an artificial intelligence (AI) model to identify PGS.
Methods:
One surgeon labeled surgical phases, PGS, CVS attainment, and gallbladder injury in 200 cholecystectomy videos. We used multilevel Bayesian regression models to analyze the PGS's effect on intra-operative outcomes. We trained AI models to identify PGS from an initial view of the gallbladder and compared model performance to annotations by a second surgeon.
Results:
Slightly inflamed gallbladders (PGS-2) minimally increased duration, adding 2.7 [95% compatibility interval (CI) 0.3-7.0] minutes to an operation. This contrasted with maximally inflamed gallbladders (PGS-5), where on average 16.9 (95% CI 4.4-33.9) minutes were added, with 31.3 (95% CI 8.0-67.5) minutes added for the most affected surgeon. Inadvertent gallbladder injury occurred in 25% of cases, with a minimal increase in gallbladder injury observed with added inflammation. However, up to a 28% (95% CI - 2, 63) increase in probability of a gallbladder hole during PGS-5 cases was observed for some surgeons. Inflammation had no substantial effect on whether or not a surgeon attained the CVS. An AI model could reliably (Krippendorff's α = 0.71, 95% CI 0.65-0.77) quantify inflammation when compared to a second surgeon (α = 0.82, 95% CI 0.75-0.87).
Conclusions:
An AI model can identify the degree of gallbladder inflammation, which is predictive of cholecystectomy intra-operative course. This automated assessment could be useful for operating room workflow optimization and for targeted per-surgeon and per-resident feedback to accelerate acquisition of operative skills.