Related Experiment Video
Updated: Oct 6, 2025

Insertion, Maintenance, and Removal of the Percutaneous Dual Lumen Cannula Right Ventricular Assist Device
Published on: July 20, 2022
Perks and Pitfalls of Performance-Linked Reimbursement for Novel Drugs: The Case of Sacubitril-Valsartan
Alexander T Sandhu1,2, Paul A Heidenreich1,2, John Lin3
1Department of Medicine (A.T.S., P.A.H., J.P.), Stanford University, CA.

Background:
Rising drug costs have increased interest in performance-linked reimbursement (PLR) contracts that tie payment to patient outcomes. PLR is theoretically attractive to payers interested in reducing the risk of overpaying for expensive drugs, to manufacturers working to improve early drug adoption, and to patients seeking improved access. Multiple PLR contracts were developed for sacubitril-valsartan. We evaluated how the characteristics of a PLR contract influence its performance.
Methods:
We used a published cost-effectiveness model of sacubitril-valsartan. We evaluated hypothetical PLR contracts that adjusted drug payment based on observed therapy effectiveness. Ideally, these contracts reduce the uncertainty around the value obtained with purchasing sacubitril-valsartan. By reducing the financial risk in covering an ineffective therapy, PLR incentivizes insurers to increase patient access. We measured the uncertainty in value as the SD of the incremental net monetary benefit (INMB), an estimate of therapy value incorporating costs and clinical benefits. We evaluated the change in INMB SD under a variety of different assumptions regarding contract design, therapy effectiveness, and population characteristics.
Results:
Over 2 years, sacubitril-valsartan led to 0.042 additional quality-adjusted life-years at an incremental cost of $4916. Using a willingness-to-pay of $150 000 per quality-adjusted life-year, this led to a mean INMB across simulations of $1416 (SD, $1720). A PLR contract that adjusted payment based on cardiovascular mortality reduced the INMB SD moderately by 20.7% while a contract based on all-cause mortality was more effective (INMB SD reduction of 27.3%). A contract based on heart failure hospitalization reduction was ineffective. PLR effectiveness increased with greater uncertainty regarding therapy effectiveness or in sicker cohorts (eg, New York Heart Association Class III/IV heart failure). Contracts required precise estimates of treatment effect in addition to trust or verifiability between manufacturers and payers concerning patient selection.
Conclusions:
The development of accurate prospective estimates of treatment effectiveness using actual enrollee characteristics will be critical for successful PLR. If able to meet these requirements, PLRs could incentivize insurers to expand access to expensive treatments by reducing financial risk.
More Related Videos

Related Concept Videos
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:06
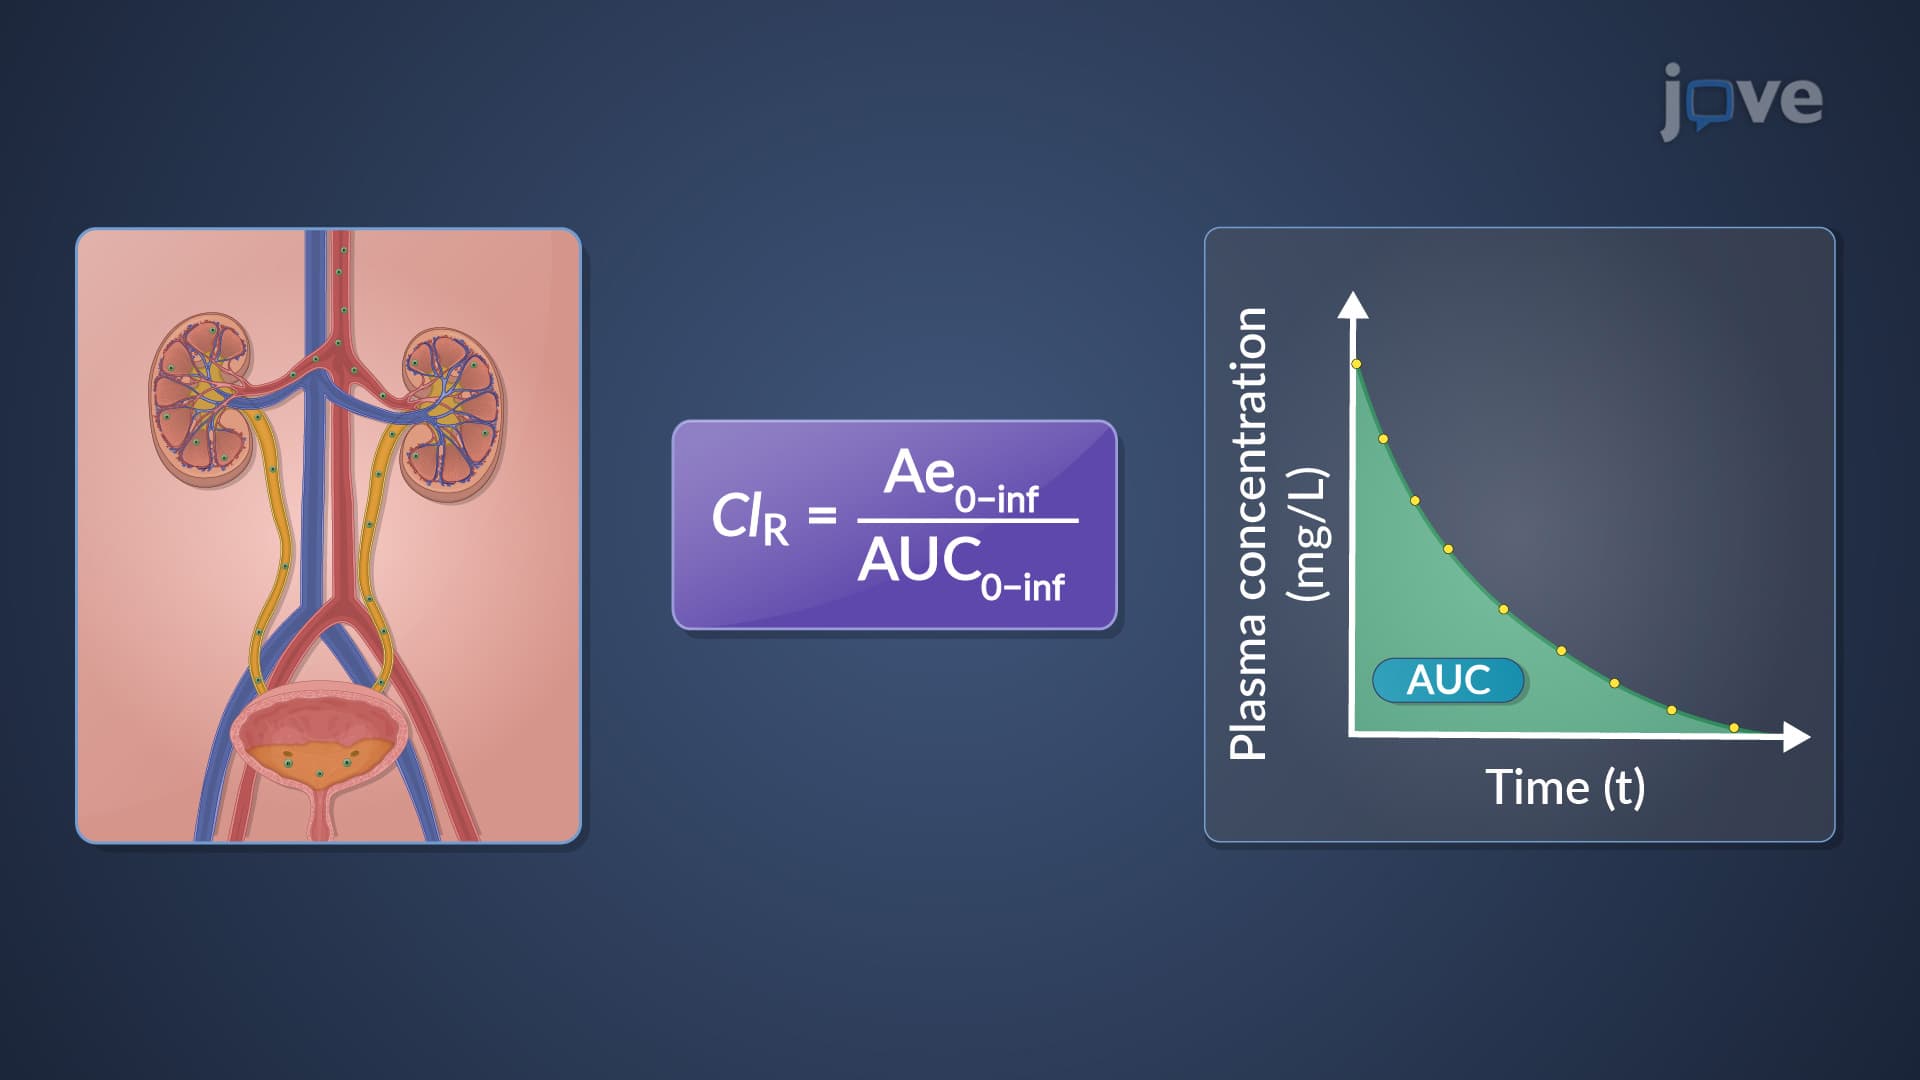
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:28
Structure-Activity Relationships and Drug Design
SAR studies the intricate relationship between a drug's chemical structure and biological activity. It focuses on understanding how modifications to a drug's structure can influence...
 01:28
Drug Products: Biologics, Biosimilars and Interchangeables
 01:19
Pharmacovigilance
This process, termed pharmacovigilance, aims to detect, evaluate, and minimize harmful effects related to medication use. The data collection for pharmacovigilance depends on spontaneous reporting systems, where healthcare professionals or patients voluntarily report suspected ADRs.
In some cases, there...
 01:18
Treatment for Pulmonary Arterial Hypertension: Endothelin Receptor Antagonists
ETs are synthesized through a complex sequence of enzymatic steps, primarily involving an enzyme referred to as endothelin-converting enzyme...