Related Experiment Video
Updated: Oct 5, 2025

Drug-Induced Sleep Endoscopy DISE with Target Controlled Infusion TCI and Bispectral Analysis in Obstructive Sleep Apnea
Published on: December 6, 2016
Neural ventilatory drive decline as a predominant mechanism of obstructive sleep apnoea events
Laura K Gell1, Daniel Vena2, Raichel M Alex2
1Division of Sleep and Circadian Disorders, Brigham and Women's Hospital and Harvard Medical School, Boston, Massachusetts, USA lgell@bwh.harvard.edu.

Background:
In the classic model of obstructive sleep apnoea (OSA), respiratory events occur with sleep-related dilator muscle hypotonia, precipitating increased neural ventilatory 'drive'. By contrast, a drive-dependent model has been proposed, whereby falling drive promotes dilator muscle hypotonia to precipitate respiratory events. Here we determine the extent to which the classic versus drive-dependent models of OSA are best supported by direct physiological measurements.
Methods:
In 50 OSA patients (5-91 events/hour), we recorded ventilation ('flow', oronasal mask and pneumotach) and ventilatory drive (calibrated intraoesophageal diaphragm electromyography, EMG) overnight. Flow and drive during events were ensemble averaged; patients were classified as drive dependent if flow fell/rose simultaneously with drive. Overnight effects of lower drive on flow, genioglossus muscle activity (EMGgg) and event risk were quantified (mixed models).
Results:
On average, ventilatory drive fell (rather than rose) during events (-20 (-42 to 3)%baseline, median (IQR)) and was strongly correlated with flow (R=0.78 (0.24 to 0.94)). Most patients (30/50, 60%) were classified as exhibiting drive-dependent event pathophysiology. Lower drive during sleep was associated with lower flow (-17 (-20 to -14)%/drive) and EMGgg (-3.5 (-3.8 to -3.3)%max/drive) and greater event risk (OR: 2.2 (1.8 to 2.5) per drive reduction of 100%eupnoea); associations were concentrated in patients with drive-dependent OSA (ie, flow: -37 (-40 to -34)%/drive, OR: 6.8 (5.3 to 8.7)). Oesophageal pressure-without tidal volume correction-falsely suggested rising drive during events (classic model).
Conclusions:
In contrast to the prevailing view, patients with OSA predominantly exhibit drive-dependent event pathophysiology, whereby flow is lowest at nadir drive, and lower drive raises event risk. Preventing ventilatory drive decline is therefore considered a target for OSA intervention.
Related Concept Videos
 01:21
Sleep Apnea
The condition is more prevalent among...
 01:18
Neural Control of Respiration
Respiratory Centers in the Brainstem
Two primary areas comprise the respiratory center: the medullary respiratory center in the medulla oblongata and the pontine respiratory group in the pons. The...
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:22
Physiology of Respiration II: Neurogenic Control of Respiration
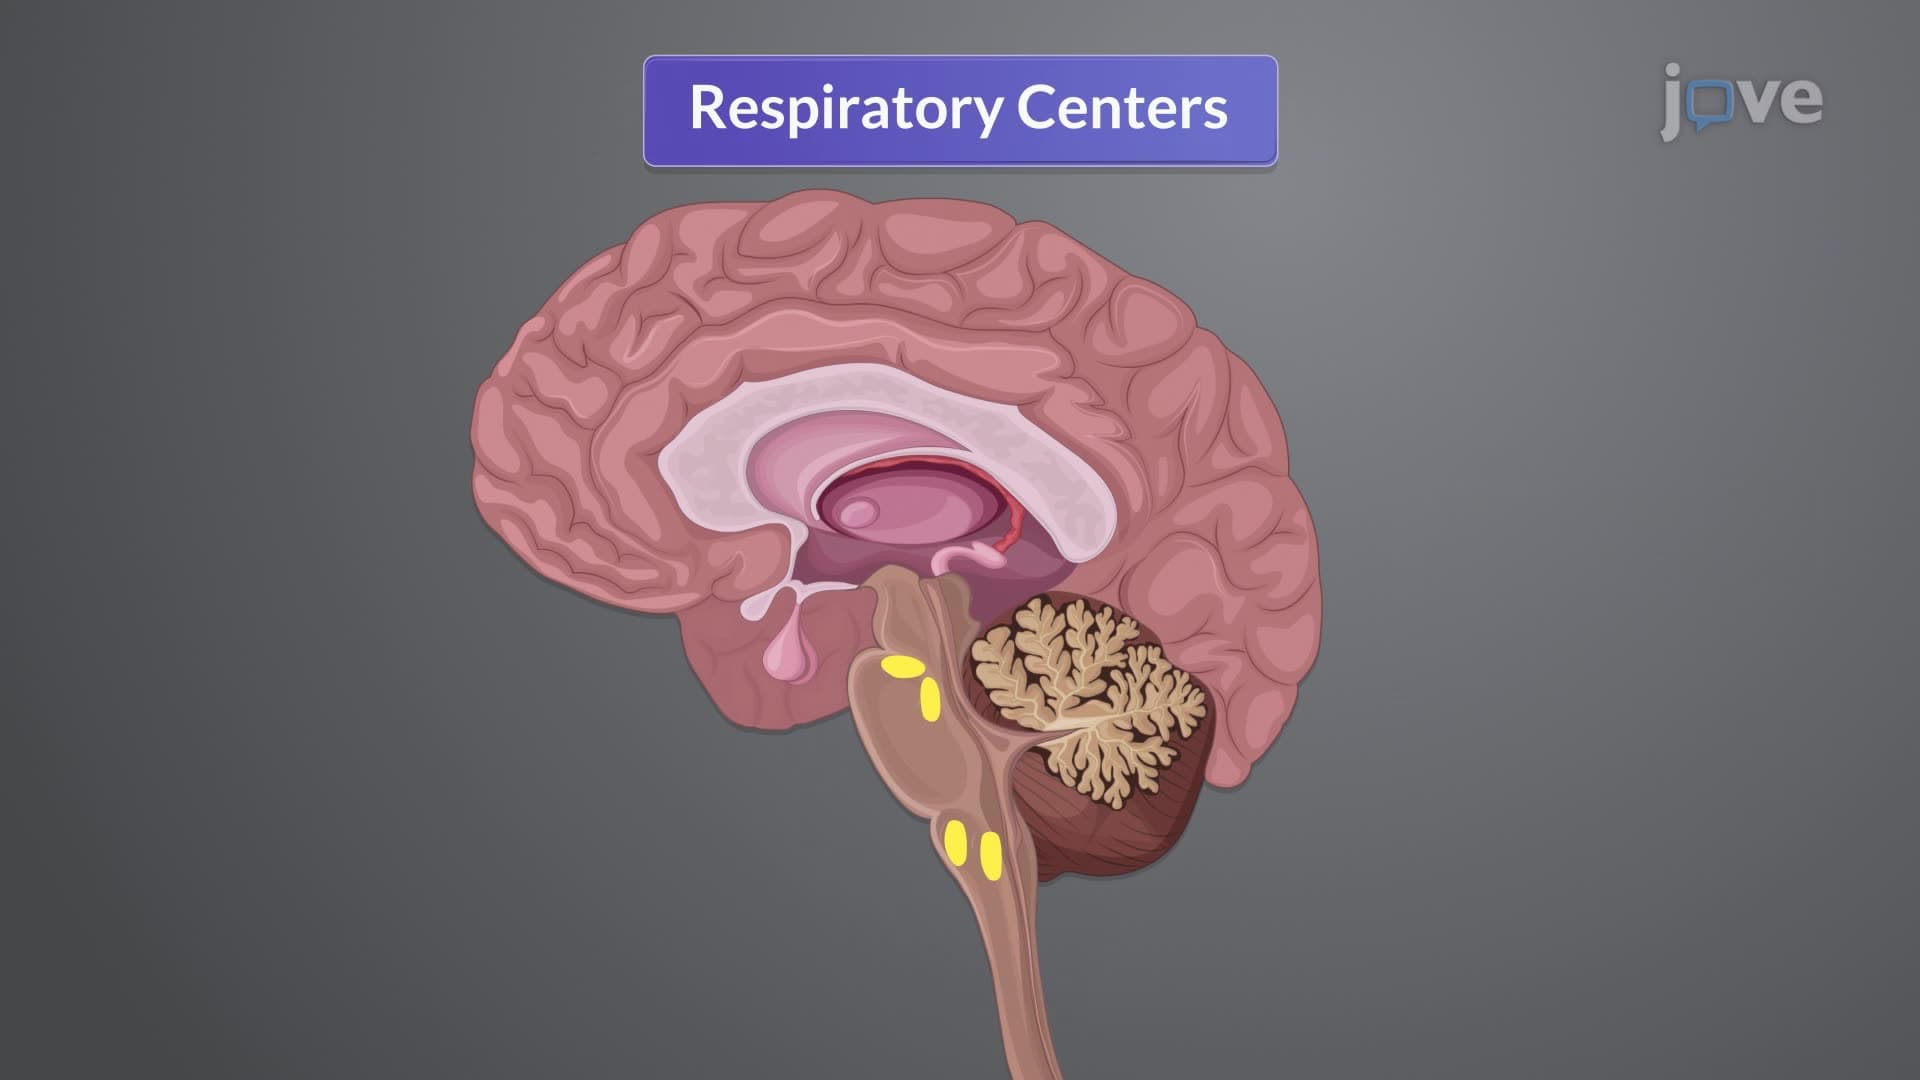
Central Control
The brainstem is the primary site of central control, hosting respiratory centers:
 01:29
Mechanical Ventilation I: Indication and Settings