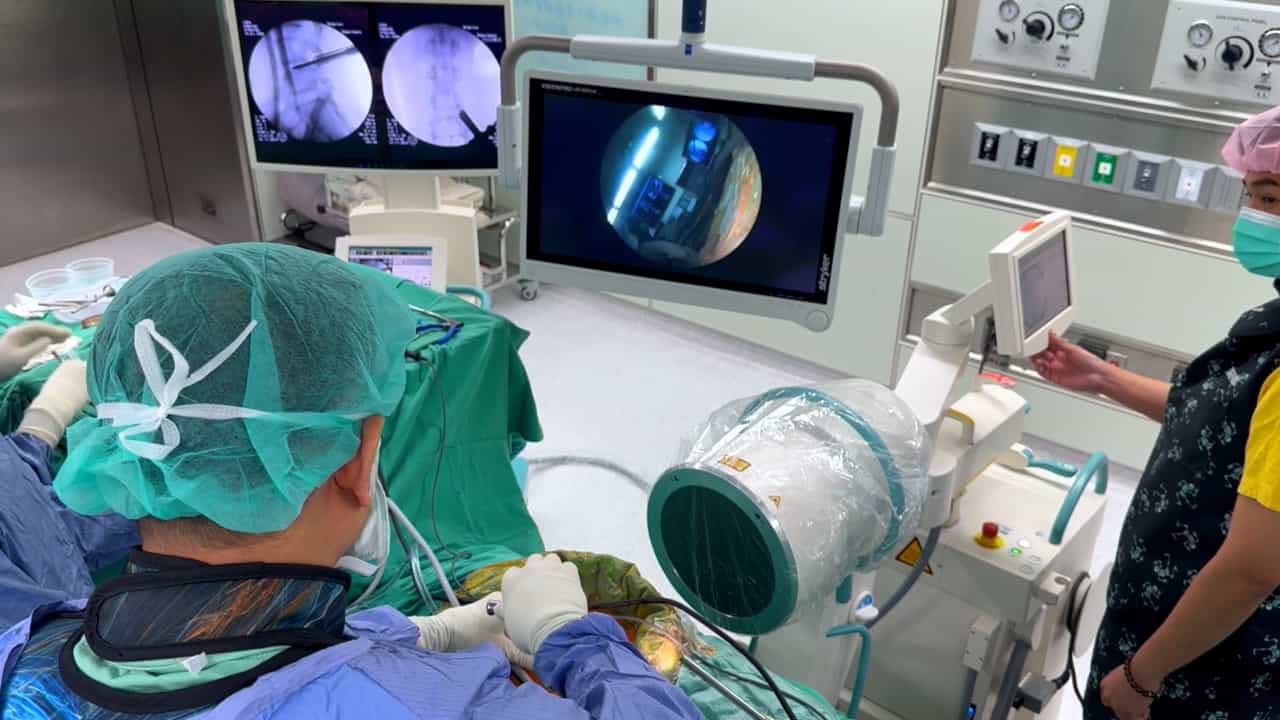
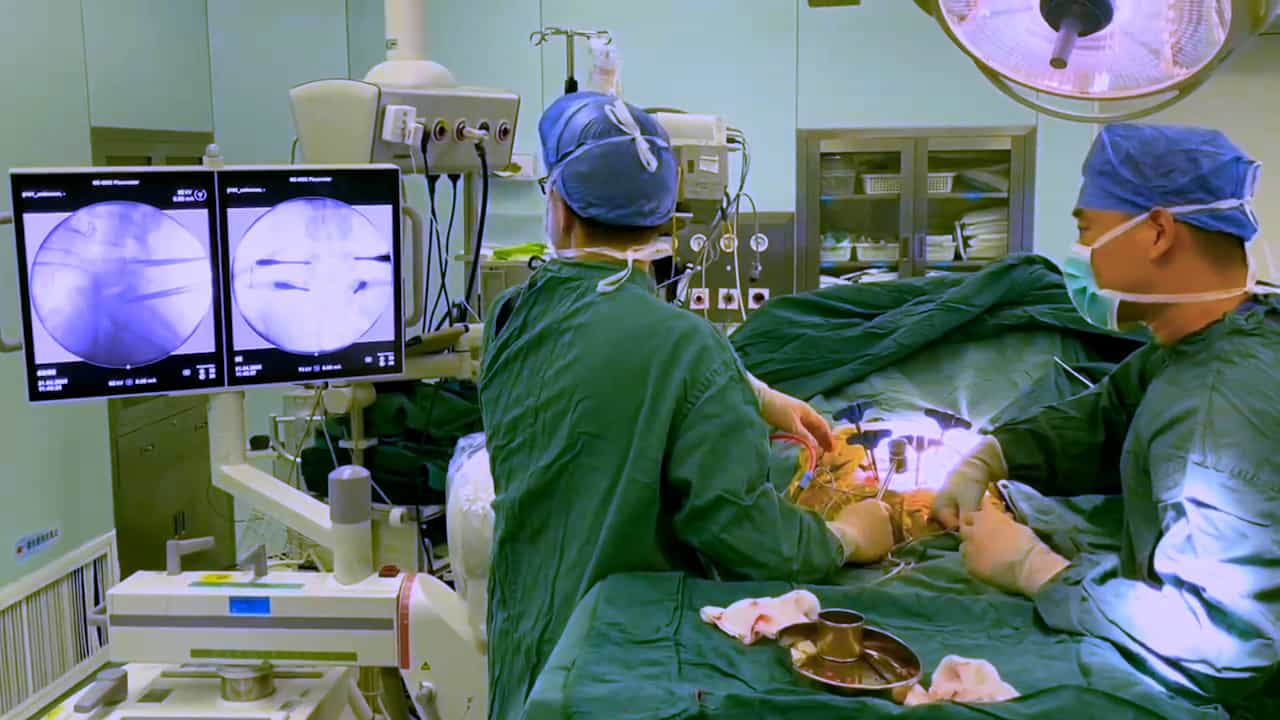
Related Experiment Video
Updated: Oct 5, 2025
Cone Beam Intraoperative Computed Tomography-based Image Guidance for Minimally Invasive Transforaminal Interbody Fusion
Published on: August 6, 2019
Minimally invasive transforaminal lumbar interbody fusion: Technical tips, learning curve, short-term clinical
Reddy Ramanadha Kanala1, Thirumal Yerragunta1, Vamsi Krishna Yerramneni1
1Department of Neurosurgery, Nizam's Institute of Medical Sciences, Hyderabad, Telangana, India.

Background:
Current trends in spine surgeries have shifted to minimally invasive procedures. Minimally invasive approaches are getting more popular for lumbar interbody fusion procedures.
Objectives:
The objective of the study was to report technical modifications, learning curve, and short-term clinical results in minimally invasive transforaminal interbody fusion (MITLIF).
Materials And Methods:
All MITLIF cases performed from 2018 July to March 2020 were included. First three authors were operating surgeons. Visual analog scores (VAS) scoring for pain, Macnab criteria, and Oswestry disability index (ODI) were used for outcome assessment. Operating time, radiation exposure, and complications were assessed separately in a group of 20 as per time sequence in series to assess the learning curve.
Results:
A total of 61 patients were included. Various indications included spondylolisthesis, failed back surgery, calcified lumbar disc, and spondylodiscitis. Mean age was 47.08 ± 12.06. Intraoperative blood loss was 97.04 ± 25.58. Mean operating time and number of C-arm shots were 190.75 ± 37.11 and 159.3 ± 74.54, respectively, in initial 20 cases which however reduced in later operated cases. Significant improvement in VAS and ODI scores was observed at follow-up of 6.34 ± 4.67 months. Three cases needed surgical revision in the initial 20 cases, and there were no revision surgeries in later operated cases.
Conclusion:
MITLIF could be done in failed back surgery cases, spondylodiscitis, and deformity corrections in addition to spondylolisthesis. It has advantages of less injury to soft tissues, maintaining the posterior tension band, decrease in blood loss and hospital stays, and early mobilization. However, it has longer learning curve and takes minimum 20 cases for the surgeon to acquire reasonable experience and confidence.
Insights
Minimally invasive transforaminal interbody fusion (MITLIF) offers benefits like reduced blood loss and faster recovery for various spinal conditions. Surgeons require approximately 20 cases to achieve proficiency with this technique.
Area of Science:
- Spine surgery
- Minimally invasive procedures
- Orthopedic surgery
Background:
- Spine surgery trends favor minimally invasive techniques.
- Minimally invasive lumbar interbody fusion is increasingly adopted.
Purpose of the Study:
- Report technical modifications in minimally invasive transforaminal interbody fusion (MITLIF).
- Evaluate the learning curve and short-term clinical outcomes of MITLIF.
Main Methods:
- Included 61 MITLIF cases (July 2018-March 2020).
- Assessed outcomes using Visual Analog Scale (VAS) and Oswestry Disability Index (ODI).
- Analyzed operating time, radiation exposure, and complications in the first 20 cases to determine the learning curve.
Main Results:
- Significant improvements in VAS and ODI scores were observed post-surgery.
- Mean operating time and C-arm shots decreased as surgical experience increased.
- Revision surgeries were required in 3 of the initial 20 cases, but none in subsequent cases.
Conclusions:
- MITLIF is effective for spondylolisthesis, failed back surgery, spondylodiscitis, and deformities.
- Advantages include minimal soft tissue injury, preserved posterior tension band, reduced blood loss, shorter hospital stays, and early mobilization.
- A learning curve of at least 20 cases is necessary for surgeon proficiency.