Related Experiment Video
Updated: Oct 5, 2025
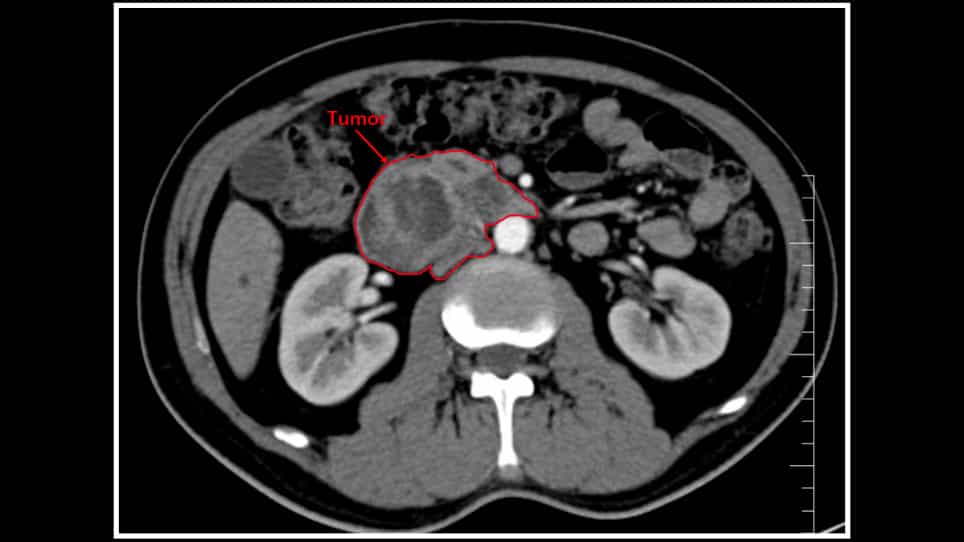

Management of the Uncinate Process in No-Touch Laparoscopic Pancreaticoduodenectomy
Published on: May 5, 2023
Pancreatic intraductal papillary mucinous neoplasms: Current diagnosis and management
Beata Jabłońska1, Paweł Szmigiel2, Sławomir Mrowiec2
1Department of Digestive Tract Surgery, Medical University of Silesia, Katowice 40-752, Poland. bjablonska@poczta.onet.pl.

Intraductal papillary mucinous neoplasms (IPMNs) represent approximately 1% of all pancreatic neoplasms and 25% of cystic neoplasms. They are divided into three types: main duct-IPMN (MD-IPPMN), branch duct-IPMN (BD-IPMN), and mixed type-IPMN. In this review, diagnostics, including clinical presentation and radiological investigations, were described. Magnetic resonance imaging is the most useful for most IPMNs. Management depends on the type and radiological features of IPMNs. Surgery is recommended for MD-IPMN. For BD-IPMN, management involves surgery or surveillance depending on the tumor size, cyst growth rate, solid components, main duct dilatation, high-grade dysplasia in cytology, the presence of symptoms (jaundice, new-onset diabetes, pancreatitis), and CA 19.9 serum level. The patient's age and comorbidities should also be taken into consideration. Currently, there are different guidelines regarding the diagnosis and management of IPMNs. In this review, the following guidelines were presented: Sendai International Association of Pancreatology guidelines (2006), American Gastroenterological Association guidelines, revised international consensus Fukuoka guidelines (2012), revised international consensus Fukuoka guidelines (2017), and European evidence-based guidelines according to the European Study Group on Cystic Tumours of the Pancreas (2018). The Verona Evidence-Based Meeting 2020 was also presented and discussed.
Intraductal papillary mucinous neoplasms (IPMNs) represent approximately 1% of all pancreatic neoplasms and 25% of cystic neoplasms. They are divided into three types: main duct-IPMN (MD-IPPMN), branch duct-IPMN (BD-IPMN), and mixed type-IPMN. In this review, diagnostics, including clinical presentation and radiological investigations, were described. Magnetic resonance imaging is the most useful for most IPMNs. Management depends on the type and radiological features of IPMNs. Surgery is recommended for MD-IPMN. For BD-IPMN, management involves surgery or surveillance depending on the tumor size, cyst growth rate, solid components, main duct dilatation, high-grade dysplasia in cytology, the presence of symptoms (jaundice, new-onset diabetes, pancreatitis), and CA 19.9 serum level. The patient's age and comorbidities should also be taken into consideration. Currently, there are different guidelines regarding the diagnosis and management of IPMNs. In this review, the following guidelines were presented: Sendai International Association of Pancreatology guidelines (2006), American Gastroenterological Association guidelines, revised international consensus Fukuoka guidelines (2012), revised international consensus Fukuoka guidelines (2017), and European evidence-based guidelines according to the European Study Group on Cystic Tumours of the Pancreas (2018). The Verona Evidence-Based Meeting 2020 was also presented and discussed.

Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the...