Related Experiment Video
Updated: Oct 5, 2025

A Novel Rescue Technique for Difficult Intubation and Difficult Ventilation
Published on: January 17, 2011
Cuffed versus uncuffed endotracheal tubes for neonates
Vedanta Dariya1, Luca Moresco2, Matteo Bruschettini3,4
1Department of Pediatrics, Division of Neonatal-Perinatal Medicine, University of Texas Southwestern Medical Center, Dallas, Texas, USA.

Background:
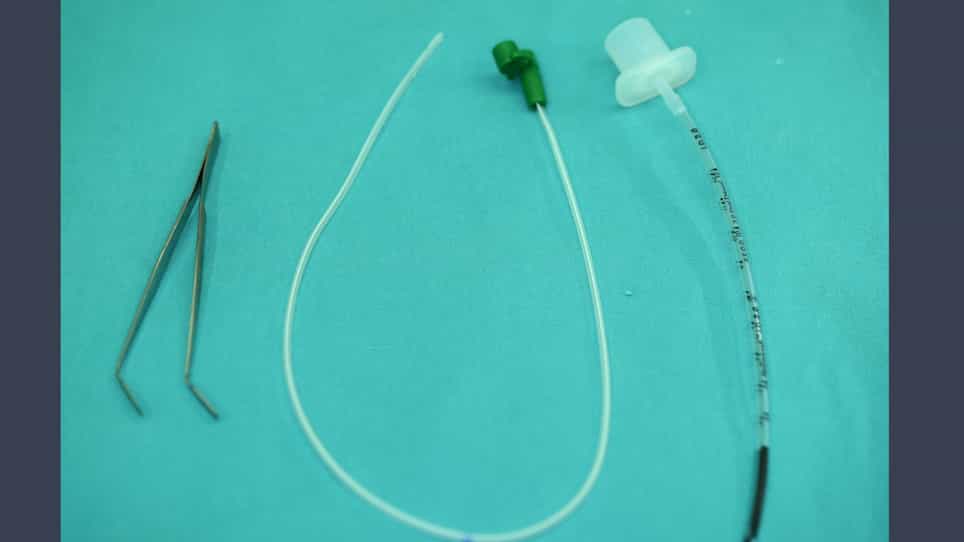
Endotracheal intubation is a commonly performed procedure in neonates, the risks of which are well-described. Some endotracheal tubes (ETT) are equipped with a cuff that can be inflated after insertion of the ETT in the airway to limit leak or aspiration. Cuffed ETTs have been shown in larger children and adults to reduce gas leak around the ETT, ETT exchange, accidental extubation, and exposure of healthcare workers to anesthetic gas during surgery. With improved understanding of neonatal airway anatomy and the widespread use of cuffed ETTs by anesthesiologists, the use of cuffed tubes is increasing in neonates.
Objectives:
To assess the benefits and harms of cuffed ETTs (inflated or non-inflated) compared to uncuffed ETTs for respiratory support in neonates.
Search Methods:
We searched CENTRAL, PubMed, and CINAHL on 20 August 2021; we also searched trial registers and checked reference lists to identify additional studies.
Selection Criteria:
We included randomized controlled trials (RCTs), quasi-RCTs, and cluster-randomized trials comparing cuffed (inflated and non-inflated) versus uncuffed ETTs in newborns. We sought to compare 1. inflated, cuffed versus uncuffed ETT; 2. non-inflated, cuffed versus uncuffed ETT; and 3. inflated, cuffed versus non-inflated, cuffed ETT.
Data Collection And Analysis:
We used the standard methods of Cochrane Neonatal. Two review authors independently assessed studies identified by the search strategy for inclusion, extracted data, and assessed risk of bias. We used the GRADE approach to assess the certainty of evidence.
Main Results:
We identified one eligible RCT for inclusion that compared the use of cuffed (inflated if ETT leak greater than 20% with cuff pressure 20 cm H2O or less) versus uncuffed ETT. The author provided a spreadsheet with individual data. Among 76 infants in the original manuscript, 69 met the inclusion and exclusion criteria for this Cochrane Review. We found possible bias due to lack of blinding and other bias. We are very uncertain about frequency of postextubation stridor, because the confidence intervals (CI) of the risk ratio (RR) were very wide (RR 1.36, 95% CI 0.35 to 5.25; risk difference (RD) 0.03, -0.11 to 0.18; 1 study, 69 participants; very low-certainty evidence). No neonate was diagnosed with postextubation subglottic stenosis; however, endoscopy was not available to confirm the clinical diagnosis. We are very uncertain about reintubation for stridor or subglottic stenosis because the CIs of the RR were very wide (RR 0.27, 95% CI 0.01 to 6.49; RD -0.03, 95% CI -0.11 to 0.05; 1 study, 69 participants; very low-certainty evidence). No neonate had surgical intervention (e.g. endoscopic balloon dilation, cricoid split, tracheostomy) for stridor or subglottic stenosis (1 study, 69 participants). Neonates randomized to cuffed ETT may be less likely to have a reintubation for any reason (RR 0.06, 95% CI 0.01 to 0.45; RD -0.39, 95% CI -0.57 to -0.21; number needed to treat for an additional beneficial outcome 3, 95% CI 2 to 5; 1 study, 69 participants; very low-certainty evidence). We are very uncertain about accidental extubation because the CIs of the RR were wide (RR 0.82, 95% CI 0.12 to 5.46; RD -0.01, 95% CI -0.12 to 0.10; 1 study, 69 participants; very low-certainty evidence). We are very uncertain about all-cause mortality during initial hospitalization because the CIs of the RR were extremely wide (RR 2.46, 95% CI 0.10 to 58.39; RD 0.03, 95% CI -0.05 to 0.10; 1 study, 69 participants; very low-certainty evidence). There is one ongoing trial. We classified two studies as awaiting classification because outcome data were not reported separately for newborns and older infants.
Authors' Conclusions:
Evidence for comparing cuffed versus uncuffed ETTs in neonates is limited by a small number of babies in a single RCT with possible bias. There is very low certainty evidence for all outcomes of this review. CIs of the estimate for postextubation stridor were wide. No neonate had clinical evidence for subglottic stenosis; however, endoscopy results were not available to assess the anatomy. Additional RCTs are necessary to evaluate the benefits and harms of cuffed ETTs (inflated and non-inflated) in the neonatal population. These studies must include neonates and be conducted both for short-term use (in the setting of the operating room) and chronic use (in the setting of chronic lung disease) of cuffed ETTs.
Related Concept Videos
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...