Related Experiment Video
Updated: Oct 5, 2025


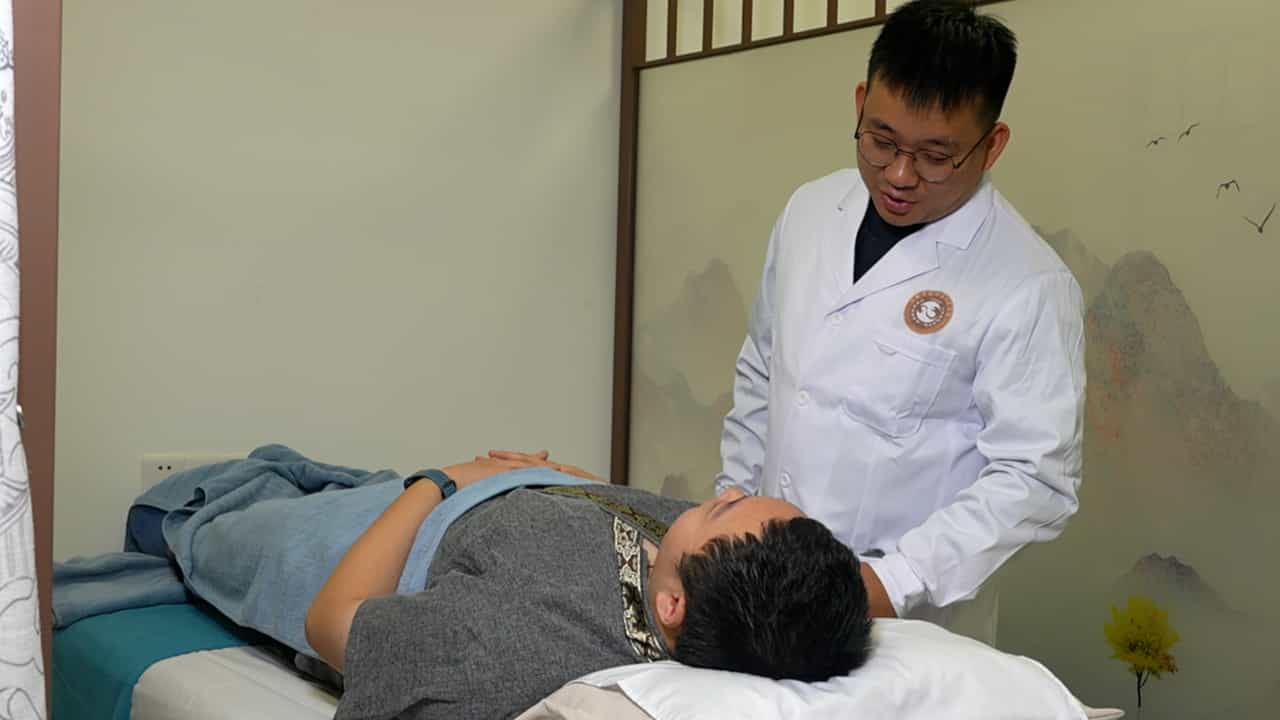
Home-Based Prescribed Pulmonary Exercise in Patients with Stable Chronic Obstructive Pulmonary Disease
Published on: August 24, 2019
Physical and affective components of dyspnoea are improved by pulmonary rehabilitation in COPD
Jean-Marie Grosbois1, Sarah Gephine2,3, Maeva Kyheng4
1FormAction Santé, Pérenchies, France jmgrosbois@formactionsante.com.

Background:
Dyspnoea is a multidimensional experience of breathing discomfort, but its affective dimension is unfrequently assessed in people with chronic obstructive pulmonary disease (COPD). We evaluated the effectiveness of a home-based pulmonary rehabilitation (PR) programme on the physical and affective components of dyspnoea assessed by the Dyspnoea-12 (D-12) questionnaire. We also determined the baseline characteristics that contributed to the change in D-12 scores.
Methods:
In this retrospective study, 225 people with COPD (age, 65±11 years; forced expiratory volume in 1 s (FEV1), 35±15% of predicted value) were enrolled into a person-centric home-based PR, consisting of a weekly supervised 90 min home session during 8 weeks. D-12 questionnaire, health status, anxiety and depressive symptoms, exercise tolerance and general fatigue were assessed at baseline (M0), at the end of PR programme (M2), and 8 (M8) and 14 months (M14) after M0. Multivariable analysis of covariance (ANCOVA) models were performed to identify the baseline characteristics that contributed to the change in D-12 scores.
Results:
Both physical and affective components of dyspnoea and all the other outcome measures were improved at M2, M8 and M14 compared with baseline (p<0.05). Baseline body mass index was the only significant independent predictor of the changes in physical dyspnoea score, while the change in the affective dimension of dyspnoea after PR was associated with FEV1, anxiety symptoms and exercise tolerance (6 min stepper test). However, since these variables had only a small impact on the changes in D-12 questionnaire scores, results from the ANCOVA analysis should be taken cautiously.
Conclusion:
Both physical and affective components of dyspnoea were improved, at short term and long term, by 8 weeks of individualised home-based PR. The present results support the importance of assessing dyspnoea as a multidimensional experience during PR, warranting replication by robustly designed randomised and controlled studies.
More Related Videos

Related Concept Videos
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:29
Chronic Obstructive Pulmonary Disease-V: Management
Smoking Cessation
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:24
Chest Physiotherapy
Purpose
CPT is primarily used for patients with excessive bronchial secretions who have difficulty clearing...
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...