New Endoscopic Solutions in Managing Phlegmonous Esophagitis
Related Experiment Video
Updated: Oct 5, 2025
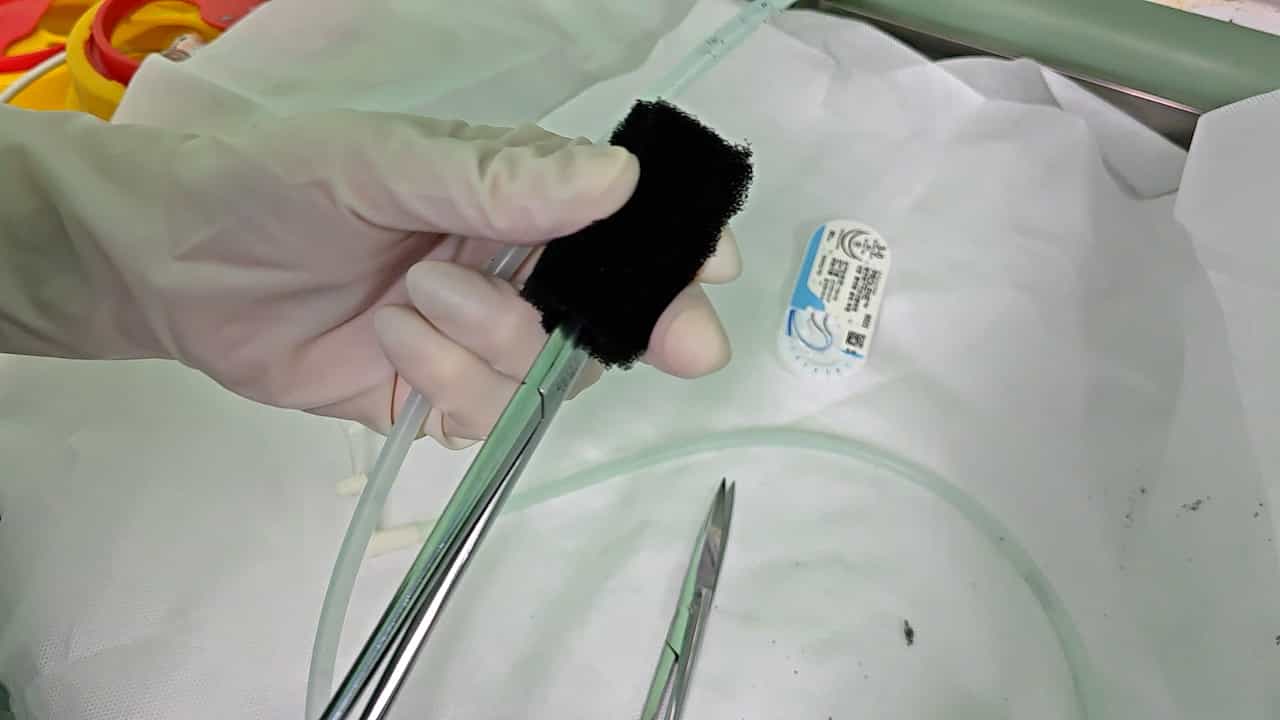
Endoscopic Vacuum Therapy for the Treatment of Anastomotic Leakage after Total Gastrectomy with Esophagojejunostomy
Published on: August 22, 2025
Ana L Santos1,2, João Santos-Antunes1,2, Rui Morais1,2
1Gastroenterology Department, Centro Hospitalar Universitário de São João, Porto, Portugal.

Abstract:
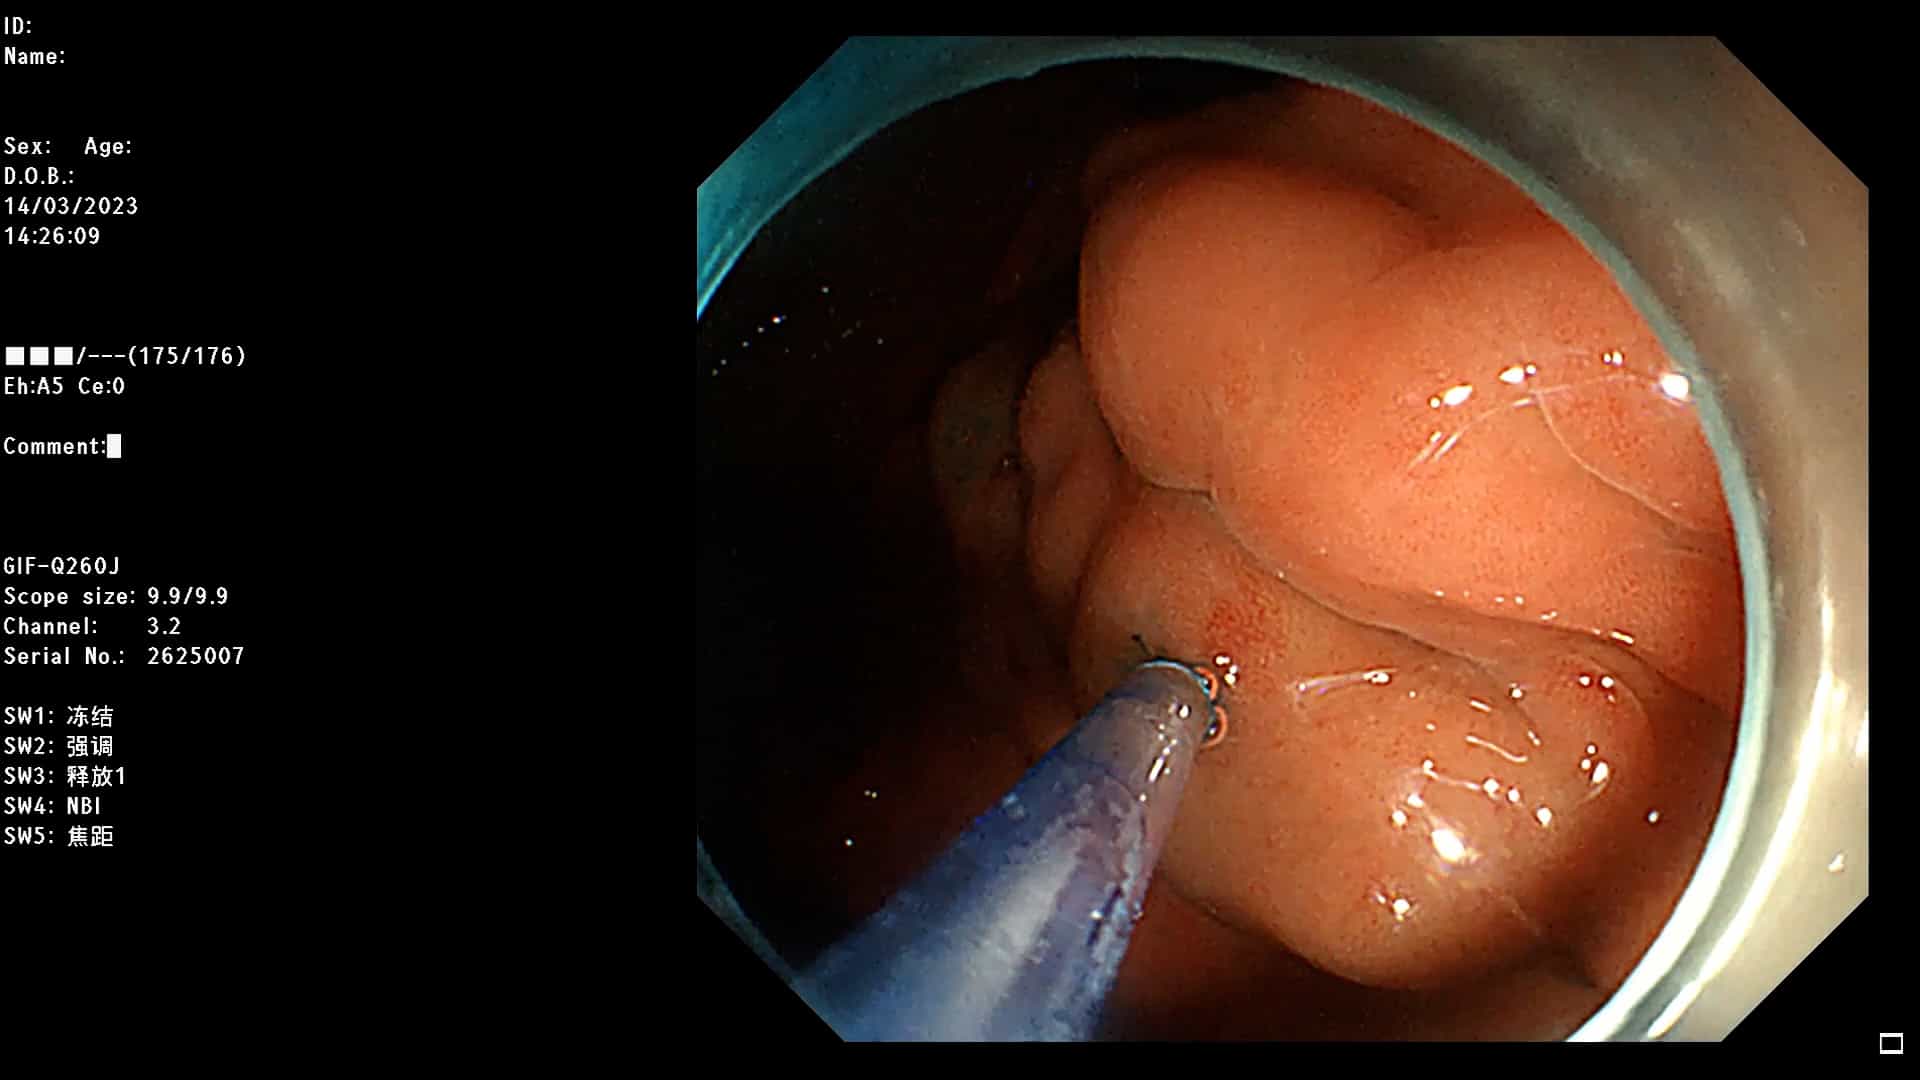
A 48-year-old woman was admitted in the emergency department due to epigastric pain, nausea, vomiting, and cough. She presented with fever and increased inflammatory parameters. A thoracoabdominal computed tomography (CT) was performed and revealed thickening of the gastric fundus and esophagus, with an apparent laceration in esophageal mucosa and associated dissection of esophageal wall. In upper endoscopy (UE), a bulging of esophageal and gastric walls was observed, with an ulceration in proximal esophagus, suggestive of a perforation. After multidisciplinary discussion, a minimally invasive endoscopic approach was decided. Internal esophageal drainage (IED) was assured with performance of some incisions with Dual-knife® (Olympus, Tokyo) along the mucosal and submucosal layers in the esophagus. During the incision, extravasation of pus was evident. One week later, due to clinical worsening and evidence of esophageal perforation in CT scan, UE was repeated. We confirmed esophageal perforation with visualization of two millimetric defects in the proximal esophagus. Significant bulging of the gastric fundus and body was also observed. IED was repeated with mucosal incision of the gastric bulging using Needle-Cut 3V® (Olympus, Tokyo), with extravasation of a significant quantity of pus. We decided to proceed to endoscopic vacuum therapy that was performed with sponge placement in the esophageal lumen (Endosponge®, B. Braun, Melsungen, Germany). UE was repeated 1 week later with sponge removal and confirmation of resolution of esophageal perforation. An improvement of the thickening of gastric fundus and body was also seen. One month later after admission, the patient was discharged home, eating normally, and remains well in the follow-up.
Related Concept Videos
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations: