Related Experiment Video
Updated: Oct 5, 2025

Investigation into Deep Breathing through Measurement of Ventilatory Parameters and Observation of Breathing Patterns
Published on: September 16, 2019
Effect of pursed-lip breathing and forward trunk lean positions on regional chest wall volume and ventilatory pattern
Nutsupa Ubolnuar1,2, Anong Tantisuwat1, Witaya Mathiyakom3
1Department of Physical Therapy, Faculty of Allied Health Sciences, Chulalongkorn University, Bangkok, Thailand.

Abstract:
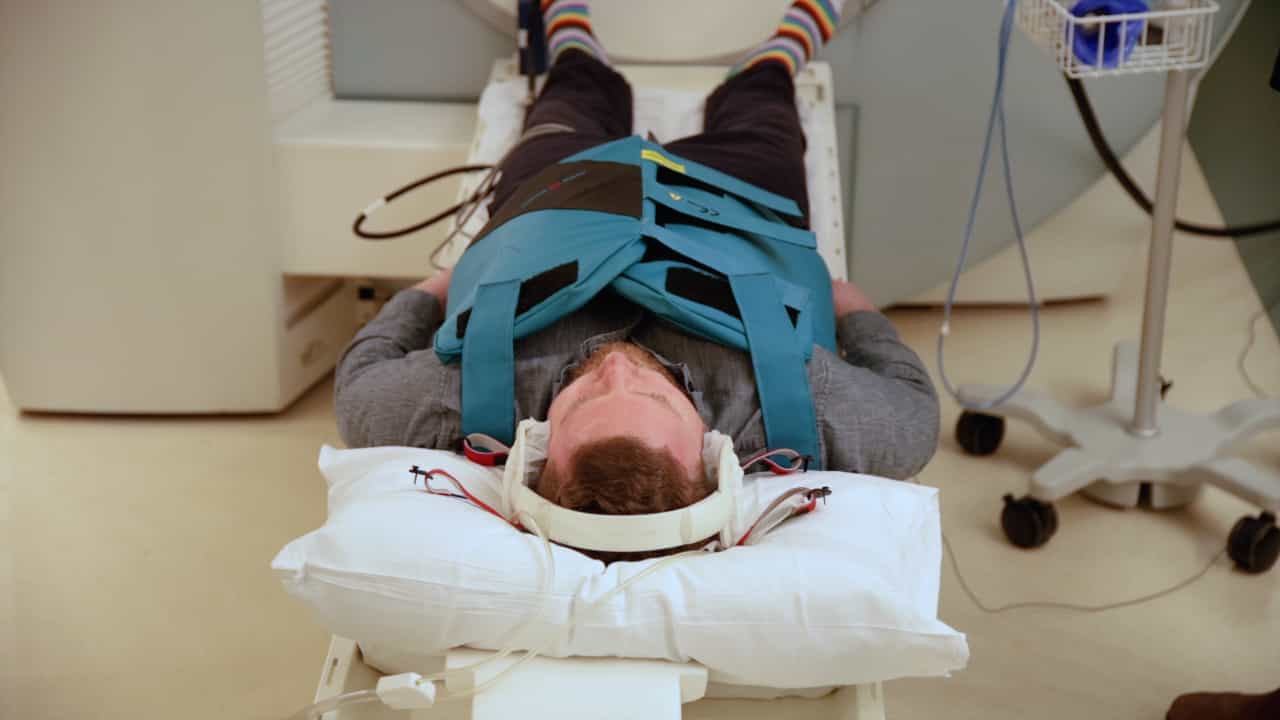
Pursed-lip breathing (PLB) and forward trunk lean posture (FTLP) are commonly used to relieve dyspnea and improve ventilation in a rehabilitation program. However, their effect on chest wall volumes and movements in older adults without chronic obstructive pulmonary disease has never been investigated. This observational study aimed to identify the effect of combined PLB and FTLP on total and regional chest wall volumes, ventilatory pattern, and thoracoabdominal movement using in older adults. It was hypothesized that the combined PLB with FTLP would result in the highest chest wall volumes among the experimental tasks. Twenty older adults performed 2 breathing patterns of quiet breathing (QB) and PLB during a seated upright (UP) position and FTLP. An optoelectronic plethysmography system was used to capture the chest wall movements during the 4 experimental tasks. Tidal volume (VT) was separated into pulmonary ribcage, abdominal ribcage, and abdomen volume. The changes in anterior-posterior (AP) and medial-lateral (ML) chest wall diameters at 3 levels were measured and used to identify chest wall mechanics to improve chest wall volumes. The PLB significantly improved ventilation and chest wall volumes than the QB (P < .05). VT of pulmonary ribcage, VT of abdominal ribcage, and VT were significantly higher during the PLB + UP (P < .05) and during the PLB + FTLP (P < .01) as compared to those of QB performed in similar body positions. However, there was no significant in total and regional lung volumes between the PLB + UP and the PLB + FTLP. The AP diameter changes at the angle of Louis and xiphoid levels were greater during the PLB + UP than the QB + UP and the QB + FTLP (P < .01). The AP diameter changes at the umbilical level and the ML diameter changes at the xiphoid level were significantly larger during the PLB + FTLP than the QB + FTLP and the QB + UP (P < .05). The ML diameter changes at the umbilical level were significantly greater during the PLB + FTLP than the QB + UP (P < .05). However, no significant difference in the relative regional chest wall volumes and phase angle among the experimental tasks (P > .05). In conclusion, a combined PLB performed in an FTLP or UP sitting could be used as a strategy to improve chest wall volumes and ventilation in older adults.

Related Concept Videos
 01:15
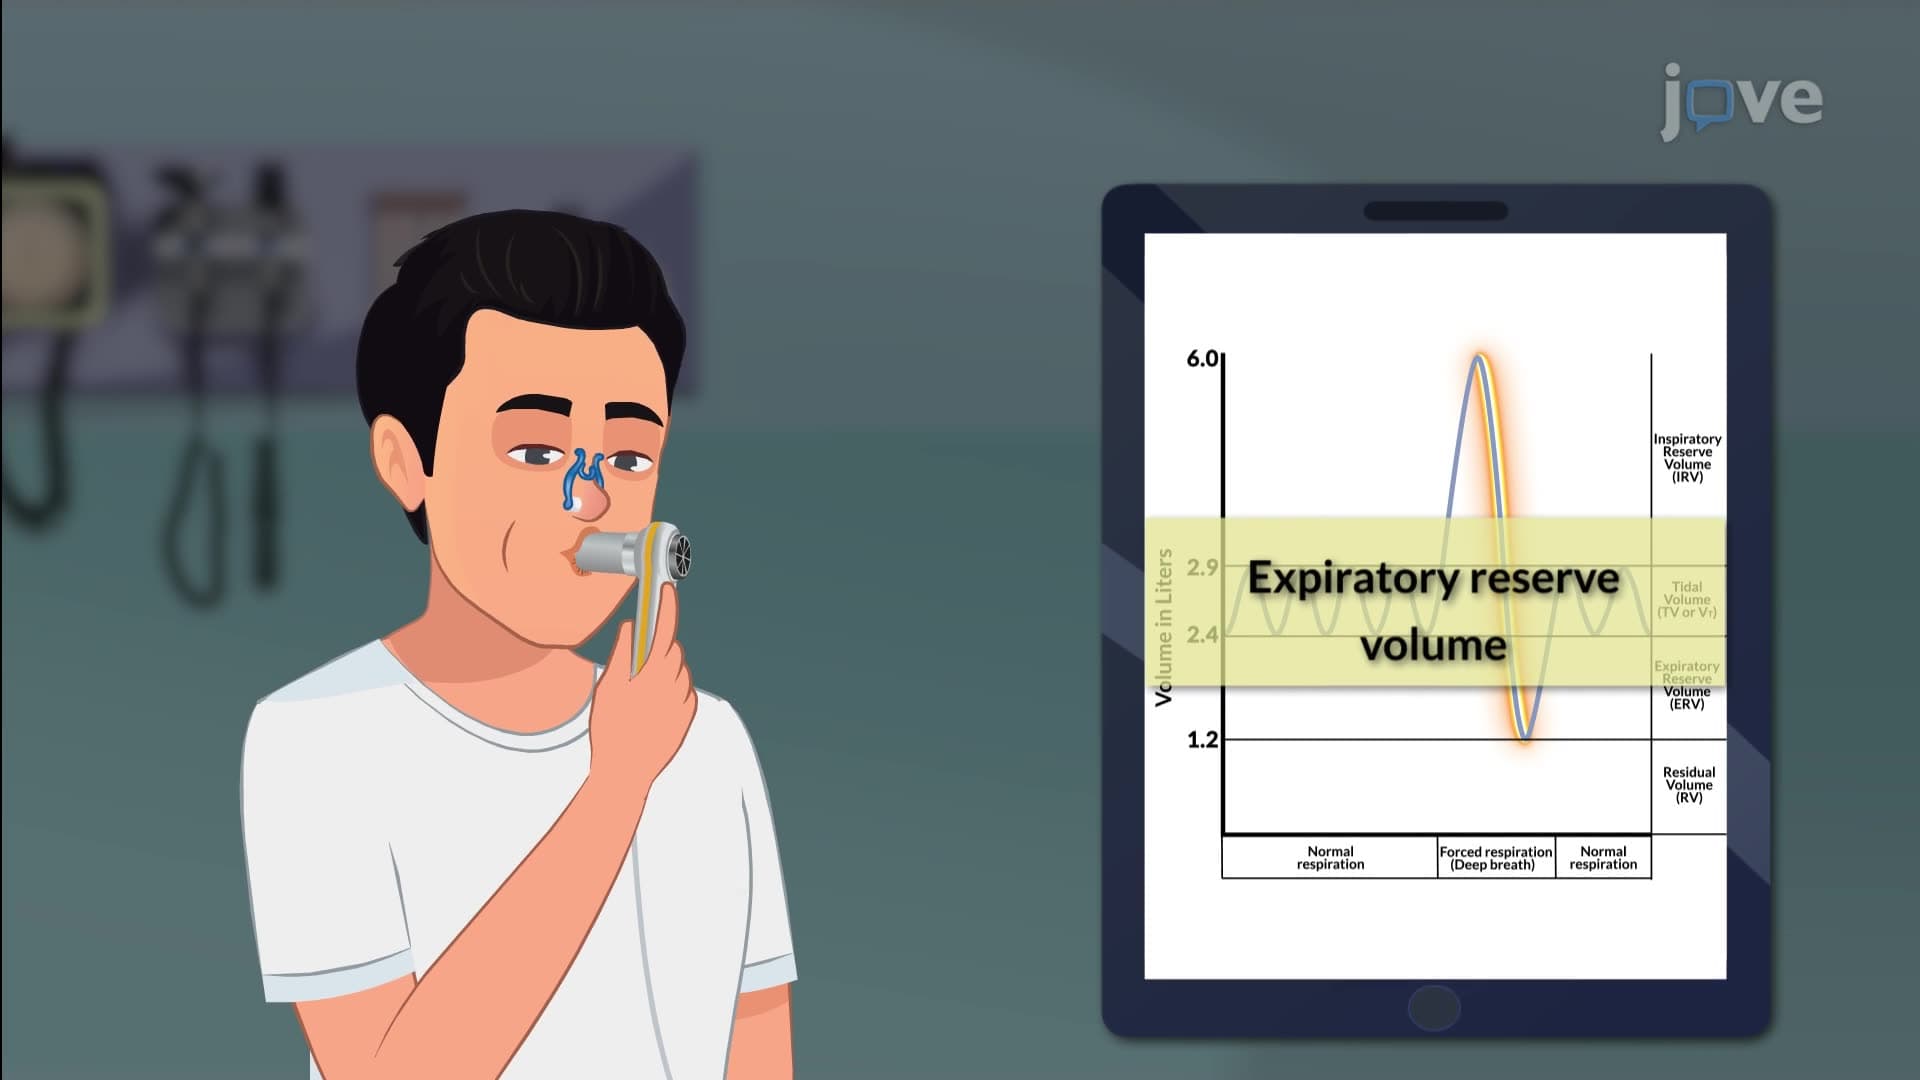
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:26
Respiratory Volumes and Capacities I
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...