Related Experiment Video
Updated: Oct 5, 2025
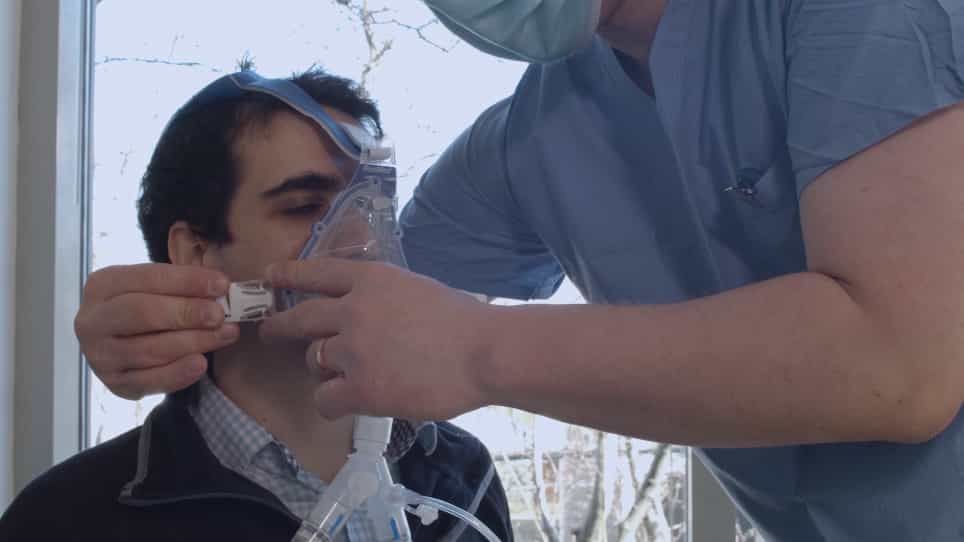

A Novel Inhalation Mask System to Deliver High Concentrations of Nitric Oxide Gas in Spontaneously Breathing Subjects
Published on: May 4, 2021
Reducing asthma attacks in children using exhaled nitric oxide (RAACENO) as a biomarker to inform treatment strategy:
Steve Turner1, Seonaidh Cotton2, Jessica Wood2
1Royal Aberdeen Children's Hospital, University of Aberdeen, Aberdeen, UK.

Insights
Adding fractional exhaled nitric oxide (FeNO) to asthma treatment did not reduce exacerbations in children. Current asthma symptom management remains the primary approach for guiding treatment decisions in pediatric asthma care.
Area of Science:
- Pediatric pulmonology
- Respiratory medicine
- Clinical trial research
Background:
- The utility of fractional exhaled nitric oxide (FeNO) in optimizing asthma management for children remains under investigation.
- Current treatment guidelines for pediatric asthma often rely on symptom-based assessments.
Purpose of the Study:
- To evaluate if incorporating FeNO measurements into symptom-guided treatment reduces asthma exacerbations in children.
- To compare the efficacy of FeNO-guided versus symptom-guided treatment strategies in pediatric asthma patients.
Main Methods:
- A multicenter, randomized controlled phase 3 trial (RAACENO) involving 509 children aged 6-15 years with asthma.
- Participants were assigned to either FeNO plus symptom-guided treatment or symptom-guided treatment alone.
- The primary outcome was the rate of asthma exacerbations requiring oral corticosteroids over 12 months.
Main Results:
- No significant difference in asthma exacerbations was observed between the FeNO-guided and standard care groups (OR 0.88, 95% CI 0.61 to 1.27; p=0.49).
- The primary outcome occurred in 48.2% of the FeNO group and 51.4% of the standard care group.
- Adverse events were infrequent and similar between groups.
Conclusions:
- Adding FeNO measurements to symptom-guided treatment did not significantly decrease asthma exacerbations in children.
- Asthma symptom assessment remains a key factor in guiding treatment decisions for pediatric asthma.
Background:
The benefit of fractional exhaled nitric oxide (FeNO) in guiding asthma treatment is uncertain. We evaluated the efficacy of adding FeNO to symptom-guided treatment in children with asthma versus only symptom-guided treatment.
Methods:
RAACENO was a multicentre, parallel, randomised, controlled, phase 3 trial done in 35 secondary care centres and 17 primary care recruitment sites (only seven primary care sites managed to recruit patients) in the UK. Patients with a confirmed asthma diagnosis, aged 6-15 years, prescribed inhaled corticosteroids, and who received a course of oral corticosteroids for at least one asthma exacerbation during the 12 months before recruitment were included. Participants were randomly assigned to either FeNO plus symptom-guided treatment (intervention) or symptom-guided treatment alone (standard care) using a 24 h in-house, web-based randomisation system. Participants and the clinical and research teams were not masked to the group allocation. A web-based algorithm gave treatment recommendations based on the Asthma Control Test (ACT) or Childhood ACT (CACT) score; current asthma treatment; adherence to study treatment in the past 3 months; and use of FeNO (in the intervention group). Follow-up occurred at 3-month intervals for 12 months. The primary outcome was any asthma exacerbation treated with oral corticosteroids in the 12 months after randomisation, assessed in the intention-to-treat population. This study is registered with the International Standard Randomised Controlled Trial Registry, ISRCTN67875351.
Findings:
Between June 22, 2017, and Aug 8, 2019, 535 children were assessed for eligibility, 20 were ineligible and six were excluded post-randomisation. 509 children were recruited and at baseline, the mean age of participants was 10·1 years (SD 2·6), and 308 (60·5%) were male. The median FeNO was 21 ppb (IQR 10-48), mean predicted FEV1 was 89·6% (SD 18·0), and median daily dose of inhaled corticosteroids was 400 microg budesonide equivalent (IQR 400-1000). Asthma was partly or fully controlled in 256 (50·3%) of 509 participants. The primary outcome, which was available for 506 (99%) of 509 participants, occurred in 123 (48·2%) of 255 participants in the intervention group and 129 (51·4%) of 251 in the standard care group, the intention-to-treat adjusted odds ratio (OR) was 0·88 (95% CI 0·61 to 1·27; p=0·49). The adjusted difference in the percentage of participants who received the intervention in whom the primary outcome occurred compared with those who received standard care was -3·1% (-11·9% to 5·6%). In 377 (21·3%) of 1771 assessments, the algorithm recommendation was not followed. Adverse events were reported by 27 (5·3%) of 509 participants (15 in the standard care group and 12 in the intervention group). The most common adverse event was itch after skin prick testing (reported by eight participants in each group).
Interpretation:
We found that the addition of FeNO to symptom-guided asthma treatment did not lead to reduced exacerbations among children prone to asthma exacerbation. Asthma symptoms remain the only tool for guiding treatment decisions.
Funding:
National Institute for Health Research.


Related Concept Videos
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:30
Asthma-IV: Nursing Management
First, in...
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:24
Asthma-III: Symptoms and Complications
Classification of Asthma
 01:25
Antiasthma Drugs: Mast Cell Stabilizers and Anti-IgE Drugs
Mast cell stabilizers, such as cromolyn (also known as sodium cromoglycate) and nedocromil (Tilade), are effective drugs in asthma management. These stabilizers hinder histamine release by skillfully obstructing the activation of mast cells and other cellular entities. Notably, they navigate this task without...