Early Outcomes of Robotic Versus Video-Assisted Thoracoscopic Anatomical Resection for Lung Cancer
Related Experiment Video
Updated: Oct 4, 2025
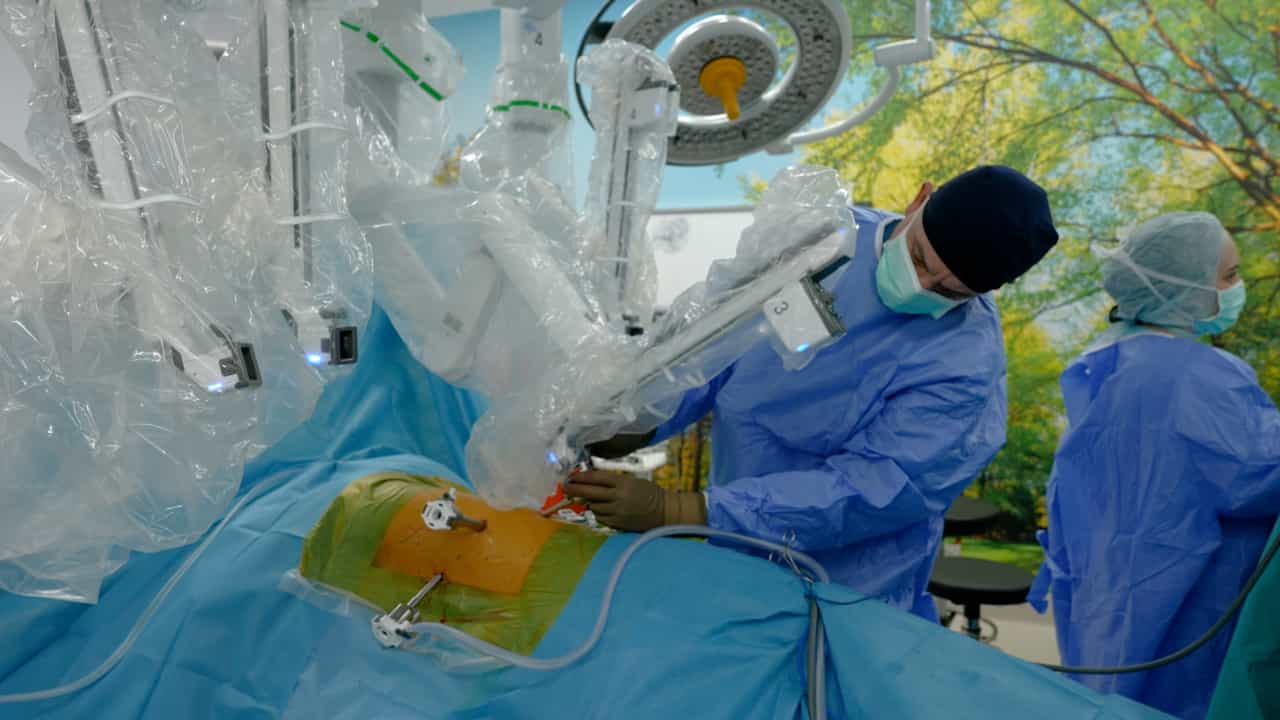
Subcostal Specimen Removal in Completely Portal Robotic Lobectomy
Published on: April 19, 2024
Ji Hyeon Park1, Samina Park1, Chang Hyun Kang1
1Department of Thoracic and Cardiovascular Surgery, Seoul National University Hospital, Seoul National University College of Medicine, Seoul, Korea.

Background:
We compared the safety and effectiveness of robotic anatomical resection and video-assisted thoracoscopic surgery (VATS).
Methods:
A retrospective analysis was conducted of the records of 4,283 patients, in whom an attempt was made to perform minimally invasive anatomical resection for lung cancer at Seoul National University Hospital from January 2011 to July 2020. Of these patients, 138 underwent robotic surgery and 4,145 underwent VATS. Perioperative outcomes were compared after propensity score matching including age, sex, height, weight, pulmonary function, smoking status, performance status, comorbidities, type of resection, combined bronchoplasty/angioplasty, tumor size, clinical T/N category, histology, and neoadjuvant treatment.
Results:
In total, 137 well-balanced pairs were obtained. There were no cases of 30-day mortality in the entire cohort. Conversion to thoracotomy was required more frequently in the VATS group (VATS 6.6% vs. robotic 0.7%, p=0.008). The complete resection rate (VATS 97.8% vs. robotic 98.5%, p=1.000) and postoperative complication rate (VATS 17.5% vs. robotic 19.0%, p=0.874) were not significantly different between the 2 groups. The robotic group showed a slightly shorter hospital stay (VATS 5.8±3.9 days vs. robotic 5.0±3.6 days, p=0.052). N2 nodal upstaging (cN0/pN2) was more common in the robotic group than the VATS group, but without statistical significance (VATS 4% vs. robotic 12%, p=0.077).
Conclusion:
Robotic anatomical resection in lung cancer showed comparable early outcomes when compared to VATS. In particular, robotic resection presented a lower conversion-to-thoracotomy rate. Furthermore, a robotic approach might improve lymph node harvesting in the N2 station.
More Related Videos
 05:39
Author Spotlight: A Non-Intubated Video-Assisted Thoracoscopic Surgery with Multimodal Analgesia and Sevoflurane Inhalation Anesthesia
Published on: May 26, 2023
 12:45
Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022