

Exploring HbA1c variation between Australian diabetes centres: The impact of centre-level and patient-level factors
Matthew Quigley1, Arul Earnest1, Naomi Szwarcbard1
1School Public Health and Preventive Medicine, Monash University, Melbourne, Victoria, Australia.

Background:
Increasing global diabetes incidence has profound implications for health systems and for people living with diabetes. Guidelines have established clinical targets but there may be variation in clinical outcomes including HbA1c, based on location and practice size. Investigating this variation may help identify factors amenable to systemic improvement interventions. The aims of this study were to identify centre-specific and patient-specific factors associated with variation in HbA1c levels and to determine how these associations contribute to variation in performance across diabetes centres.
Methods:
This cross-sectional study analysed data for 5,872 people with type 1 (n = 1,729) or type 2 (n = 4,143) diabetes mellitus collected through the Australian National Diabetes Audit (ANDA). A linear mixed-effects model examined centre-level and patient-level factors associated with variation in HbA1c levels.
Results:
Mean age was: 43±17 years (type 1), 64±13 (type 2); median disease duration: 18 years (10,29) (type 1), 12 years (6,20) (type 2); female: 52% (type 1), 45% (type 2). For people with type 1 diabetes, volume of patients was associated with increases in HbA1c (p = 0.019). For people with type 2 diabetes, type of centre was associated with reduction in HbA1c (p <0.001), but location and patient volume were not. Associated patient-level factors associated with increases in HbA1c included past hyperglycaemic emergencies (type 1 and type 2, p<0.001) and Aboriginal and Torres Strait Islander status (type 2, p<0.001). Being a non-smoker was associated with reductions in HbA1c (type 1 and type 2, p<0.001).
Conclusions:
Centre-level and patient-level factors were associated with variation in HbA1c, but patient-level factors had greater impact. Interventions targeting patient-level factors conducted at a centre level including sick-day management, smoking cessation programs and culturally appropriate diabetes education for and Aboriginal and Torres Strait Islander peoples may be more important for improving glycaemic control than targeting factors related to the Centre itself.


Related Concept Videos
 01:11
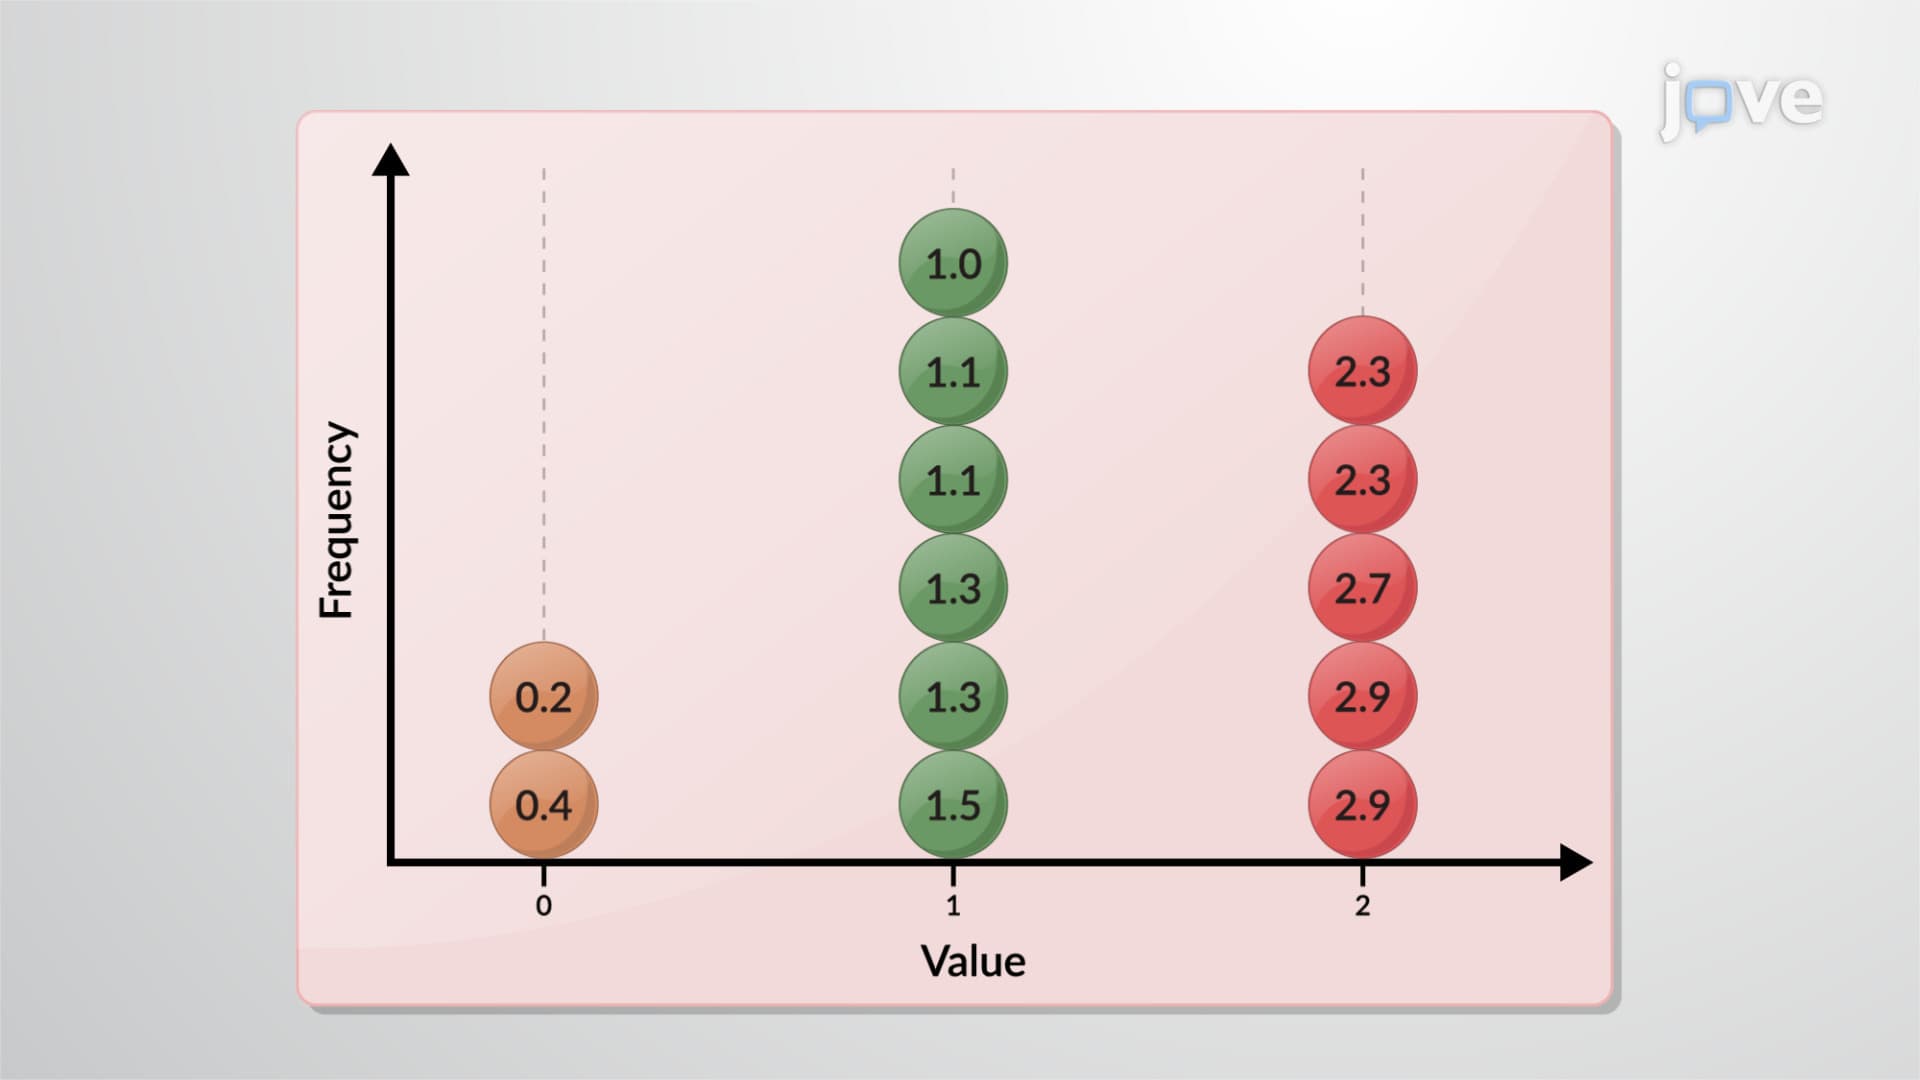
Variability: Analysis
The range is a simple measure of variability, indicating the difference between the highest and...
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:52
Regression Toward the Mean
 01:15
Diabetes: Symptoms, Diagnosis, and Complications
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:19
Testing a Claim about Standard Deviation
The hypothesis testing for the claim of population standard deviation (or variance) requires the data and samples to be random and unbiased. The population distribution also must be normal. There is no specific requirement on the sample size as the estimation is based on the chi-square distribution.
As a first step, the hypothesis (null and alternative) concerning the claim about...