Related Experiment Video
Updated: Oct 4, 2025


Generation of Hypoparathyroid Rats via Carbon-Nanoparticle-Assisted Parathyroidectomy
Published on: July 14, 2023
Parathyroid hormone and phosphate homeostasis in patients with Bartter and Gitelman syndrome: an international
Maartje F A Verploegen1, Rosa Vargas-Poussou2, Stephen B Walsh3
1Department of Nephrology, Radboud University Medical Center, Nijmegen, The Netherlands.

Background:
Small cohort studies have reported high parathyroid hormone (PTH) levels in patients with Bartter syndrome and lower serum phosphate levels have anecdotally been reported in patients with Gitelman syndrome. In this cross-sectional study, we assessed PTH and phosphate homeostasis in a large cohort of patients with salt-losing tubulopathies.
Methods:
Clinical and laboratory data of 589 patients with Bartter and Gitelman syndrome were provided by members of the European Rare Kidney Diseases Reference Network (ERKNet) and the European Society for Paediatric Nephrology (ESPN).
Results:
A total of 285 patients with Bartter syndrome and 304 patients with Gitelman syndrome were included for analysis. Patients with Bartter syndrome type I and II had the highest median PTH level (7.5 pmol/L) and 56% had hyperparathyroidism (PTH >7.0 pmol/L). Serum calcium was slightly lower in Bartter syndrome type I and II patients with hyperparathyroidism (2.42 versus 2.49 mmol/L; P = .038) compared to those with normal PTH levels and correlated inversely with PTH (rs -0.253; P = .009). Serum phosphate and urinary phosphate excretion did not correlate with PTH. Overall, 22% of patients had low serum phosphate levels (phosphate-standard deviation score < -2), with the highest prevalence in patients with Bartter syndrome type III (32%). Serum phosphate correlated with tubular maximum reabsorption of phosphate/glomerular filtration rate (TmP/GFR) (rs 0.699; P < .001), suggesting renal phosphate wasting.
Conclusions:
Hyperparathyroidism is frequent in patients with Bartter syndrome type I and II. Low serum phosphate is observed in a significant number of patients with Bartter and Gitelman syndrome and appears associated with renal phosphate wasting.
More Related Videos
 07:13
Two Techniques to Create Hypoparathyroid Mice: Parathyroidectomy Using GFP Glands and Diphtheria-Toxin-Mediated Parathyroid Ablation
Published on: March 14, 2017
 07:12
Establishment of a Simple and Effective Rat Model for Intraoperative Parathyroid Gland Imaging
Published on: August 17, 2022
Related Concept Videos
 00:59
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by...
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:27
Roles of Electrolytes: Calcium and Phosphate
The calcium concentration in blood plasma is primarily...
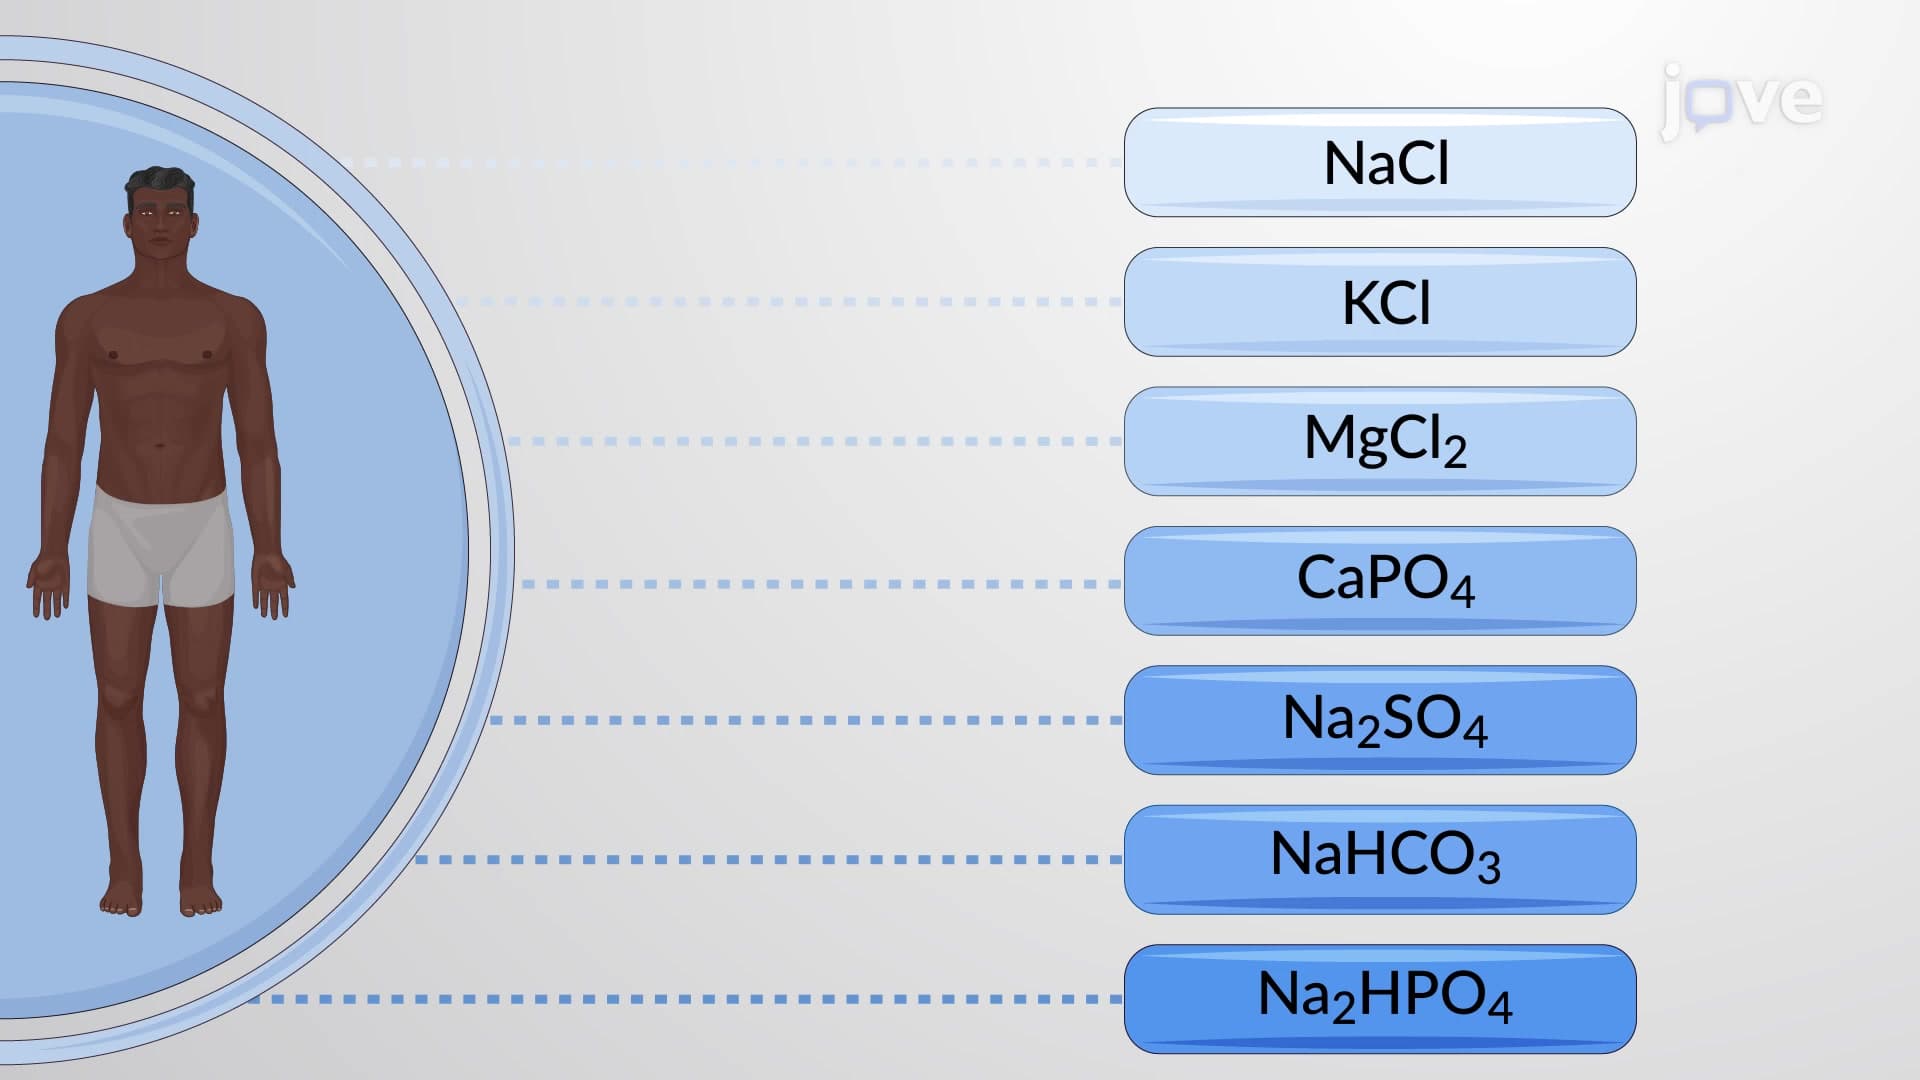 01:33
Introduction to Electrolytes
Role of Sodium
One...
 01:21
Skeleton and Calcium Homeostasis
 01:22
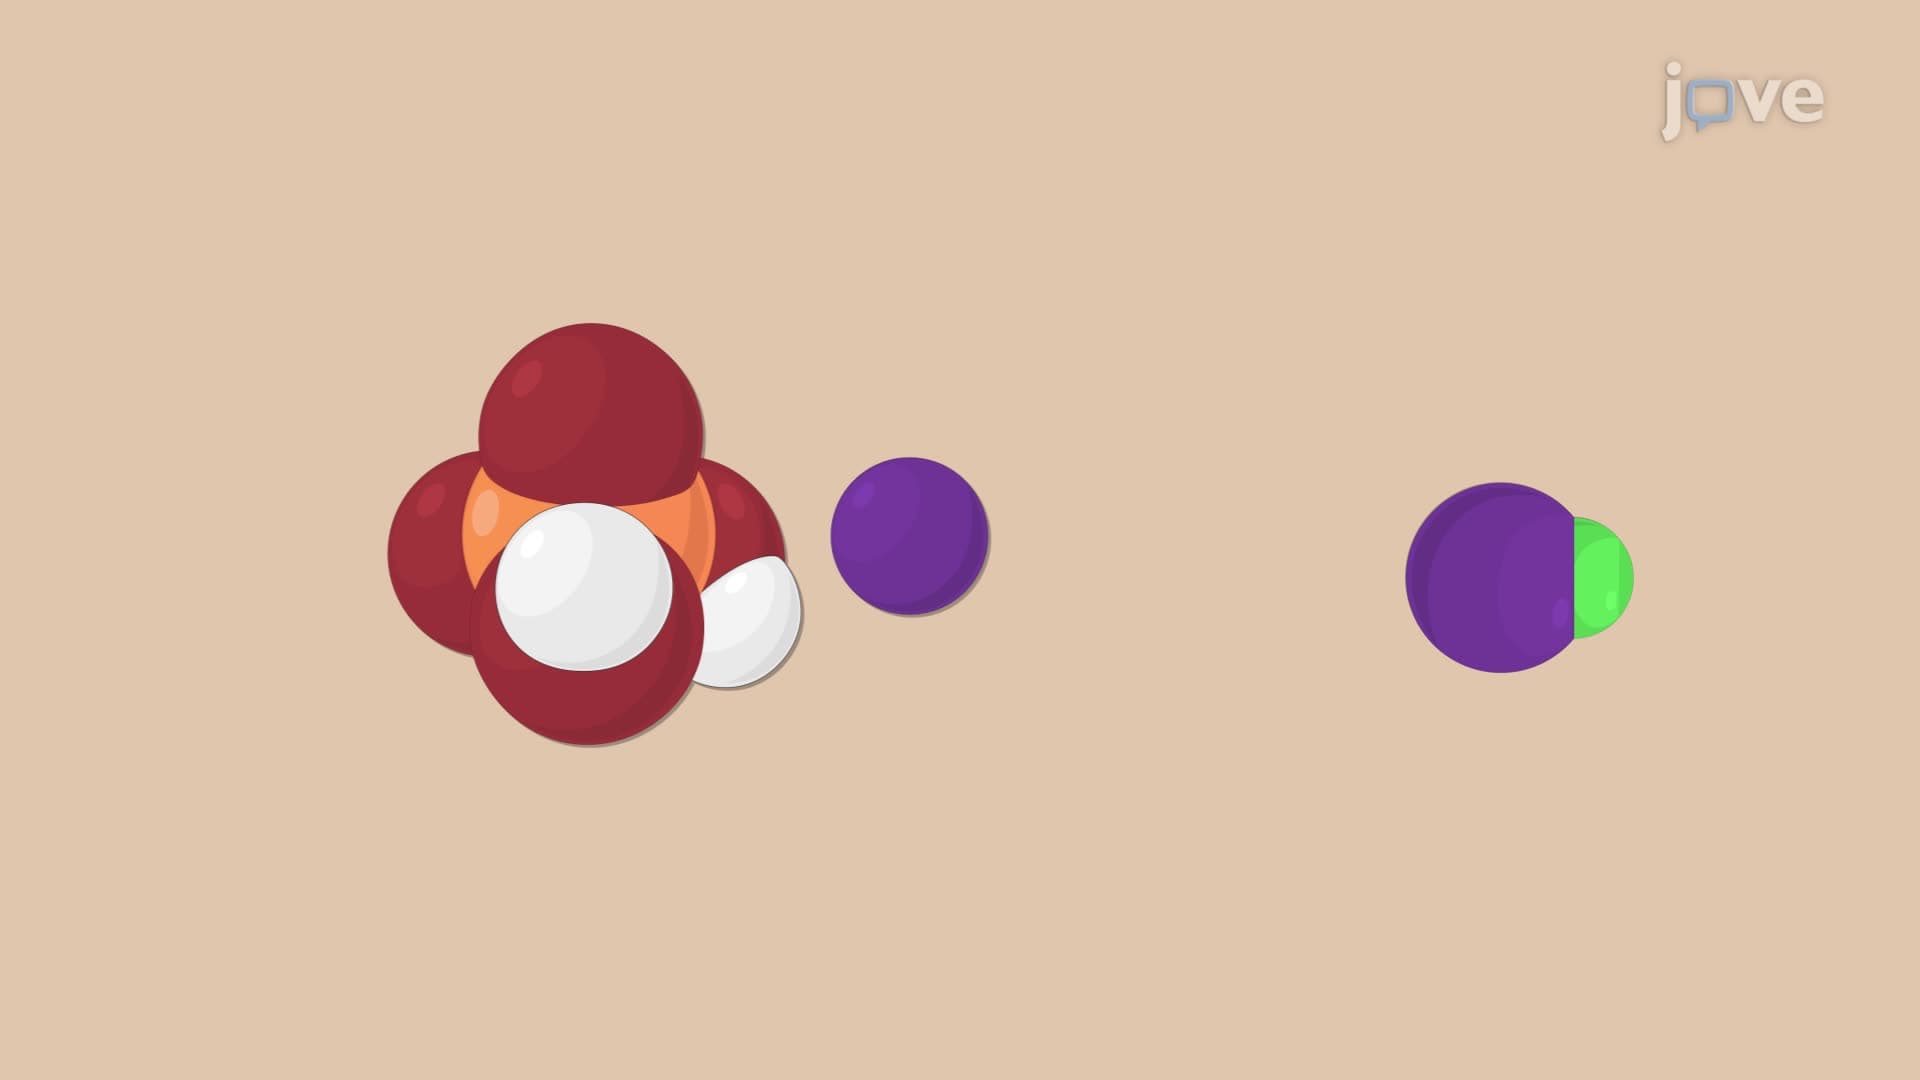
Phosphate Buffer
Sodium dihydrogen phosphate does not fully dissociate in neutral or acidic solutions. When a strong base, such as sodium hydroxide (NaOH), is introduced into the solution, sodium dihydrogen phosphate...