Related Experiment Video
Updated: Oct 4, 2025

Calcification of Vascular Smooth Muscle Cells and Imaging of Aortic Calcification and Inflammation
Published on: May 31, 2016
Serum Calcification Propensity and Calcification of the Abdominal Aorta in Patients With Primary Aldosteronism
Marta Kantauskaite1, Katharina Bolten1, Matthias Boschheidgen2
1Department of Nephrology, Medical Faculty, University Hospital Düsseldorf, Heinrich-Heine-University Düsseldorf, Düsseldorf, Germany.

Insights
Primary aldosteronism (PA) patients with high aldosterone levels show lower serum calcification propensity (T50). Lower T50 values correlate with increased vascular calcification and cardiovascular risk in PA, suggesting T50 as a potential modifiable risk factor.
Area of Science:
- Cardiology
- Endocrinology
- Vascular Biology
Background:
- Primary aldosteronism (PA) significantly increases cardiovascular disease (CVD) risk and mortality compared to primary hypertension, primarily due to excess aldosterone's vascular effects.
- Serum calcification propensity, measured by the novel T50 test, is a predictor of cardiovascular risk, with lower T50 values indicating higher risk.
- Vascular calcification is a key contributor to CVD, and understanding its predictors in conditions like PA and resistant hypertension (RH) is crucial.
Purpose of the Study:
- To investigate serum calcification propensity (T50) and its association with vascular calcification in patients with PA and resistant hypertension (RH).
- To explore the relationship between aldosterone-to-renin ratio (ARR) and T50 values in PA patients.
- To assess the impact of treatment (adrenalectomy or medical) on T50 values and identify factors associated with changes in T50.
Main Methods:
- T50 measurements were conducted at baseline and during follow-up in 66 PA patients and 28 RH patients.
- Abdominal aortic calcification was quantified using the Agatston score.
- Associations between T50, aldosterone-to-renin ratio, atherosclerotic cardiovascular disease (ACSVD) scores, HDL levels, serum calcium, magnesium, phosphate, and estimated glomerular filtration rate (eGFR) were analyzed.
Main Results:
- No significant difference in baseline T50 values was observed between PA and RH groups.
- In PA patients, higher aldosterone-to-renin ratios were associated with lower T50 values, and lower T50 values correlated with increased abdominal aortic calcification and higher ACSVD scores.
- Treatment did not increase T50 values; a decrease in T50 post-intervention in PA was linked to higher baseline serum calcium and altered magnesium/phosphate levels, while in RH, it was associated with lower baseline eGFR.
Conclusions:
- A high aldosterone-to-renin ratio is associated with reduced serum calcification propensity (low T50) in primary aldosteronism.
- Lower T50 values are linked to greater vascular calcification and higher cardiovascular risk scores in PA patients.
- Serum calcification propensity (T50) may represent a novel, modifiable risk factor for cardiovascular disease in primary aldosteronism.
Abstract:
Patients with primary aldosteronism (PA) are more susceptible to cardiovascular disease and mortality than patients with primary hypertension. This is mostly attributed to excess production of aldosterone and its effects on the development of vascular injury. A novel functional test (T50) measures serum calcification propensity. Lower T50-values predict higher cardiovascular risk. We investigated serum calcification propensity and vascular calcification in PA and resistant hypertension (RH). T50 measurement was performed in patients with PA (n = 66) and RH (n = 28) at baseline and after 403 (279-640) and 389 (277-527) days of treatment. No significant differences in T50-values were observed between the groups (371 ± 65 and 382 ± 44 min, in PA and RH group, respectively, p > 0.05). However, higher aldosterone-to-renin ratios were associated with lower T50-values in PA-patients (r -0.282, p < 0.05). Furthermore, lower T50-values were associated with increased abdominal aortic calcification measured by Agatston score in PA (r -0.534, p < 0.05). In both, PA and RH, higher atherosclerotic cardiovascular disease (ACSVD) scores (r -0.403, p < 0.05) and lower HDL (r 0.469, p < 0.05) was related to lower T50-values in a linear regression model. Adrenalectomy or medical treatment did not increase T50-values. In comparison to patients with stable T50-values, PA patients with a decrease in T50 after intervention had higher serum calcium concentrations at baseline (2.24 ± 0.11 vs. 2.37 ± 0.10 mmol/l, p < 0.05). This decline of T50-values at follow-up was also associated with a decrease in serum magnesium (-0.03 ± 0.03 mmol/l, p < 0.05) and an increase in phosphate concentrations (0.11 ± 0.11 mmol/l, p < 0.05). Resistant hypertension patients with a decrease in T50-values at follow-up had a significantly lower eGFR at baseline. In summary, these data demonstrate an association between a high aldosterone-to-renin ratio and low T50-values in PA. Moreover, lower T50-values are associated with higher ACSVD scores and more pronounced vascular calcification in PA. Thus, serum calcification propensity may be a novel modifiable risk factor in PA.


Related Concept Videos
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:21
Skeleton and Calcium Homeostasis
 00:51
Synthesis and Functions of Calcitonin
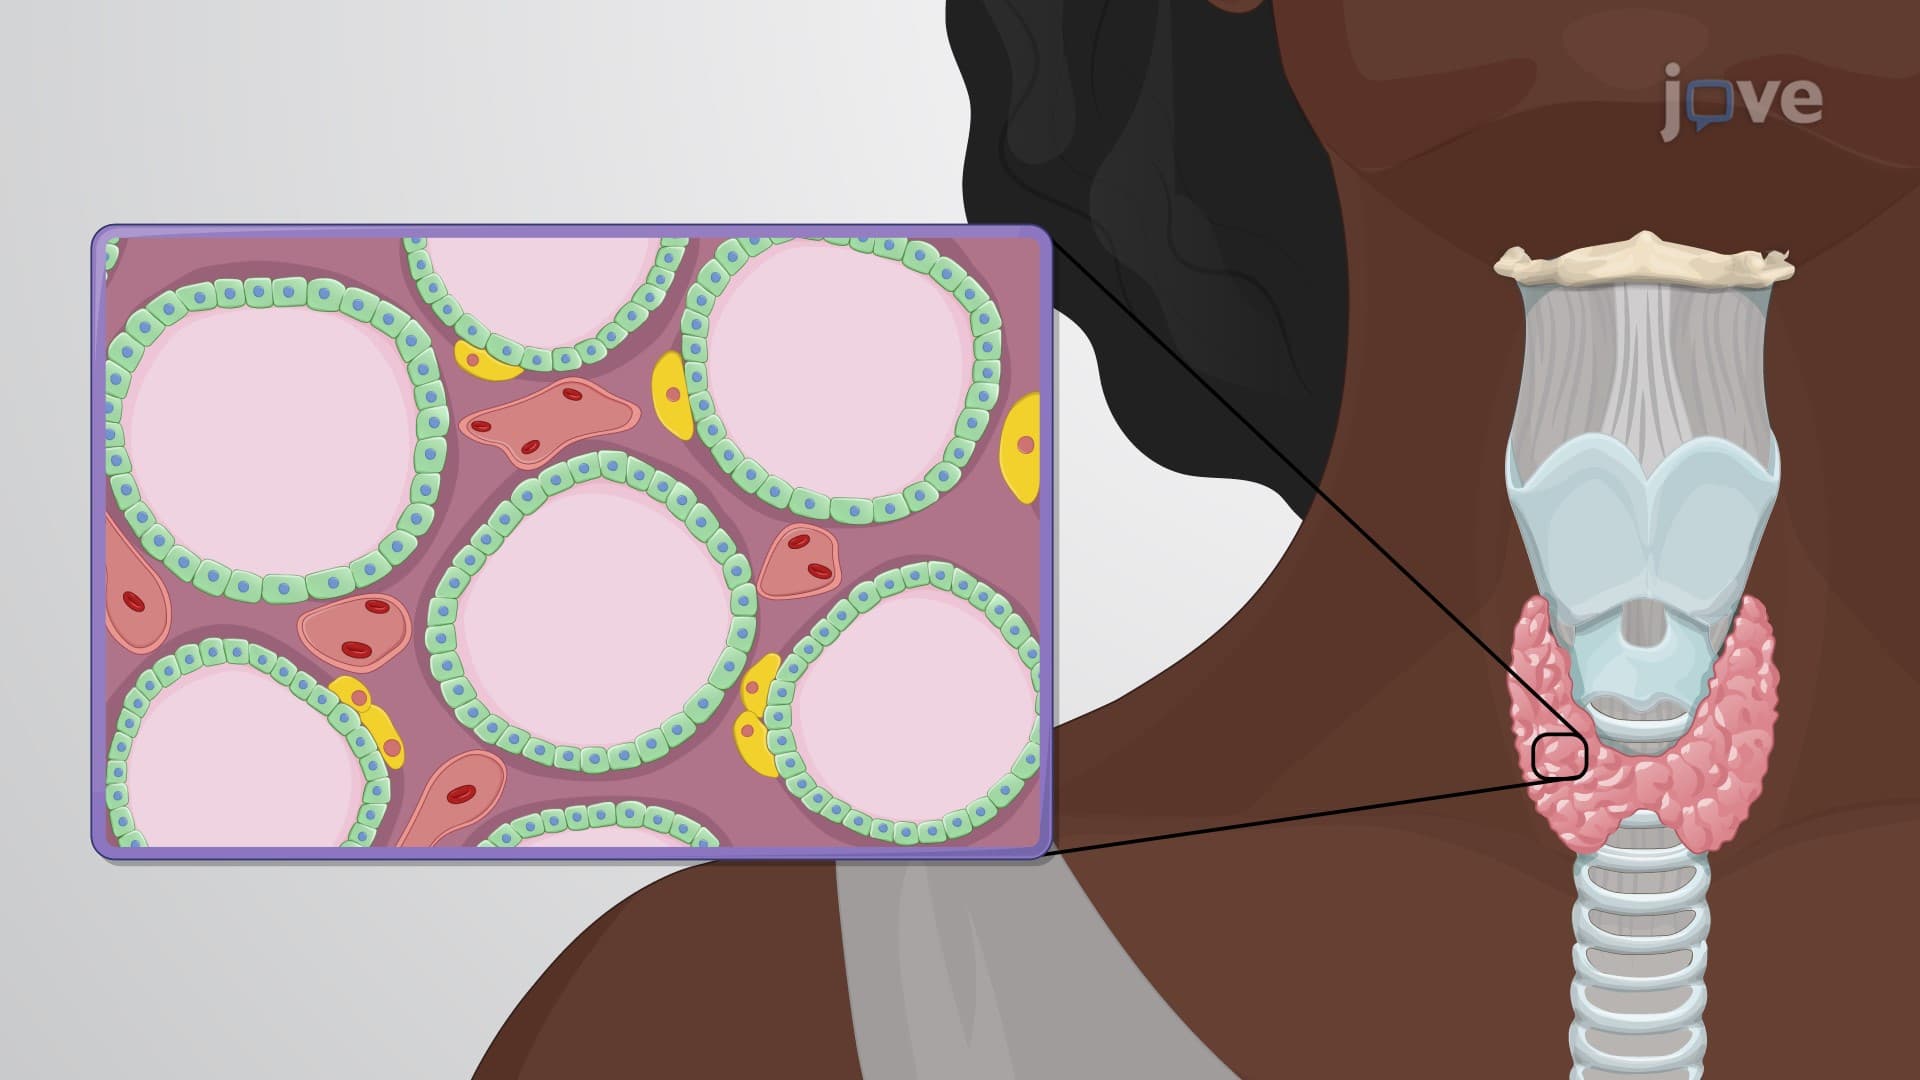
The exact mechanisms by which calcitonin operates in calcium homeostasis remain elusive, but its significance is evident in several vital...
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation