Related Experiment Video
Updated: Oct 4, 2025
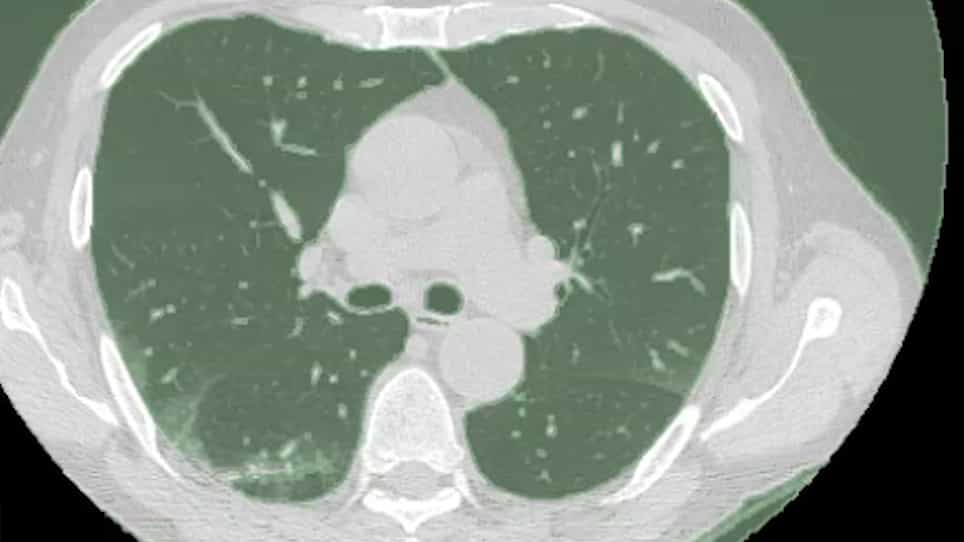

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Adjusting D-dimer to Lung Disease Extent to Exclude Pulmonary Embolism in COVID-19 Patients (Co-LEAD)
Benjamin Planquette1,2,3,4, Lina Khider2,5,6, Alice Le Berre7
1Innovative Therapies in Haemostasis, Université de Paris, INSERM, Paris, France.

Insights
A new algorithm (Co-LEAD) safely excludes pulmonary embolism (PE) in coronavirus disease 2019 (COVID-19) patients using adjusted D-dimer thresholds based on lung damage. This approach can reduce the need for CT pulmonary angiography (CTPA).
Area of Science:
- Pulmonary Medicine
- Infectious Diseases
- Diagnostic Imaging
Background:
- D-dimer testing is valuable for excluding pulmonary embolism (PE).
- Its specificity is reduced in coronavirus disease 2019 (COVID-19) patients, leading to increased computed tomography pulmonary angiography (CTPA) use.
- A need exists for improved diagnostic strategies in COVID-19 patients with suspected PE.
Purpose of the Study:
- To develop and validate a new algorithm (Co-LEAD) to optimize D-dimer thresholds for PE exclusion in COVID-19 patients.
- To assess the algorithm's safety and potential to reduce CTPA utilization.
Main Methods:
- A retrospective, multicenter cohort study of 774 COVID-19 patients with suspected PE.
- A D-dimer threshold adjusted for lung damage extent (<50% or ≥50%) was derived in a patient set (n=337).
- The algorithm's safety and performance were validated in an independent set (n=337).
Main Results:
- The Co-LEAD algorithm demonstrated high sensitivity (98.2% derivation, 96.7% validation) for PE exclusion.
- Specific D-dimer thresholds (900 ng/mL or 1700 ng/mL) based on lung damage extent were established.
- The algorithm could potentially allow 30.4% of patients to avoid CTPA, with a negative likelihood ratio of 0.06-0.08.
Conclusions:
- The Co-LEAD algorithm provides a safe method for excluding PE in COVID-19 patients.
- Implementation of this algorithm may significantly reduce the reliance on CTPA in this patient population.
- Further prospective studies are recommended to confirm these findings.
Objective:
D-dimer measurement is a safe tool to exclude pulmonary embolism (PE), but its specificity decreases in coronavirus disease 2019 (COVID-19) patients. Our aim was to derive a new algorithm with a specific D-dimer threshold for COVID-19 patients.
Methods:
We conducted a French multicenter, retrospective cohort study among 774 COVID-19 patients with suspected PE. D-dimer threshold adjusted to extent of lung damage found on computed tomography (CT) was derived in a patient set (n = 337), and its safety assessed in an independent validation set (n = 337).
Results:
According to receiver operating characteristic curves, in the derivation set, D-dimer safely excluded PE, with one false negative, when using a 900 ng/mL threshold when lung damage extent was <50% and 1,700 ng/mL when lung damage extent was ≥50%. In the derivation set, the algorithm sensitivity was 98.2% (95% confidence interval [CI]: 94.7-100.0) and its specificity 28.4% (95% CI: 24.1-32.3). The negative likelihood ratio (NLR) was 0.06 (95% CI: 0.01-0.44) and the area under the curve (AUC) was 0.63 (95% CI: 0.60-0.67). In the validation set, sensitivity and specificity were 96.7% (95% CI: 88.7-99.6) and 39.2% (95% CI: 32.2-46.1), respectively. The NLR was 0.08 (95% CI; 0.02-0.33), and the AUC did not differ from that of the derivation set (0.68, 95% CI: 0.64-0.72, p = 0.097). Using the Co-LEAD algorithm, 76 among 250 (30.4%) COVID-19 patients with suspected PE could have been managed without CT pulmonary angiography (CTPA) and 88 patients would have required two CTs.
Conclusion:
The Co-LEAD algorithm could safely exclude PE, and could reduce the use of CTPA in COVID-19 patients. Further prospective studies need to validate this strategy.
Related Concept Videos
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:27
Pulmonary Embolism III: Nursing Management
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:29
Pulmonary Embolism I: Introduction
 01:29
Venous Thrombosis III: Interprofessional Care
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies