Related Experiment Video
Updated: Oct 3, 2025
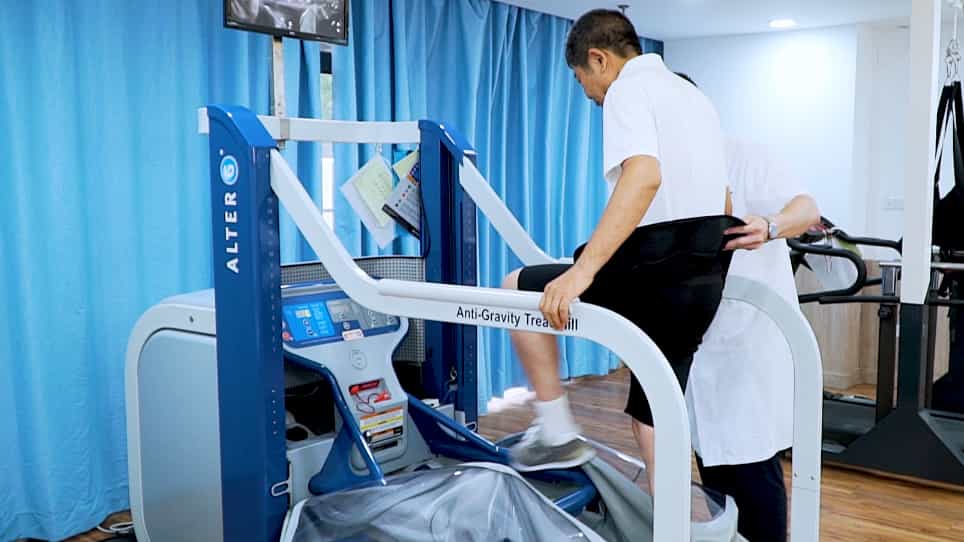
The Lower Body Positive Pressure Treadmill for Knee Osteoarthritis Rehabilitation
Published on: July 22, 2019
Does Blood Flow Restriction Therapy Improve Leg Strength in Patients With a Painful Total Knee Arthroplasty?
Isaac B Majors1, Simon C Mears1, Christopher K Oholendt2
1Department of Orthopaedic Surgery, University of Arkansas for Medical Sciences, Little Rock, AR.

Background:
Blood flow restriction (BFR) therapy has been proposed to help patients build strength with fewer repetitions than standard physical therapy (PT). We sought to determine if BFR would improve quadriceps and hamstring strength in patients with instability and perceived weakness >1 year after primary total knee arthroplasty (TKA).
Methods:
We retrospectively reviewed 48 patients with painful TKAs and flexion instability as well as quadriceps and hamstring weakness who performed a 6-week PT program and received isokinetic strength measurements (ISMs). Thirty-six patients completed a standard PT program (non-BFR) and 12 patients completed a BFR regimen. ISMs were taken before and after PT to quantify quadriceps and hamstring power, torque, and work compared to the contralateral leg. Statistical analysis was conducted on pre-PT and post-PT ISMs and decisions for revision surgery.
Results:
There were no differences in ISMs after PT between the BFR and non-BFR groups. The non-BFR group showed statistically significant strength improvements in flexion but not extension (+28.7%-32.8%, P = .0145-.255). Although no significant difference was found in the BFR group, they saw improvements in all extension strength metrics (19.4%-23.4%, P = .3315-.3901) and flexion (25.7%-29.9%, P = .1994-.2392). No difference was observed between the groups in the rates of subsequent revision TKA (8.3% vs 16.7%, P = .3362).
Conclusion:
BFR did not improve quadriceps and hamstring strength compared to PT alone in patients with instability and weakness after TKA. Over 80% of total patients chose to avoid revision TKA after completion of focused PT with or without BFR.
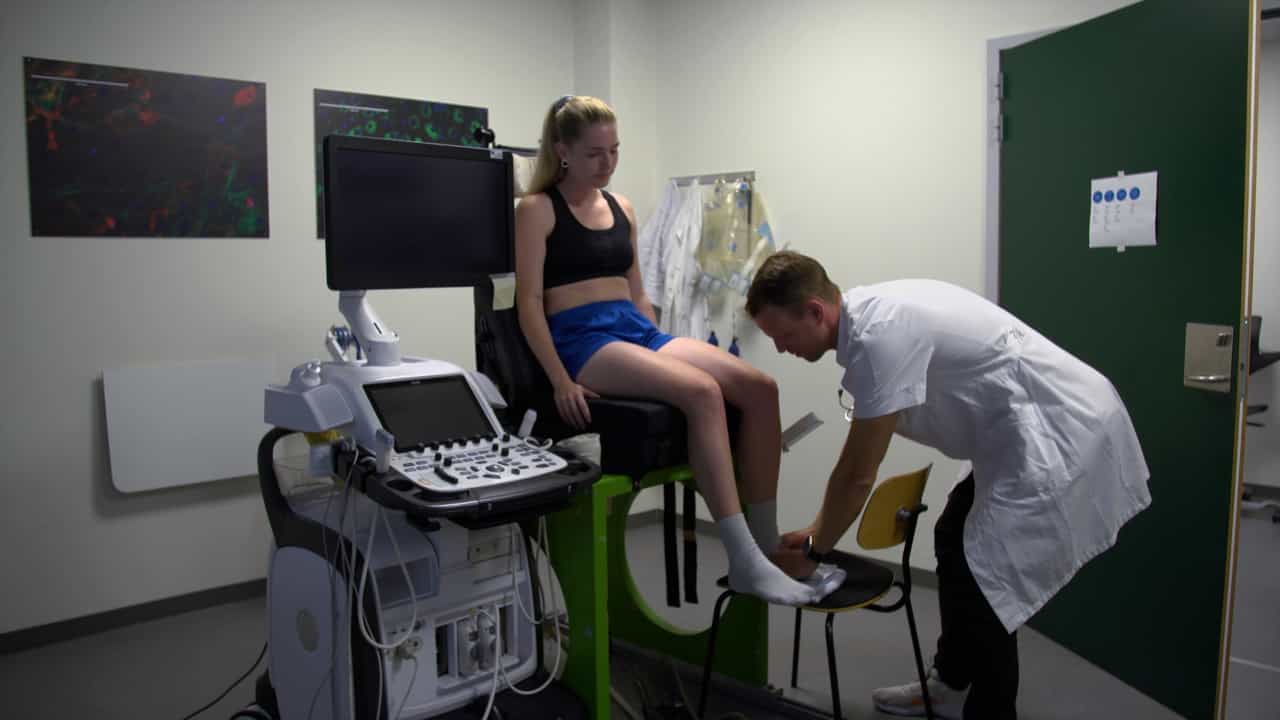

Related Concept Videos
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:26
Peripheral Artery Disease IV: Nursing Management
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:29
Venous Thrombosis III: Interprofessional Care
 01:23
Treatment for Pulmonary Arterial Hypertension: Prostacyclin Receptor Agonists
These agonists bind to the IPR receptor situated on the plasma membrane of the pulmonary artery smooth muscle cells. This binding triggers a cascade of reactions known as the GS-AC-cAMP-PKA pathway. This pathway results in the relaxation of smooth muscle...