Impact of pre-existing right or left bundle branch block on patients undergoing surgical aortic valve replacement
Related Experiment Video
Updated: Oct 3, 2025
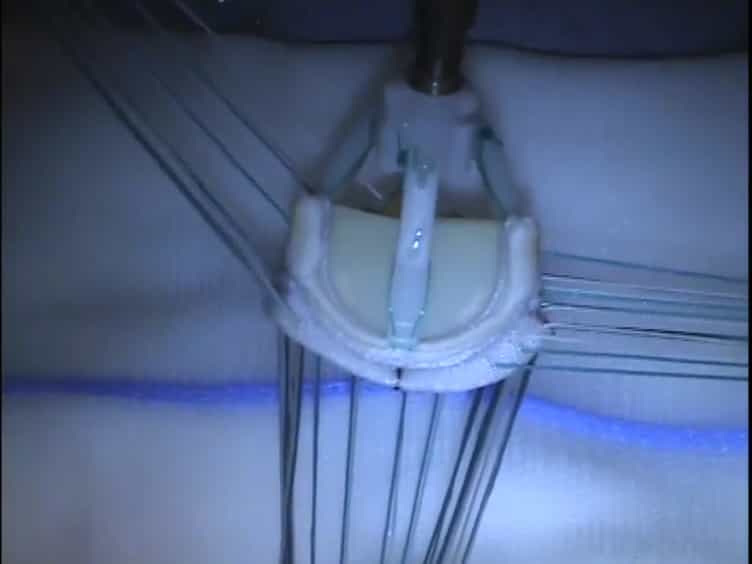
Technique and Patient Selection Criteria of Right Anterior Mini-Thoracotomy for Minimal Access Aortic Valve Replacement
Published on: March 26, 2018
Eilon Ram1,2, Yael Peled3, Irena Sarantsev1
1Department of Cardiac Surgery, Sheba Medical Center, Tel Hashomer, Sackler School of Medicine, Tel Aviv University, Tel Aviv, Israel.

Insights
Pre-existing bundle branch block increases pacemaker implantation and mortality risk after aortic valve replacement. Patients with bundle branch block face poorer long-term survival compared to those without this conduction abnormality.
Area of Science:
- Cardiology
- Cardiac Surgery
- Electrophysiology
Background:
- Pre-existing bundle branch block (BBB) is a common finding in patients undergoing aortic valve (AV) replacement.
- Limited contemporary data exist on the prognostic impact of BBB on clinical outcomes post-AV replacement.
Purpose of the Study:
- To evaluate the impact of pre-existing left or right bundle branch block on clinical outcomes in patients undergoing AV replacement.
Main Methods:
- Retrospective analysis of 2704 patients undergoing AV replacement between 2004 and 2020.
- Comparison of clinical outcomes between patients with and without pre-existing bundle branch block.
Main Results:
- Patients with pre-existing bundle branch block (7.5%) had higher in-hospital mortality (5.9% vs 2.9%, P=0.032) and significantly more new pacemaker implantations (28.6% vs 7.5% vs 2.8%, P<0.001).
- Left bundle branch block was associated with higher mortality (11.9% vs 4.3%, P=0.003) compared to right bundle branch block.
- The 10-year cumulative survival rate was lower for patients with bundle branch block (76.8% vs 82.8%, P=0.042).
Conclusions:
- Pre-existing bundle branch block is associated with increased pacemaker implantation and all-cause mortality after AV replacement.
- Patients with bundle branch block have worse long-term survival following AV replacement compared to those without conduction disturbances.
Objectives:
Contemporary data on the prognostic impact of pre-existing left or right bundle branch block on clinical outcomes after aortic valve (AV) replacement are limited. The aim of this study was to evaluate the impact of pre-existing bundle branch block on clinical outcomes in patients undergoing AV replacement.
Methods:
Data from patients who underwent AV replacement surgery between 2004 and 2020 were obtained from our departmental database.
Results:
Of the 2704 study patients, 203 (7.5%) had pre-existing bundle branch block and 2501 (92.5%) had normal atrioventricular conduction. The mean age was 68 (13) years, 1697 (63%) were male and 683 (25%) had a unicuspid or bicuspid AV. The in-hospital mortality rate was higher in patients with pre-existing bundle branch block compared to those without on admission (5.9% vs 2.9%, P = 0.032), and more frequent in patients with left compared with right bundle branch block (11.9% vs 4.3%, P = 0.003). New pacemaker implantation was most frequent in those patients with pre-existing left bundle branch block, followed by right and no bundle branch block on admission (28.6% vs 7.5% vs 2.8% respectively, P < 0.001; odds ratio 4.96 95% confidence interval 2.96-8.08, P < 0.001). The 10-year cumulative survival rate was lower in patients with bundle branch block compared with patients with no bundle branch block (76.8% vs 82.8%, log-rank P < 0.001; hazard ratio 0.73, confidence interval 0.54-0.99, P = 0.042).
Conclusions:
This study indicates that patients with pre-existing bundle branch block have a higher incidence of pacemaker implantation and all-cause mortality after AV replacement compared with patients without a conduction disturbance.
Related Concept Videos
 01:25
Aortic Regurgitation III: Medical Management
 01:22
Aneurysm IV: Nursing Management
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:15
Aortic Regurgitation I: Introduction
 01:22
Mitral Stenosis I: Introduction
 01:26
Mitral Stenosis III: Medical Management