Related Experiment Video
Updated: Oct 3, 2025
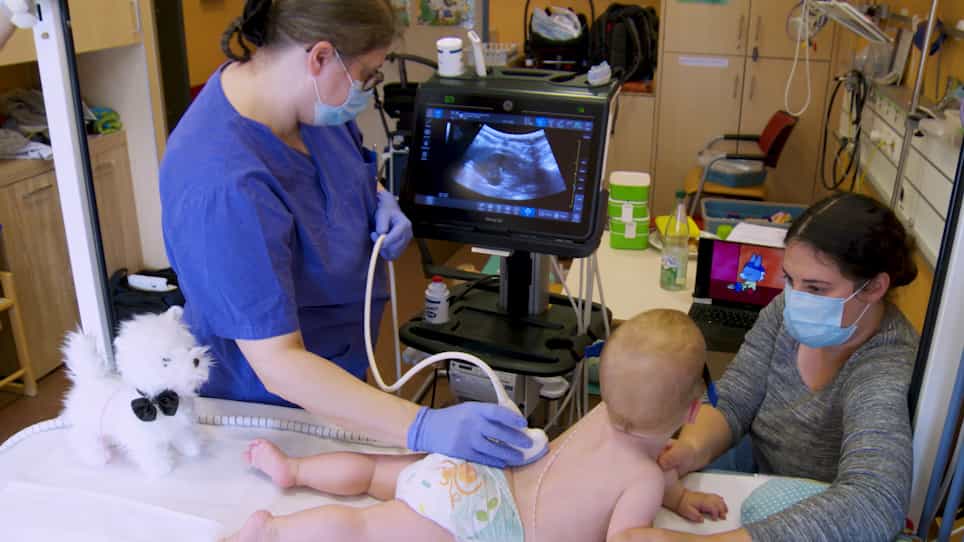

How to Administer Near-Infrared Spectroscopy in Critically ill Neonates, Infants, and Children
Published on: August 19, 2020
Validation of the Masimo O3™ regional oximetry device in pediatric patients undergoing cardiac surgery
Ji-Hyun Lee1, In-Sun Song1, Pyoyoon Kang1
1Department of Anesthesiology and Pain Medicine, Seoul National University Hospital, Seoul National University College of Medicine, # 101 Daehakno, Jongnogu, Seoul, 03080, Republic of Korea.

Abstract:
We assessed the accuracy of Masimo O3™ regional cerebral oxygen saturation (rSO2) readings by comparing them with reference values and evaluated the relationship between rSO2 and somatic tissue oxygen saturation (StO2) in children undergoing cardiac surgery. After anesthesia induction, pediatric sensors were applied to the forehead and foot sole, and rSO2 and StO2 values were monitored continuously. Before cardiopulmonary bypass (CPB), FIO2 was set to 0.2, 0.5, and 0.8 serially every 15 min. After CPB, FIO2 was reversed. The reference values (SavO2) were calculated by combining arterial (SaO2) and central venous oxygen saturation (SvO2) readings from the arterial and central lines, respectively (0.7 [Formula: see text] SvO2 + 0.3 [Formula: see text] SaO2). In total, 265 pairs of rSO2/StO2 and SavO2 from 49 patients were analyzed. The bias, standard deviation (SD), standard error (SE), and root mean squared error (RMSE) of rSO2 were 2.6%, 4.5%, 0.3%, and 4.3%, respectively. The limits of agreement ranged from -6.3% to 11.6%. Trend accuracy analysis yielded a relative mean error of -1.4%, with an SD of 4.3%, SE of 0.2%, and RMSE of 3.9%. According to multiple linear regression analysis, the application of CPB, FIO2, Hb level, and tip location of the central venous catheter influenced the bias (all P < 0.05). Furthermore, the correlation between rSO2 and StO2 was weak (r = 0.254). rSO2 readings by the Masimo O3™ device and pediatric sensor had good absolute and trending accuracies with respect to the calculated reference values in children undergoing cardiac surgery. rSO2 and StO2 cannot be used interchangeably.Clinical trial registration http://clinicaltrials.gov (number: NCT04208906).
More Related Videos
 14:28
Non-Invasive Monitoring of Microvascular Oxygenation and Reactive Hyperemia using Hybrid, Near-Infrared Diffuse Optical Spectroscopy for Critical Care
Published on: May 10, 2024
 07:51
Standardized Hemorrhagic Shock Induction Guided by Cerebral Oximetry and Extended Hemodynamic Monitoring in Pigs
Published on: May 21, 2019
Related Concept Videos
 01:24
Pulse Oximetry
Purpose
Average SpO2 values are greater than 95%. If the readings fall below 90%, it indicates that...
 01:19
Guidelines For Measuring Vital Signs
Before taking a patient's vital signs, a nurse would consider and assess the patient's comfort level and ensure appropriate equipment is available.
 01:19
Special considerations while measuring oxygen saturation
Ensuring accuracy in vital sign recordings while prioritizing patient comfort and minimizing anxiety is...
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:26
Oxygen Delivering System I: Nasal Cannula and Face Mask
Nasal Cannula
A nasal cannula is a lightweight tube split at one end into two prongs and placed in the nostrils. It is typically used to deliver low to medium levels of oxygen.
Suggested flow rate: The suggested flow rate for a nasal cannula typically ranges between 1 and 6 L/min.
Oxygen percentage setting:...