Related Experiment Video
Updated: Oct 3, 2025


Expired CO2 Measurement in Intubated or Spontaneously Breathing Patients from the Emergency Department
Published on: January 29, 2011
PCO2 gap, its ratio to arteriovenous oxygen content, ScvO2 and lactate in high-risk abdominal surgery patients: An
Enrique Guilherme1, Marie-Charlotte Delignette1, Hadrien Pambet1
1Department of Anaesthesiology and Critical Care, Croix Rousse University Hospital, Hospices Civils de Lyon, Lyon, France.

Background:
The difference between arterial and central venous carbon dioxide partial pressure (PCO2 gap), a marker of oxygen delivery (DO2) and oxygen consumption (VO2) adequacy, has been evaluated as a promising prognostic tool in intensive care unit (ICU) patients. We therefore sought to study the association between intraoperative PCO2 gap and postoperative complications (POC) in the perioperative setting of elective major abdominal surgery.
Methods:
We conducted a single-centre prospective observational study. All adult patients who underwent major planned abdominal surgery were eligible. PCO2 gap was measured every 2 h during surgery, at ICU admission and repeated 12 h and 24 h later. Severe POC within 28 days after surgery were defined as complications graded 3 or more according to Clavien-Dindo classification. Following a univariate analysis, a multivariable analysis using a logistic regression model was performed.
Results:
Ninety patients were included and divided into two groups according to the occurrence of POC. No significant difference was found between groups regarding baseline characteristics at inclusion. Thirty-nine (43%) patients developed postoperative complications. The median [IQR] intraoperative PCO2 gap was significantly higher in patients who had complications (6.5 [5.5-7.3] mmHg) compared to those who did not (5.0 [3.9-5.8] mmHg; p < 0.001). The area under the receiver operating characteristic curve for occurrence of POC was 0.78 for the PCO2 gap. After multivariable analysis, PCO2 gap was found independently associated with POC (OR: 14.9, 95% CI [4.68-60.1], p < 0.001) with a threshold value of 6.2 mmHg. The duration of surgery (OR: 1.01, 95% CI [1.00; 1.01], p = 0.04) and the need for vasoactive support during surgery (OR: 5.76, 95% CI [1.72; 24.1], p = 0.006) were also independently associated with POC.
Conclusion:
Intraoperative PCO2 gap is a relevant predictive factor of severe postoperative complications in high-risk elective surgery patients.
Trial Registration:
ClinicalTrials.gov, NCT03914976.
More Related Videos
 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
 07:28
Donor Posterior Atrial Flap Rotation for Left Atrial Cuff Reconstruction in Lung Transplantation
Published on: October 11, 2024
Related Concept Videos
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this...
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and...
 01:26
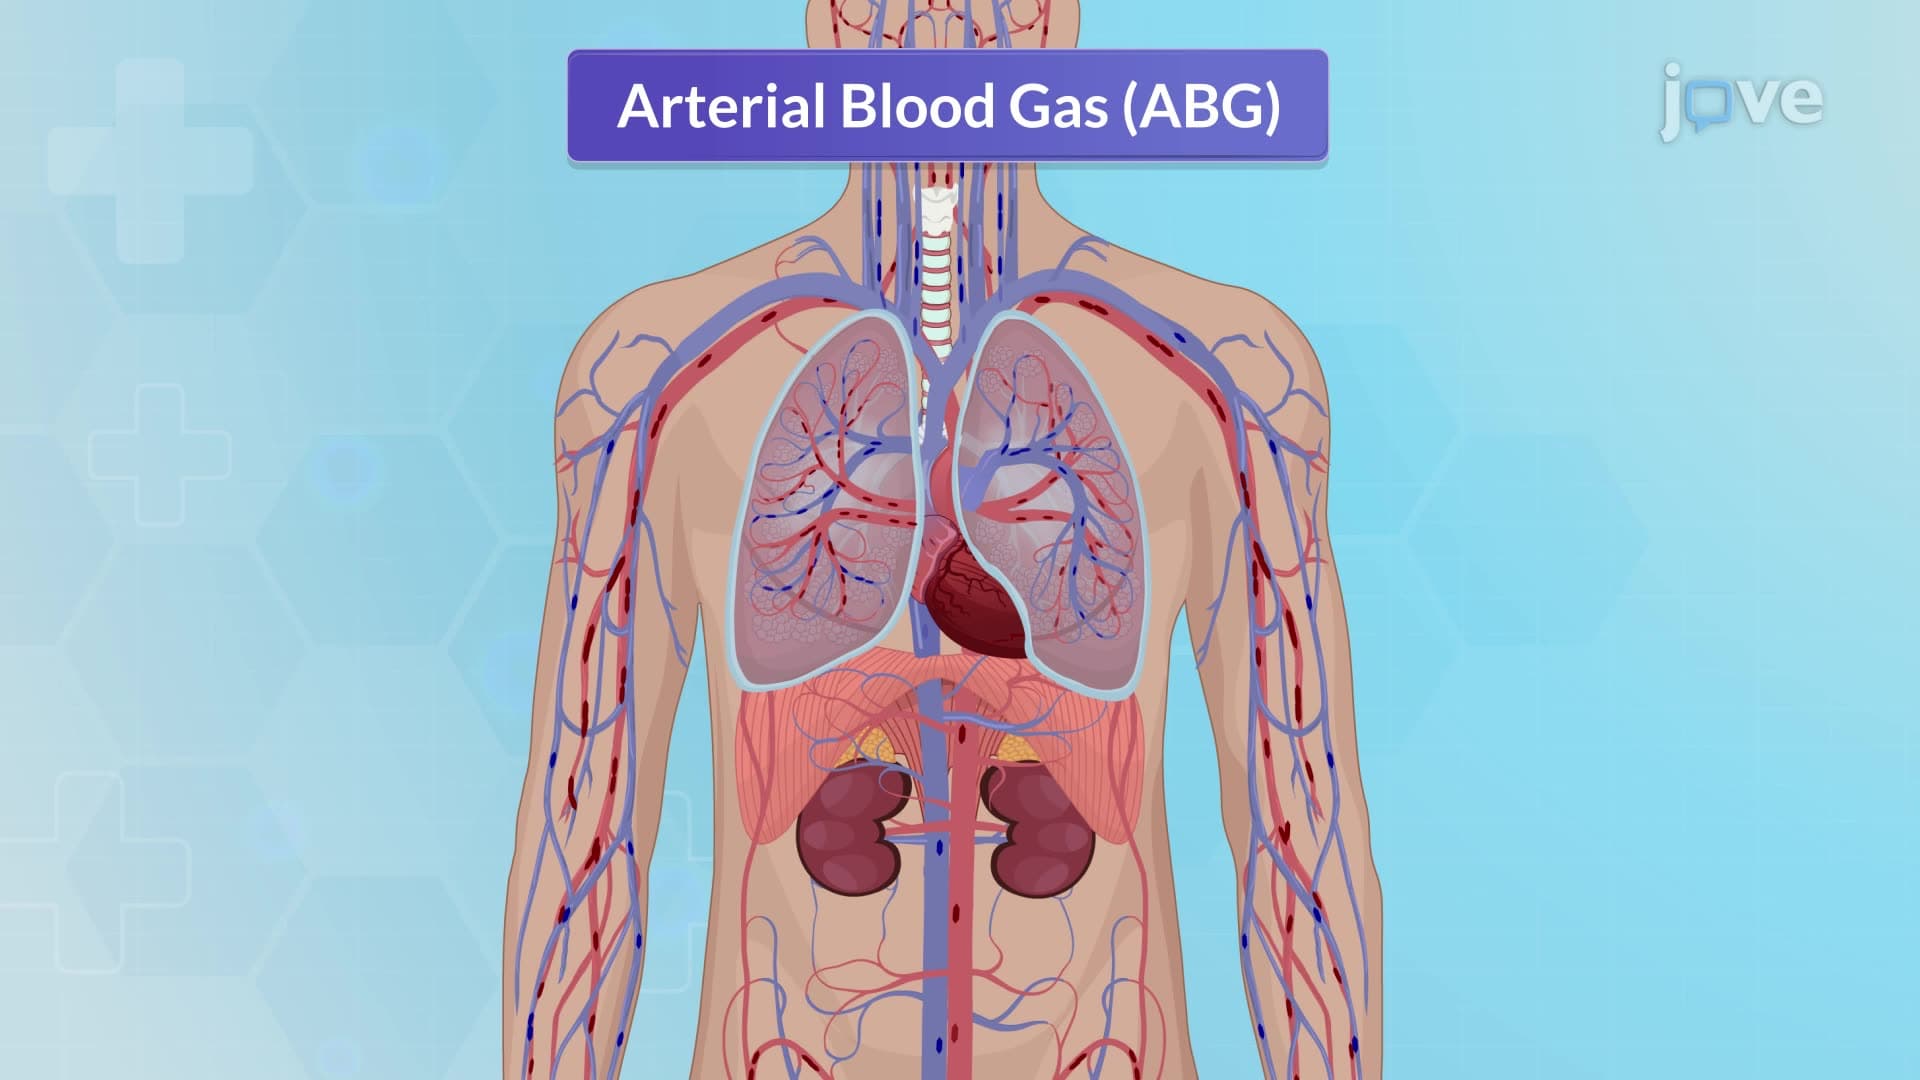
Blood Studies I: ABG and VBG
Arterial Blood Gas (ABG)
Arterial Blood Gas (ABG) studies are crucial for assessing the lungs' ability to supply oxygen and remove carbon dioxide, reflecting the patient's ventilation status. They also help understand the kidneys' capacity to...
 01:27
Oxygen Transport in the Blood
 01:19
Special considerations while measuring oxygen saturation
Ensuring accuracy in vital sign recordings while prioritizing patient comfort and minimizing anxiety is...
 01:18
Respiratory Regulation of Acid-Base Balance
When carbon dioxide levels increase in the blood, more H+ and HCO3⁻ are...