Related Experiment Video
Updated: Oct 3, 2025

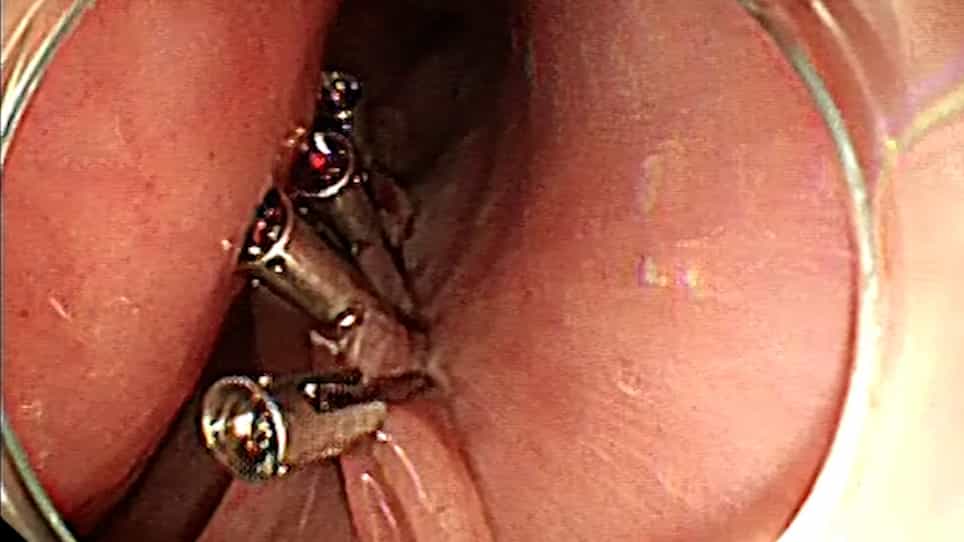
Robotic Myotomy and Partial Fundoplication for Achalasia
Published on: August 11, 2023
Characteristics of Achalasia Subtypes: Result of a Study in a Tertiary Hospital
Saba Alvand1, Behnaz Aghaee2, Zahra Momayez Sanat3
1Liver and Pancreatobiliary Diseases Research Center, Digestive Diseases Research Institute, Tehran University of Medical Sciences, Tehran, Iran.

Background:
With the appearance of enhancing high-resolution manometry (HRM), realizing the difference of achalasia symptoms between classified groups by HRM is an outcome of interest in areas with remote access to this device.
Methods:
All patients newly diagnosed with achalasia from January 2019 to March 2020 were enrolled in the study. All the patients were diagnosed via HRM after undergoing endoscopy to rule out pseudo-achalasia, and grouped based on the Chicago classification criteria and answered a questionnaire assessing relevant symptoms.
Results:
We included 62 patients recently diagnosed with achalasia with a mean age of 53.66 in males (n=30), and 45.4 in females (n=32). Mean time of diagnosis was 24 months. Thirty-seven percent were in type I, 50% in type II, and 13% in type III. Dysphagia and weight loss were higher in type III, while all other relevant symptoms were higher in type II, none of which, however, was statistically significant. Weight loss was reversely associated with duration of symptoms (Spearman correlation= -0.3, P=0.01), and this reverse association was more prominent in females (Spearman correlation= -0.47, P=0.009), type III (Spearman correlation= -0.74, P=0.03), and in the first clinical stages (Spearman correlation= -0.55, P=0.04) in sub analysis.
Conclusion:
Type II is the most common type of achalasia in this study. Unlike HRM classification, clinical manifestations alone cannot be used to group patients into different types. However, significant weight loss of the newly diagnosed subjects can become an indicator of on-time diagnosis of the patients.

Related Concept Videos
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...