Related Experiment Video
Updated: Oct 3, 2025

Robotic Myotomy and Partial Fundoplication for Achalasia
Published on: August 11, 2023
Elevated average maximum intrabolus pressure on high-resolution manometry is associated with esophageal dysmotility
Katelyn E Madigan1, J Shawn Smith2, Joni K Evans3
1Department of Medicine, Wake Forest School of Medicine, Medical Center Boulevard, Winston-Salem, NC, 27157, USA. kmadigan@wakehealth.edu.

Background:
Intrabolus pressure (IBP) recorded by high-resolution manometry (HRM) portrays the compartmentalized force on a bolus during esophageal peristalsis. HRM may be a reliable screening tool for esophageal dysmotility in patients with elevated average maximum IBP (AM-IBP). Timed barium esophagram (TBE) is a validated measure of esophageal emptying disorders, such as esophagogastric junction outflow obstruction and achalasia. This study aimed to determine if an elevated AM-IBP correlates with esophageal dysmotility on HRM and/or delayed esophageal emptying on TBE.
Methods:
A retrospective analysis of all HRM (unweighted sample n = 155) performed at a tertiary referral center from 09/2015-03/2017 yielded a case group (n = 114) with abnormal AM-IBP and a control group (n = 41) with a normal AM-IBP (pressure < 17 mmHg) as consistent with Chicago Classification 3. All patients received a standardized TBE, with abnormalities classified as greater than 1 cm of retained residual liquid barium in the esophagus at 1 and 5 min or as tablet retention after 5 min.
Results:
AM-IBP was significantly related to liquid barium retention (p = 0.003) and tablet arrest on timed barium esophagram (p = 0.011). A logistic regression model correctly predicted tablet arrest in 63% of cases. Tablet arrest on AM-IBP correlated with an optimal prediction point at 20.1 mmHg on HRM. Patients with elevated AM-IBP were more likely to have underlying esophageal dysmotility (95.6% vs. 70.7% respectively; p < 0.001), particularly esophagogastric junction outflow obstruction disorders. Elevated AM-IBP was associated with incomplete liquid bolus transit on impedance analysis (p = 0.002).
Conclusions:
Our findings demonstrate that an elevated AM-IBP is associated with abnormal TBE findings of esophageal tablet retention and/or bolus stasis. An abnormal AM-IBP (greater than 20.1 mm Hg) was associated with a higher probability of retaining liquid bolus or barium tablet arrest on TBE and esophageal dysmotility on HRM. This finding supports the recent incorporation of IBP in Chicago Classification v4.0.

Related Concept Videos
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more...
 01:24
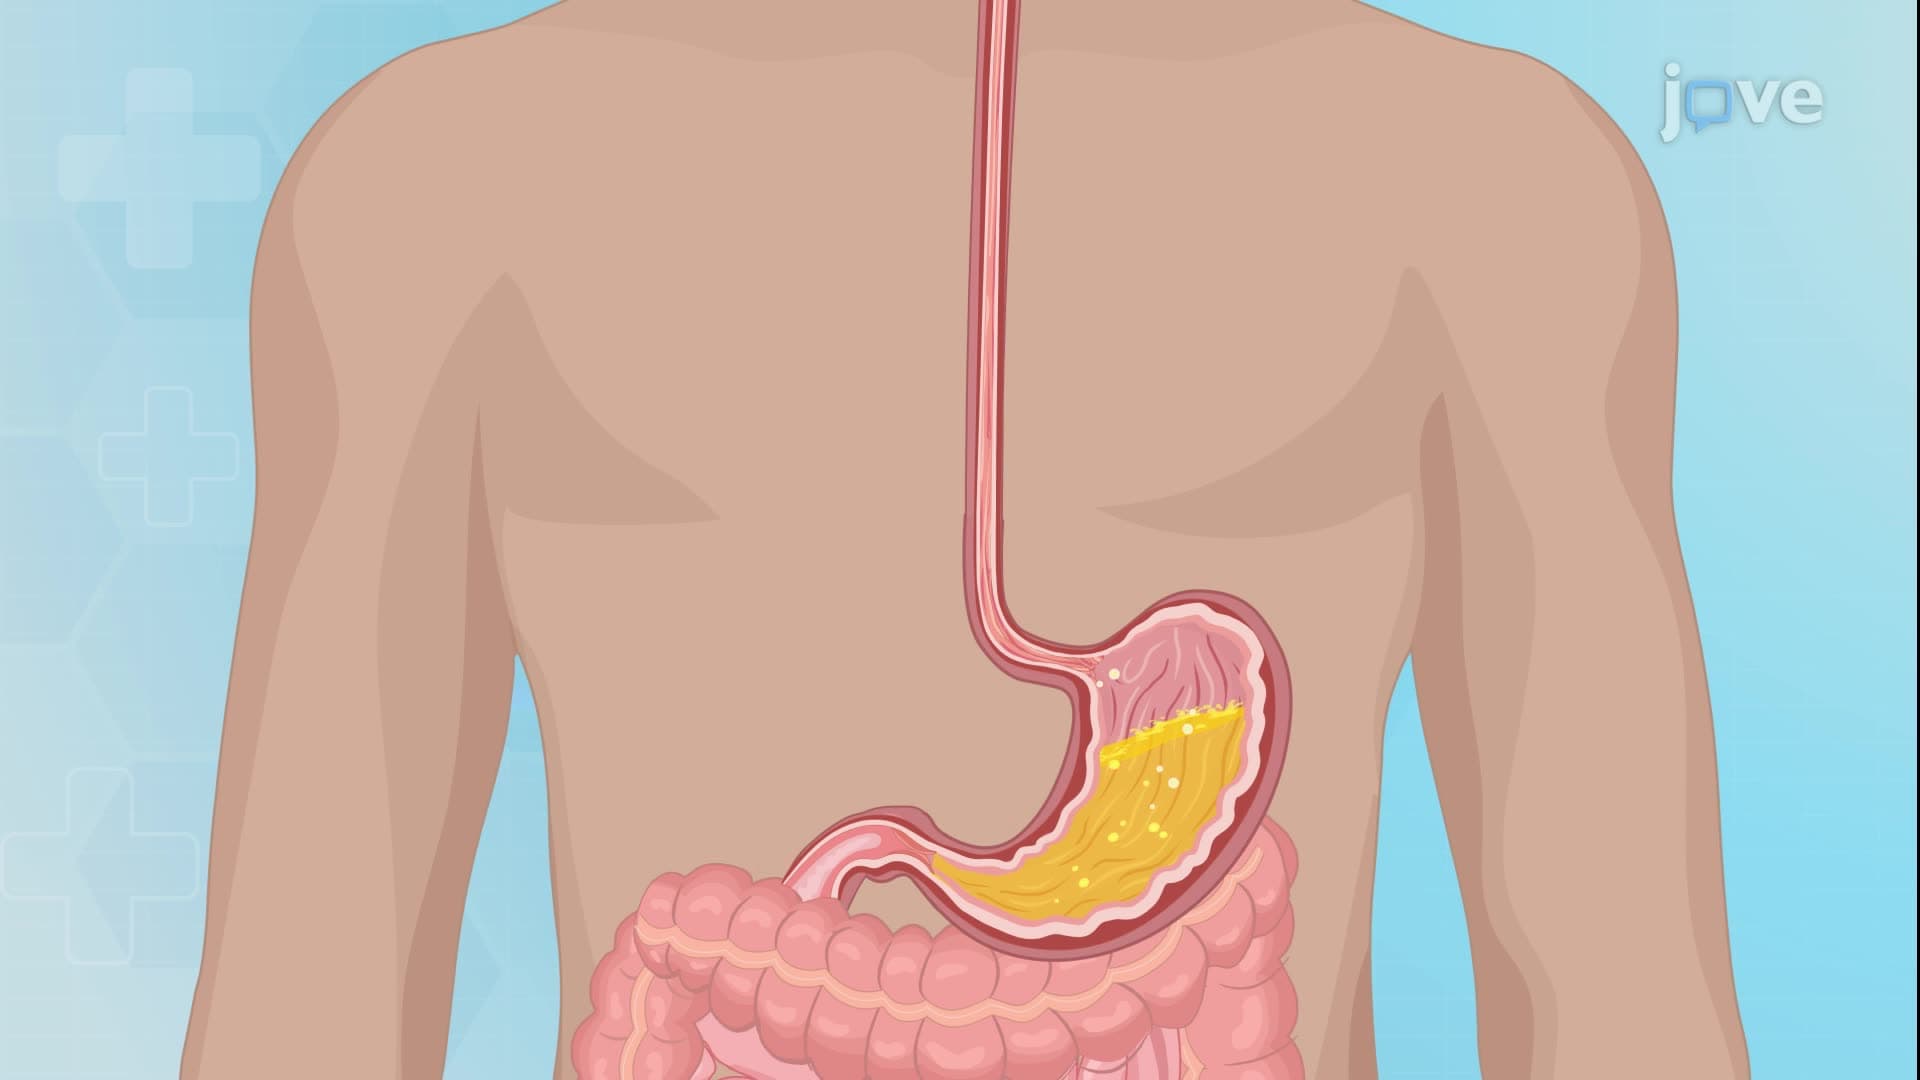
Upper GI Series: Barium Swallow
Purpose and Procedure
Patients undergoing this procedure ingest a liquid containing barium sulfate with a chalky...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:23
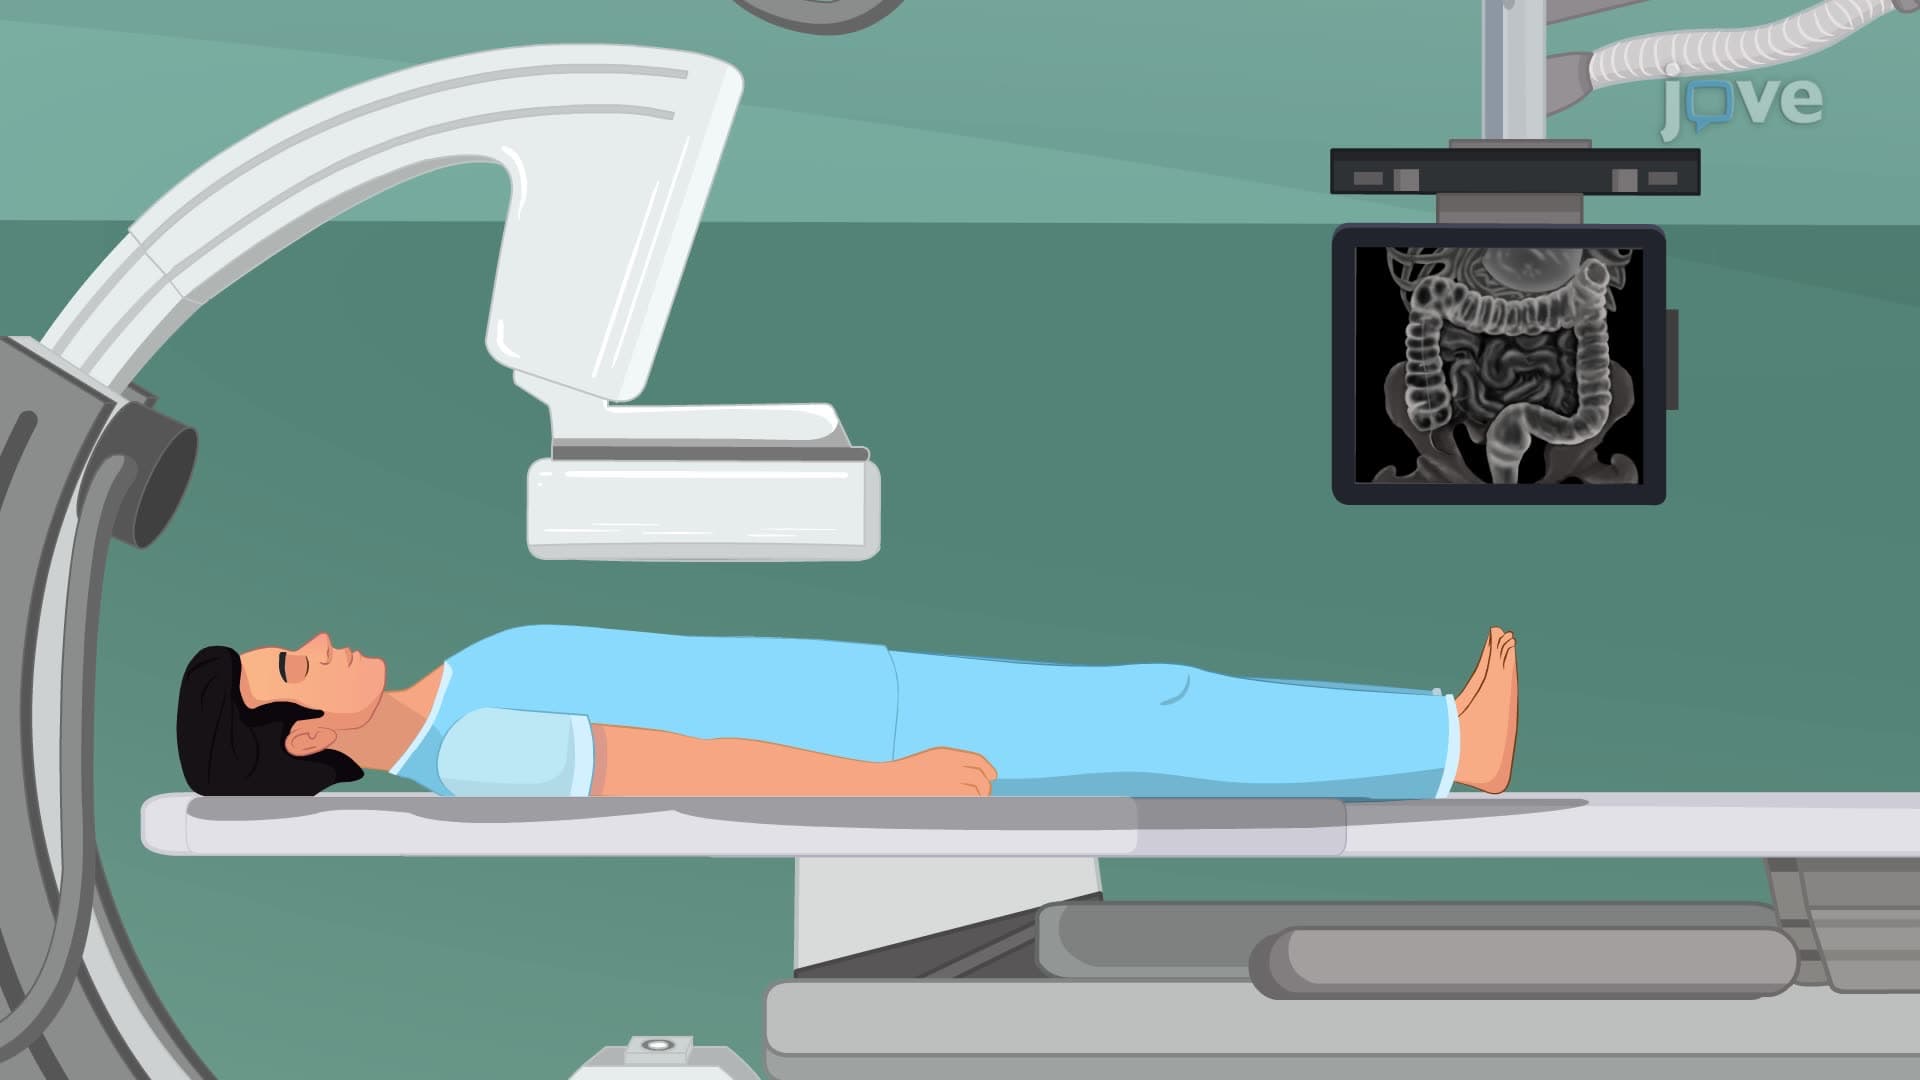
Lower GI Series: Barium Enema
Procedure Details
The examination begins by inserting a lubricated rectal tube into the patient's rectum to administer a radiopaque barium solution. The barium flow is carefully...