Related Experiment Video
Updated: Oct 2, 2025
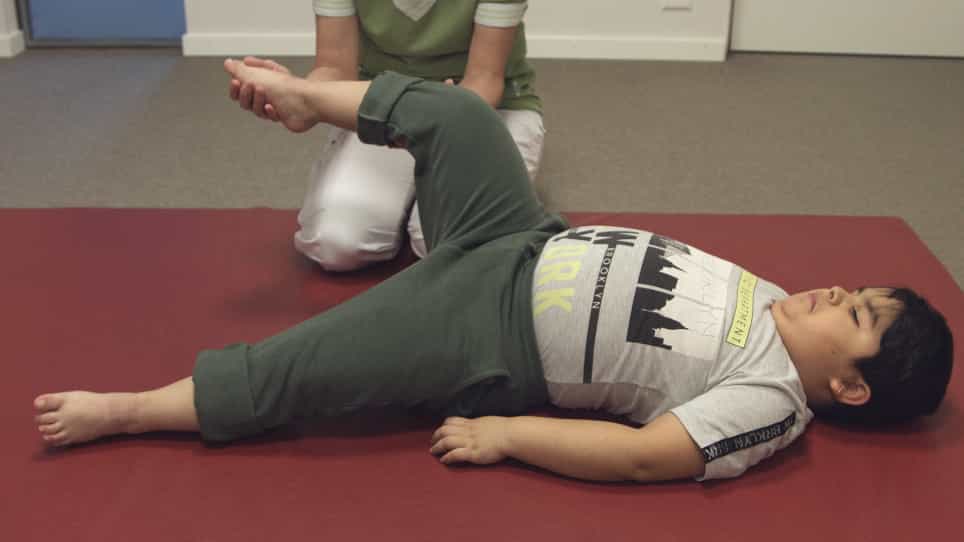

Measurements of Motor Function and Other Clinical Outcome Parameters in Ambulant Children with Duchenne Muscular Dystrophy
Published on: January 12, 2019
Healthcare resource utilization, total costs, and comorbidities among patients with myotonic dystrophy using U.S.
Sarah J Howe1, David Lapidus2, Michael Hull3
1Marigold Foundation, 7515 Flint Road SE, Calgary, AB, T2H 1G3, Canada. sarah.howe@marigoldfoundation.org.

Background:
Myotonic dystrophy (DM) is a rare, inherited disorder with multi-systemic effects that impact the skeletal muscles, eyes, heart, skin and gastrointestinal, endocrine, respiratory, and central nervous systems. DM is divided into two subtypes: DM1 can present from early childhood through adulthood and also has a congenital form (cDM) while DM2 typically manifests during mid-adulthood. Both forms are progressive with no approved treatments, and unmet need for disease-modifying therapies remains high. This study interrogated health insurance claims data to explore the clinical experience, healthcare resource utilization (HCRU), and all-cause costs for DM.
Results:
A total of 8541 patients with DM and 242 patients with cDM and their matched controls were selected from a database of over 200 million claimants. HCRU and all-cause costs, including pharmacy, outpatient, and inpatient services, were analyzed across four years in 12-month follow-up periods. Mean all-cause costs per DM patient were high in each of the four periods (range $14,640-$16,704) and showed a steady increase from 13 to 23 months on, while the control group mean costs declined from $9671 in the first 12 months after the index event, to approach the US population average ($5193) over time. For cDM, the highest mean costs were in the first 12-months ($66,496 vs. $2818 for controls), and remained high (above $17,944) across all subsequent periods, while control mean costs approached $0. For DM and cDM, HCRU was higher compared to controls across all study periods and all-cause healthcare costs were mostly driven by inpatient and outpatient encounters. Analysis of all diagnosis codes over the study period (comorbidities) demonstrated an elevated comorbidity profile consistent with the clinical profile of DM.
Conclusions:
This study is among the first to utilize claims data to increase understanding of the clinical experience and health economic outcomes associated with DM. The markedly elevated HCRU patterns and comorbidity profile presented here add to the broad body of scientific and clinical knowledge on DM. These insights can inform clinical care and support the development of disease modifying and/or symptom-targeting therapies that address the multi-systemic, progressive nature of DM.
Related Concept Videos
 01:28
Disorders of the Skeletal Muscle
Musculoskeletal disorders
Musculoskeletal disorders involve injuries and conditions affecting the skeletal muscles and associated connective tissues. These disorders can arise from acute biomechanical stresses or chronic overuse and can occur across different age groups. Common injuries include sprains, fractures, and muscular strains, often resulting from...
 01:29
Issues And Trends In Healthcare Delivery System
Cost Containment
Payment for healthcare services has historically promoted adoption of costly and often unnecessary or inefficient...
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:20
Myasthenia Gravis: Overview and Treatment
These antibodies interfere with the function of the nicotinic receptors in three ways: by binding to the receptor and disrupting acetylcholine binding; by causing cross-linking of receptors which...
 01:15
Methods of Documentation VI: Case Management Model
For example, a patient with a chronic...
 01:30
Health Information Technology and Healthcare Information System
Health Information Technology, commonly called HIT, integrates advanced information systems and technology in healthcare settings. Its primary functions include: