Related Experiment Video
Updated: Oct 2, 2025


Skeletal Phenotype Analysis of a Conditional Stat3 Deletion Mouse Model
Published on: July 3, 2020
Does the Skeletal Phenotype of Osteogenesis Imperfecta Differ for Patients With Non-COL1A1/2 Mutations? A
Tewodros Zerfu1, Bicheng Yong2, Jennifer Harrington3
1CURE Ethiopia Children's Hospital, Addis Ababa.

Background:
Osteogenesis imperfecta (OI) is a heritable disease characterized by bone fragility and other extra skeletal manifestations. Most patients with OI have mutations in the COL1A1 or COL1A2 genes. However, a significant minority of patients with clinical OI have non-COL1A1/2 mutations, which have become easier to detect with the use of genetic panels. Traditional understanding of OI pathogenesis was expanded because of these new mutations, and their phenotypic-genotypic relationship is largely unknown. We hypothesized that patients with non-COL1A1/2 mutations have different skeletal clinical presentations from those with OI caused by COL1A1/2 mutations.
Methods:
Patients were categorized into 4 groups according to our modified functional classification, namely, quantitative COL1A1/2 haploinsufficiency (group 1), qualitative COL1A1/2 dominant negative mutations (group 2), mutations indirectly affecting type I collagen synthesis, processing and posttranslational modification (group 3) and mutations altering osteoblast differentiation and function (group 4). Both group 3 and 4 were classified as non-COL1A1/2 mutation group.
Results:
Of 113 OI patients included, 51 had COL1A1/2 quantitative haploinsufficiency mutations (group 1), 39 had COL1A1/2 qualitative dominant negative mutations (group 2), and 23 patients had OI caused by mutations in 1 of 9 other noncollagen genes (groups 3/4). Patients with non-COL1A1/2 mutations (groups 3 and 4) have severe skeletal presentations. Specifically, OI patients with non-COL1A1/2 mutations experienced more perinatal fractures, vertebral compression fractures and had more long bone deformities. Although the occurrence of scoliosis was similar, the cobb angle was larger in the non-COL1A1/2 mutation group. Radial head dislocations, ossification of interosseous membrane, extraskeletal ossification, cervical kyphosis, and champagne glass deformity of the pelvis were more frequent in this group.
Conclusions:
The clinical phenotype of OI in patients with non-COL1A1/2 is severe and has unique features. This information is useful for clinical diagnosis and prognosis.
Level Of Evidence:
Level III.
More Related Videos
 09:20
Laser Capture Microdissection of Mouse Embryonic Cartilage and Bone for Gene Expression Analysis
Published on: December 18, 2019
 14:55
Analysis of Minerals Produced by hFOB 1.19 and Saos-2 Cells Using Transmission Electron Microscopy with Energy Dispersive X-ray Microanalysis
Published on: June 24, 2018
Related Concept Videos
 01:33
Pleiotropy
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:49
Multiple Allele Traits
 01:20
Introduction to the Skeletal System
Components of the Skeletal System
Bone, or osseous tissue, is a hard connective tissue that forms an internal support structure for the human body. Bones shield vulnerable organs and soft tissue from external forces. For example, the vertebral bones protect and support the spinal cord.
Cartilage, a semi-rigid connective tissue found in regions such as...
 01:27
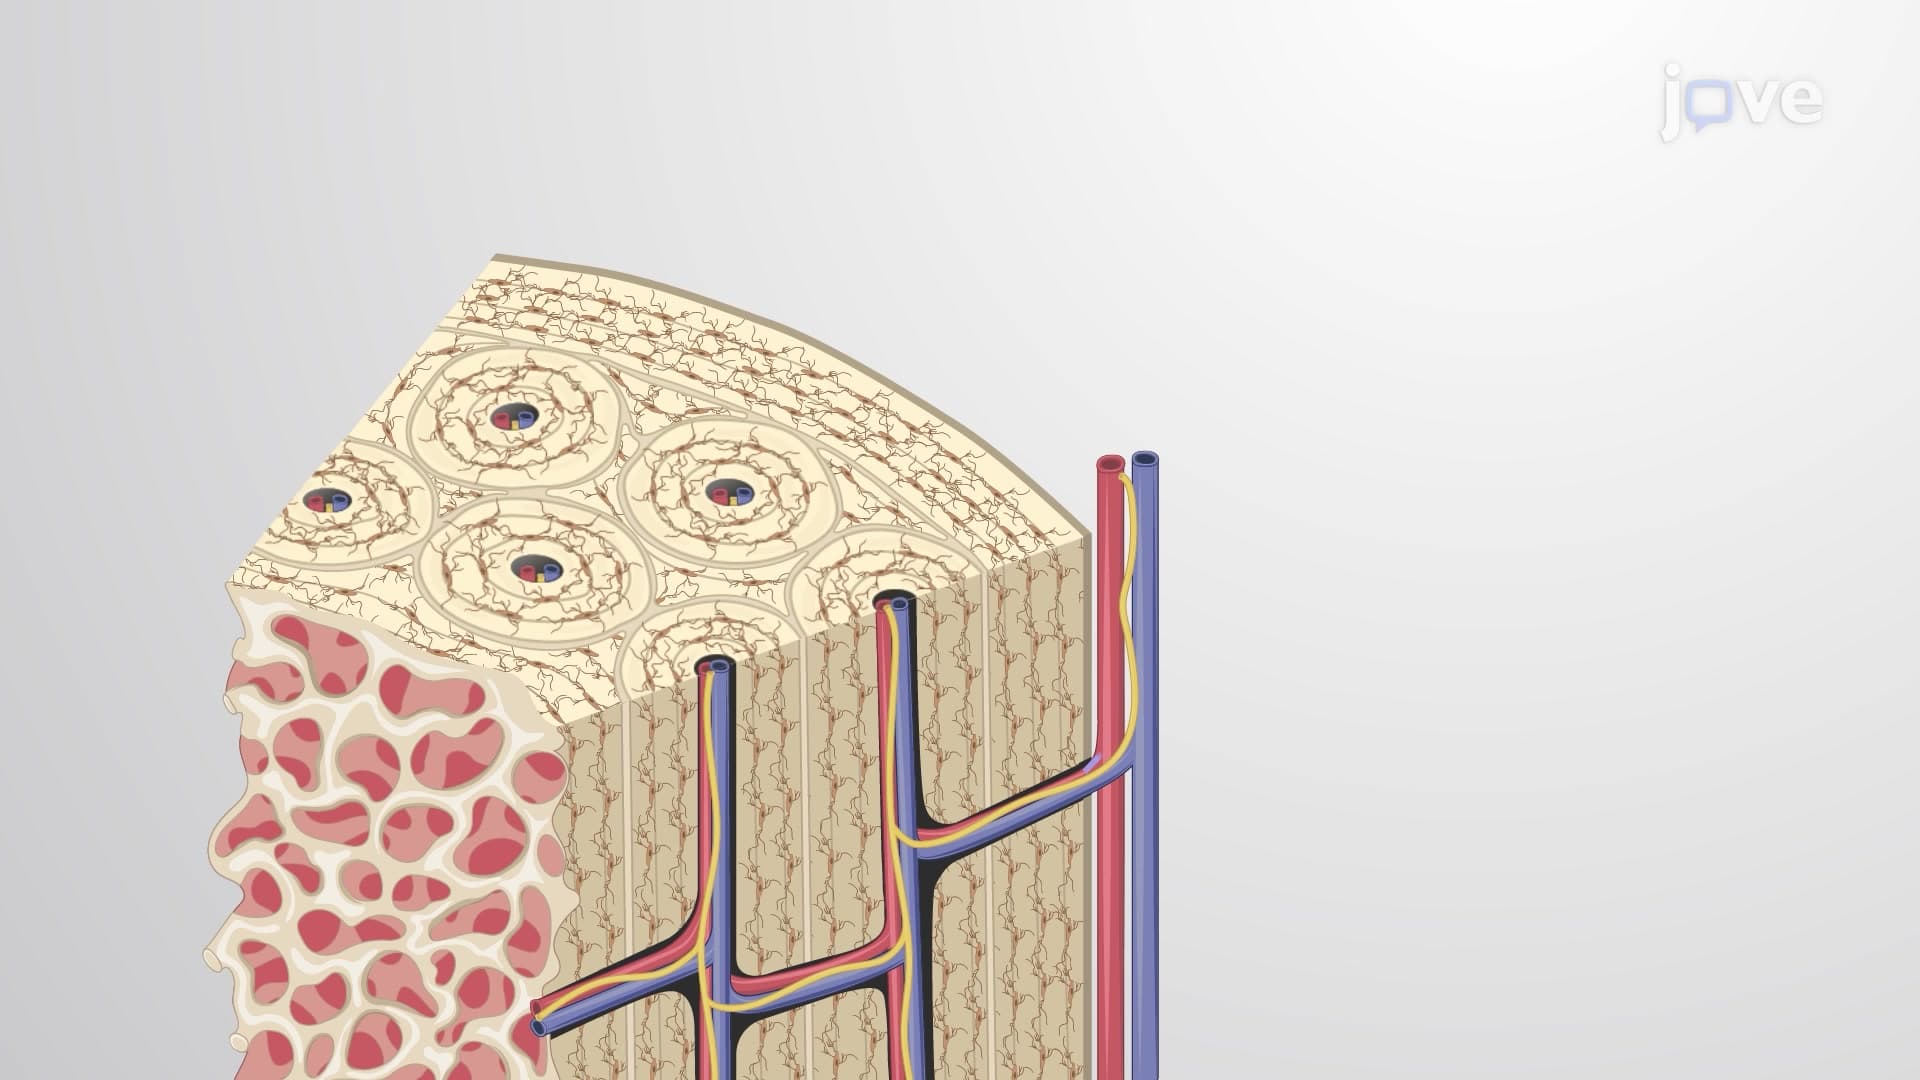
Compact Bone
Compact bone, also called cortical bone, is the denser, stronger of the two types of bone tissue. It is found under the periosteum and in the diaphyses of long bones, where it provides support and protection. The microscopic structural unit of compact bone is called an osteon, or haversian system. Each osteon is composed of concentric rings of calcified...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...