Related Experiment Video
Updated: Oct 2, 2025

Author Spotlight: Minimally Invasive Relief for Occipital Neuralgia at the Nuchal Line
Published on: September 13, 2024
Anatomy of the greater occipital nerve: implications in posterior fossa approaches
G Lainé1, V Jecko2, T Wavasseur2
1Department of Neurosurgery A, Hôpital Pellegrin, University Hospital of Bordeaux, Place Amélie Raba-Léon, 33000, Bordeaux, France. gaetan.laine@neurochirurgie.fr.

Purpose:
Because of its superficial location in the dorsal regions of the scalp, the greater occipital nerve (GON) can be injured during neurosurgical procedures, resulting in post-operative pain and postural disturbances. The aim of this work is to specify the course of the GON and how its injuries can be avoided while performing posterior fossa approaches.
Methods:
This study was carried out at the department of anatomy at Bordeaux University. 4 specimens were dissected to study the GON course. Posterior fossa approaches (midline suboccipital, paramedian suboccipital, retrosigmoid and petrosal) were performed on 4 other specimens to assess potential risks of GON injuries.
Results:
The GON runs around the obliquus capitis inferior (100%), crosses the semispinalis capitis (100%) and the trapezius (75%) or its aponeurosis (25%). Direct GON injuries can be seen in paramedian suboccipital approaches. Stretching of the GON can occur in midline suboccipital and paramedian suboccipital approaches. We found no evidence of direct or indirect GON injury in retrosigmoid or petrosal approaches.
Conclusion:
Our study provides interesting data regarding the risk GON injury in posterior fossa approaches. Direct GON injuries in paramedian suboccipital approaches can be avoided with careful dissection. Placing retractors in contact with the periosteum and performing a minimal retraction may help to avoid excessive GON stretching in midline suboccipital and paramedian suboccipital approaches. Furthermore, the incision for retrosigmoid approaches should be as lateral as possible and not too caudal. Finally, avoiding extreme patient positioning reduces the risk of GON stretching in all approaches.
Related Concept Videos
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:14
Cranial Nerves: Types Part I
Olfactory Nerve (Cranial Nerve I)
The olfactory nerve, or cranial nerve I, is unique as it is purely sensory and dedicated to the sense of smell. This nerve originates in the olfactory epithelium of the...
 01:19
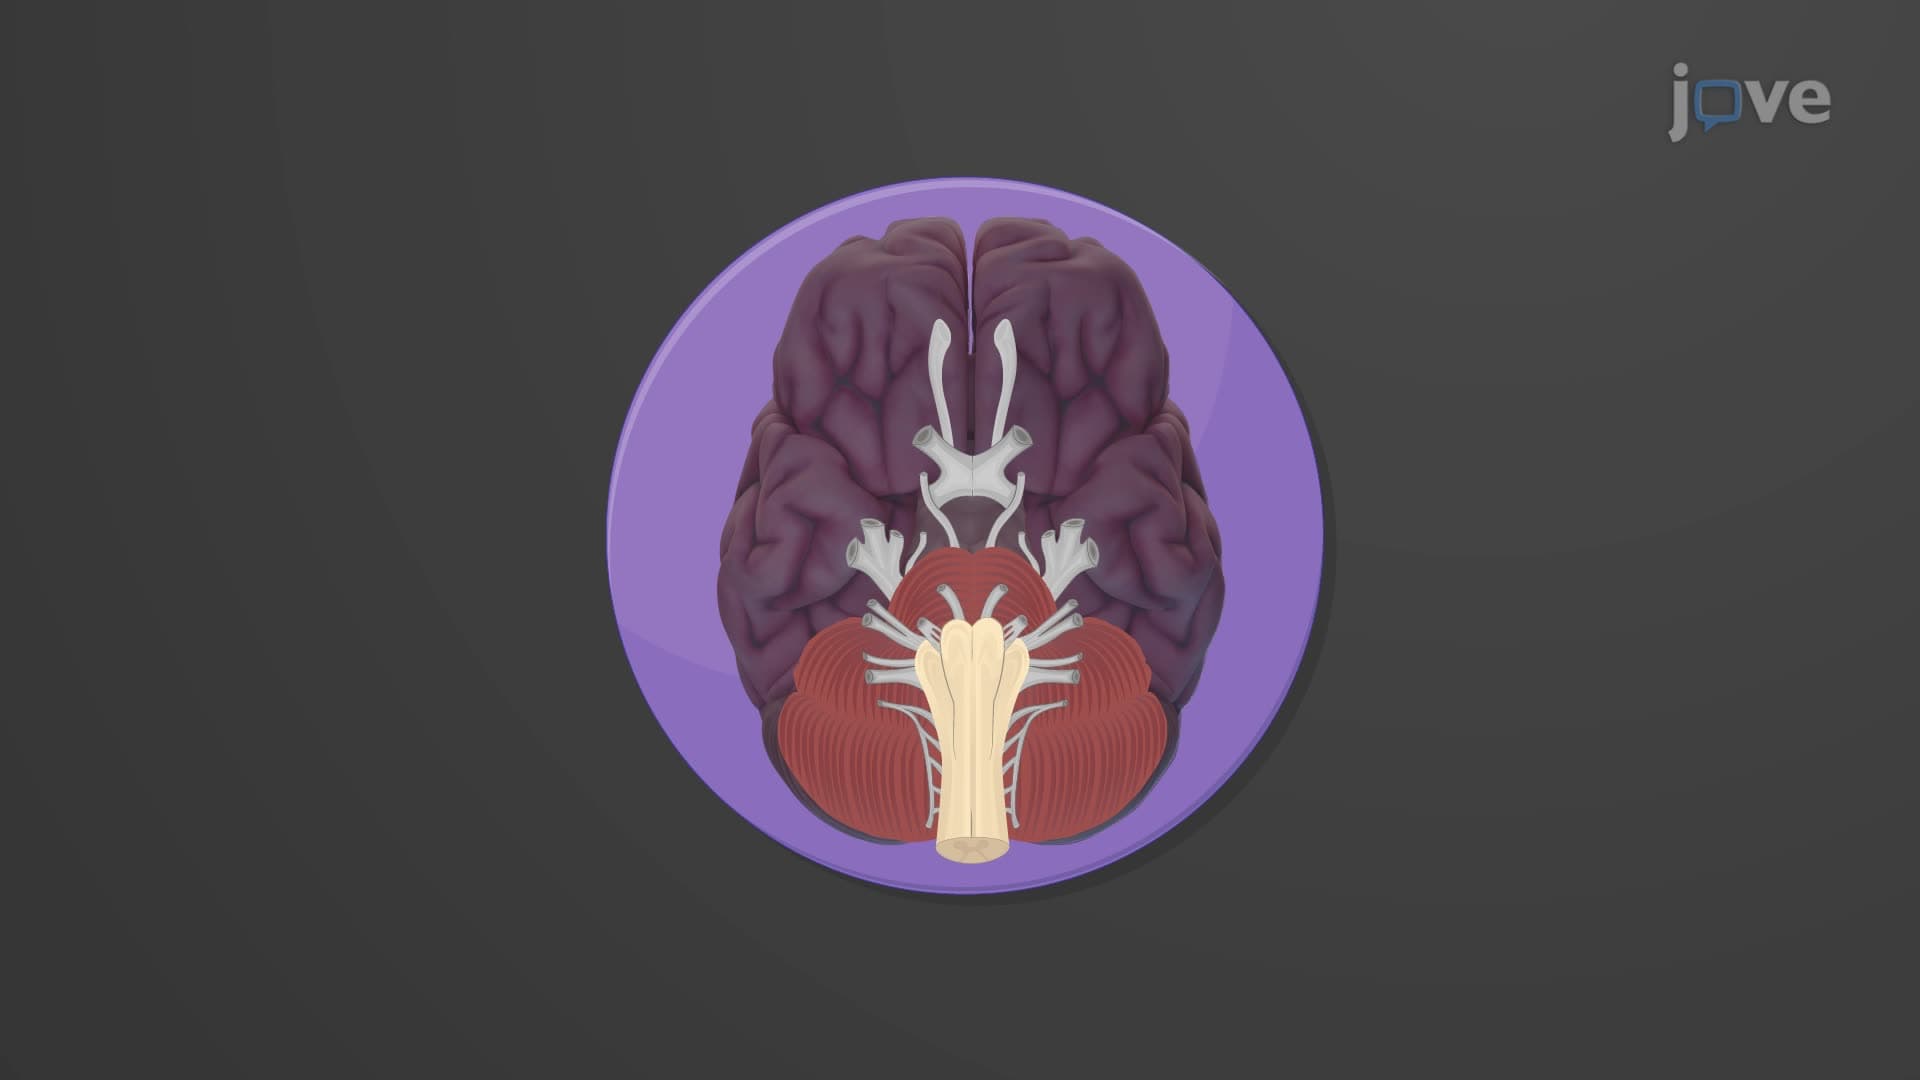
Cranial Nerves: Overview and Anatomy
 01:10
The Arch of Aorta
Encircling the heart, the coronary arteries form a ring-like structure before...
 01:22
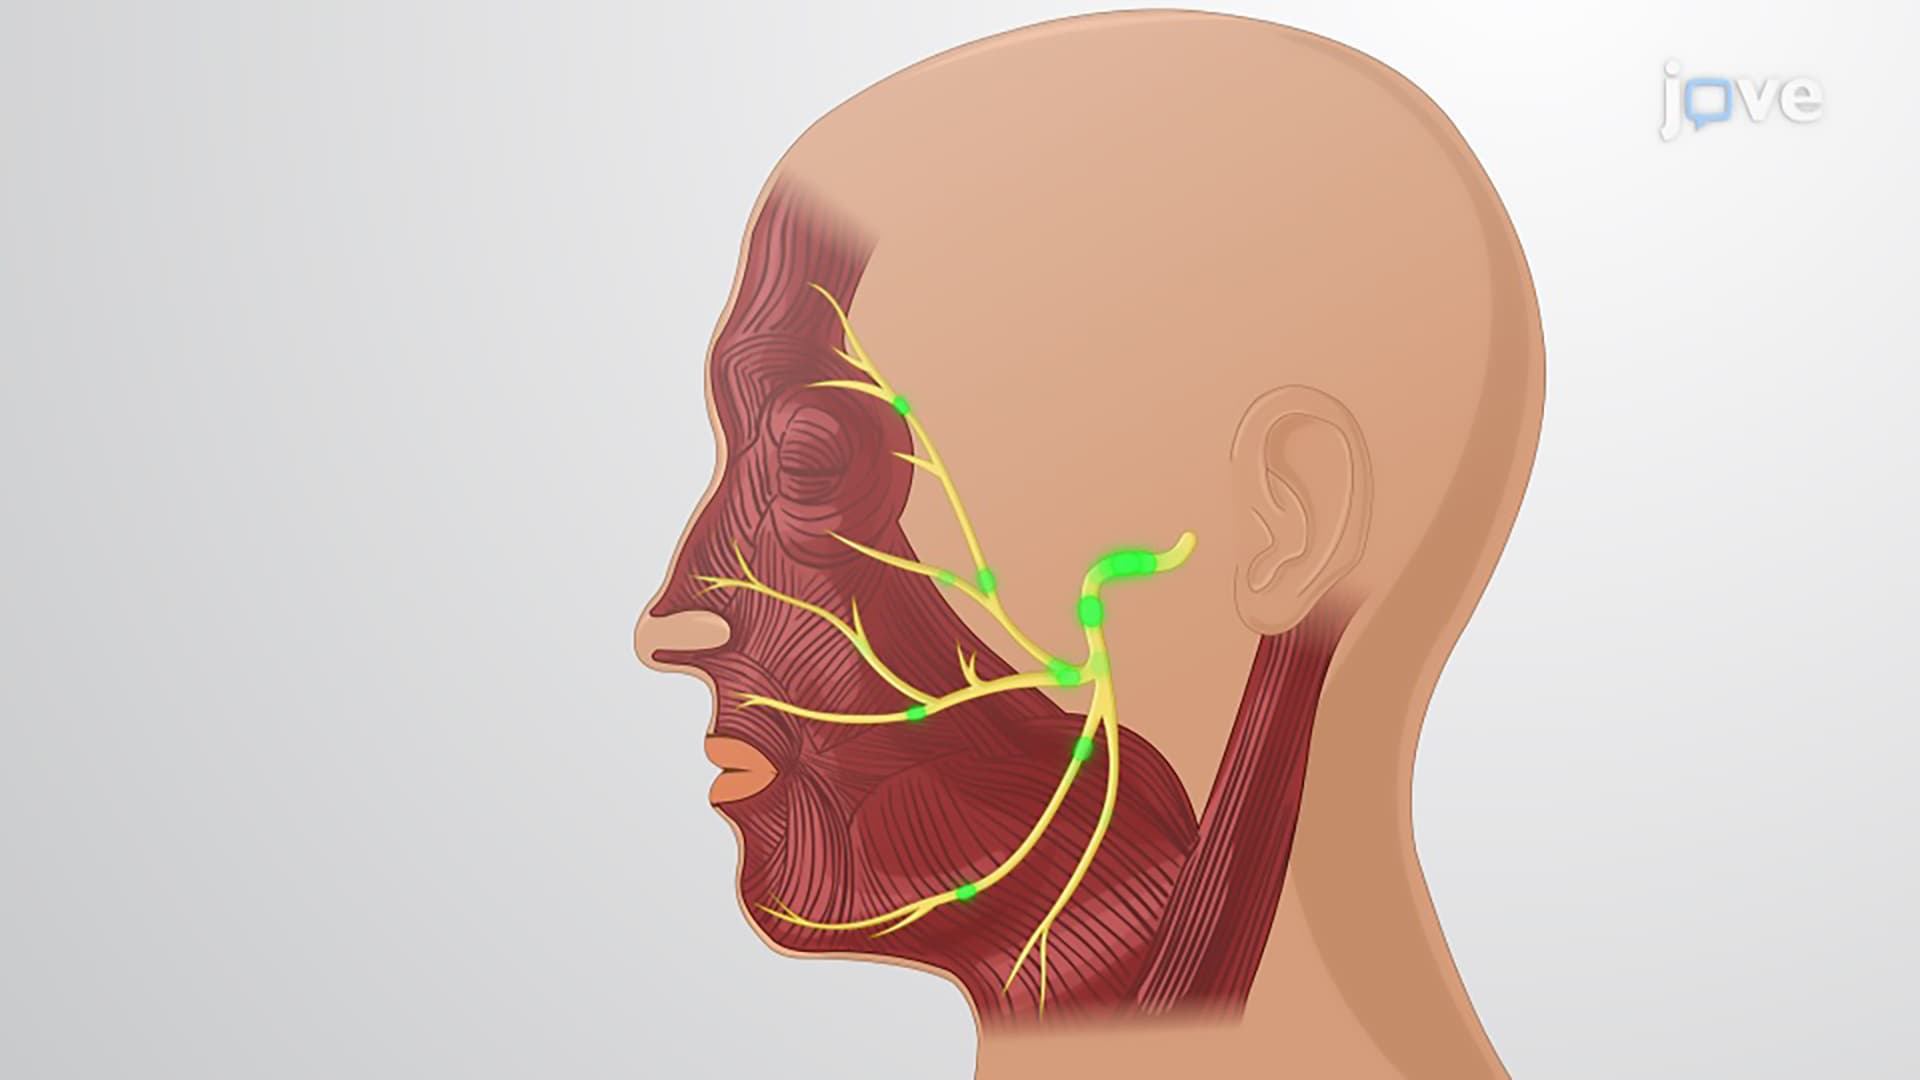
Cranial Nerves: Types Part II
Facial Nerve (Cranial Nerve VII)
Cranial nerve VII, or the facial nerve,...
 01:27
Cranial Bones: Lateral View
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...