Related Experiment Video
Updated: Oct 2, 2025
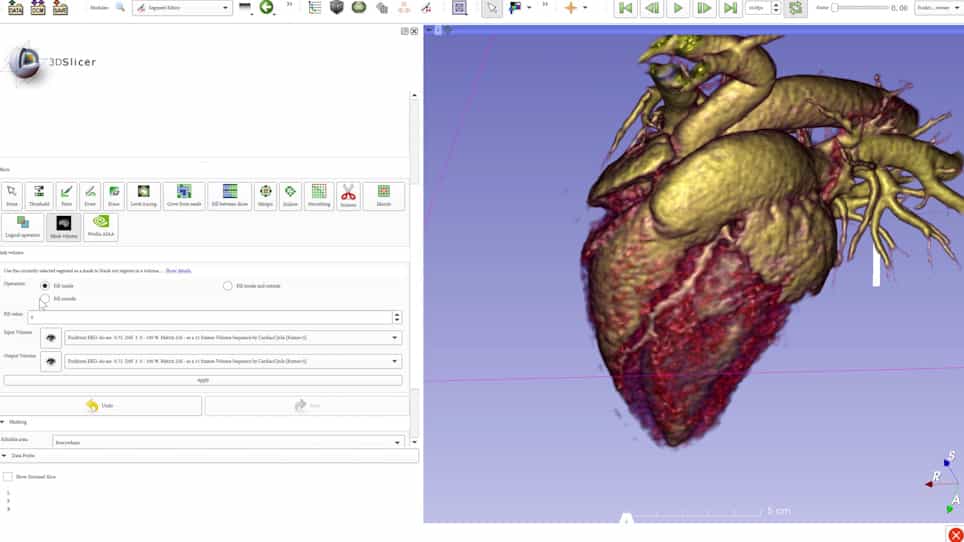
Four-Dimensional Computed Tomography-Guided Valve Sizing for Transcatheter Pulmonary Valve Replacement
Published on: January 20, 2022
Solving the Pulmonary Hypertension Paradox in Patients With Severe Tricuspid Regurgitation by Employing Artificial
Vera Fortmeier1, Mark Lachmann2, Maria I Körber3
1Department of General and Interventional Cardiology, Heart and Diabetes Center North Rhine-Westphalia, Ruhr University Bochum, Bad Oeynhausen, Germany.

Objectives:
This study aimed to improve echocardiographic assessment of pulmonary hypertension (PH) in patients presenting with severe tricuspid regurgitation (TR).
Background:
Echocardiographic assessment of PH in patients with severe TR carries several pitfalls for underestimation, hence concealing the true severity of PH in very sick patients in particular, and ultimately obscuring the impact of PH on survival after transcatheter tricuspid valve intervention (TTVI).
Methods:
All patients in this study underwent TTVI for severe TR between 2016 and 2020. To predict the mean pulmonary artery pressure (mPAP) solely based on echocardiographic parameters, we trained an extreme gradient boosting (XGB) algorithm. The derivation cohort was constituted by 116 out of 162 patients with both echocardiography and right heart catheterization data, preprocedurally obtained, from a bicentric registry. Moreover, 142 patients from an independent institution served for external validation.
Results:
Systolic pulmonary artery pressure was consistently underestimated by echocardiography in comparison to right heart catheterization (40.3 ± 15.9 mm Hg vs 44.1 ± 12.9 mm Hg; P = 0.0066), and the assessment was most discrepant among patients with severe defects of the tricuspid valve and impaired right ventricular systolic function. Using 9 echocardiographic parameters as input variables, an XGB algorithm could reliably predict mPAP levels (R = 0.96, P < 2.2 × 10⁻¹⁶). Moreover, patients with elevations in predicted mPAP levels ≥29.9 mm Hg showed significantly reduced 2-year survival after TTVI (58.3% [95% CI: 41.7%-81.6%] vs 78.8% [95% CI: 68.7%-90.5%]; P = 0.026). Importantly, the poor prognosis associated with elevation in predicted mPAP levels was externally confirmed (HR for 2-year mortality: 2.9 [95% CI: 1.5-5.7]; P = 0.002).
Conclusions:
PH in patients with severe TR can be reliably assessed based on echocardiographic parameters in conjunction with an XGB algorithm, and elevations in predicted mPAP levels translate into increased mortality after TTVI.

Related Concept Videos
 01:25
Aortic Regurgitation III: Medical Management
 01:30
Pulmonary Hypertension: Classification and Pathogenesis
There are various classifications for PH, each relating to different underlying causes and also...
 01:25
Mitral Regurgitation III: Medical Management
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests