Related Experiment Video
Updated: Oct 2, 2025


ADSC-sheet Transplantation to Prevent Stricture after Extended Esophageal Endoscopic Submucosal Dissection
Published on: February 10, 2017
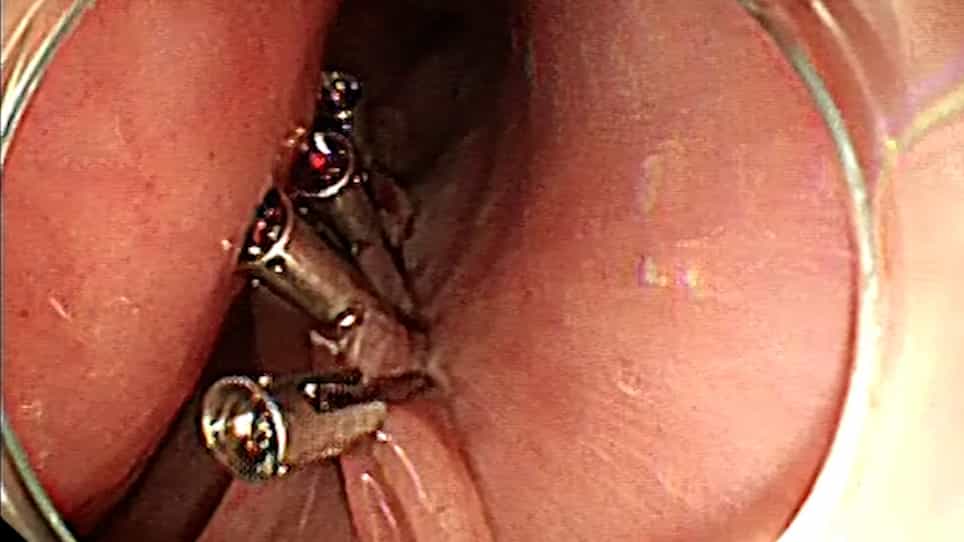
Efficacy of endoscopic clip closure for nonperforated muscle layer exposure during esophageal endoscopic submucosal
Hayato Yamaguchi1, Masakatsu Fukuzawa1, Takashi Kawai2
1Department of Gastroenterology and Hepatology, Tokyo Medical University, Tokyo, Japan.

Abstract:
Exposure of the muscle layer during endoscopic submucosal dissection (ESD) in the esophagus can lead to complications such as fever and pain. Although closure with endoscopic clips is widely used when perforation is a major complication, its value when the exposed muscle layer is not perforated is unclear. Data for 104 lesions in 104 patients who underwent esophageal ESD between 2008 and 2020 were retrospectively analyzed. Patients with multiple tumors, those who experienced procedure-related adverse events such as aspiration pneumonitis, perforation during ESD, or delayed bleeding, and those in whom the muscle layer was not exposed were excluded. The clinical course of inflammation after ESD in patients in whom the muscle layer was exposed was examined according to whether endoscopic clips were used for closure. A significantly greater number of patients had a temperature ≤ 37.5°C in the clip closure group than in the nonclip closure group (≤37.5°C/≥37.6°C, 47/14 vs. 25/18, respectively, P = 0.040). Furthermore, significantly more patients in the clip closure group had a white blood cell count ≤10,000/μL (≤10,000/μL/>10,000/μL, 51/10 vs. 21/22, P < 0.001) and a C-reactive protein level < 1.0 mg/dL (<1.0 mg/dL/≥1.0 mg/dL, 40/21 vs. 36/7, P = 0.040) in the 24 hour post-ESD. The results were not changed after propensity score matching. Closure with endoscopic clips reduces inflammation after esophageal ESD with nonperforated muscle layer exposure. Even if there is no obvious perforation during ESD, closure of the exposed muscle layer with endoscopic clips may contribute to the clinical course post-ESD.
Insights
Closing exposed muscle layers after esophageal endoscopic submucosal dissection (ESD) with endoscopic clips can reduce post-procedure inflammation. This technique may improve patient outcomes even without visible perforation during ESD.
Area of Science:
- Gastroenterology
- Endoscopy
- Surgical Complications
Background:
- Esophageal endoscopic submucosal dissection (ESD) can expose the muscle layer, potentially leading to post-procedural fever and pain.
- Endoscopic clips are standard for managing perforations, but their utility for non-perforated muscle layer exposure is not well-established.
Purpose of the Study:
- To evaluate the impact of endoscopic clip closure on post-ESD inflammation in cases with exposed muscle layer but no perforation.
- To determine if clip closure influences key inflammatory markers and patient temperature post-procedure.
Main Methods:
- Retrospective analysis of 104 patients undergoing esophageal ESD between 2008 and 2020.
- Exclusion of patients with multiple tumors, procedure-related adverse events, or no muscle layer exposure.
- Comparison of inflammatory markers (temperature, WBC, CRP) between patients with and without clip closure for exposed muscle layers.
Main Results:
- Patients with clip closure showed significantly lower post-ESD temperatures (≤37.5°C) compared to the non-clip group (P=0.040).
- Clip closure was associated with significantly lower white blood cell counts (≤10,000/μL) (P<0.001) and C-reactive protein levels (<1.0 mg/dL) (P=0.040) within 24 hours post-ESD.
- These findings remained significant after propensity score matching.
Conclusions:
- Endoscopic clip closure of non-perforated exposed muscle layers after esophageal ESD effectively reduces post-procedural inflammation.
- This prophylactic closure strategy may improve the clinical course and patient recovery following esophageal ESD.

Related Concept Videos
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...