Multilobulated Sinus of Valsalva Aneurysm Dissecting into the Interventricular Septum (DAIS) and Rupturing into Left Ventricle: A Case Report
Related Experiment Video
Updated: Oct 12, 2026

Microsurgical Clip Obliteration of Middle Cerebral Aneurysm Using Intraoperative Flow Assessment
Published on: September 25, 2009
Soumitra Ghosh1, Dinakar Bootla1, Parag Barward1
1Department of Cardiology, Advanced Cardiac Centre, Post Graduate Institute of Medical Education & Research, Sector 12, Chandigarh 160012, India.

Background:
Dissecting aneurysm of sinus of Valsalva (SOV) into the interventricular septum is a rare entity. Multilobulated form of dissection rupturing into the left ventricle (LV) has never been reported in the literature.
Case Summary:
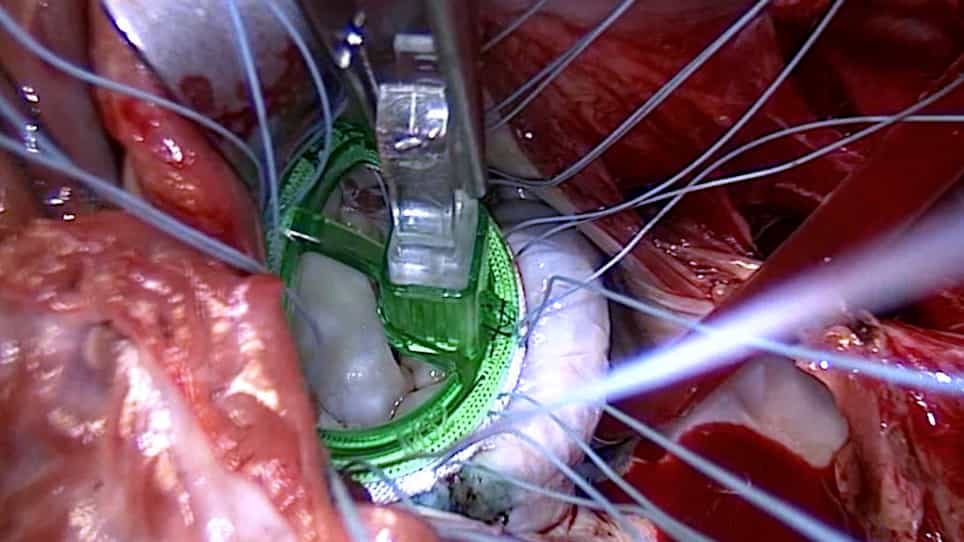
A 52-year-old male presented with dyspnoea and palpitation with wide pulse pressure and peripheral signs of distal run-off and a continuous murmur along the left parasternal area. Echocardiography revealed dilated right coronary cusp (RCC), which burrowed into the interventricular septum (IVS), forming multi-loculated cystic lesion which ruptured into LV with associated restrictive ventricular septal defect (VSD) and severe aortic regurgitation. Computed tomography (CT) angiography confirmed a 4.8 cm × 5.3 cm × 5.4 cm multiseptated aneurysm. The surgery involved excision of the aortic valve (AV) with the sinus, ligation of its penetrating portion at the crest of IVS, closure of VSD, and AV replacement. Postoperative echocardiography showed the complete collapse of the IVS component of the SOV aneurysm and the normally functioning mechanical AV.
Discussion:
Dissecting aneurysm into the IVS is a rare variant of SOV aneurysm, usually arising from RCC. It is mostly congenital in origin and has wide variety of presentations like congestive heart failure, palpitations, recurrent syncope, chest pain, sudden cardiac arrest, infective endocarditis, cerebral infarction, or asymptomatic. Aortic regurgitation is present in 30-50% of cases. Conduction disturbances from first-degree block to complete heart block are common. Echocardiogram, CT angio, and magnetic resonance imaging are useful for diagnosis. Surgical repair is the only option for treatment.
More Related Videos

Related Concept Videos
 01:27
Mitral Valve Prolapse I: Introduction
 01:22
Mitral Stenosis I: Introduction
 01:15
Aortic Regurgitation I: Introduction
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:30
Aneurysm I: Introduction
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies