

IgA Vasculitis Without Typical Skin Rash Concomitated With c-ANCA Positivity
Mohamed W Abukhatwah1, Naglaa M Kamal2, Muteb K Altowairqi1
1Pediatrics, Alhada Armed Forces Hospital, Taif, Kingdom of Saudi Arabia.

Abstract:
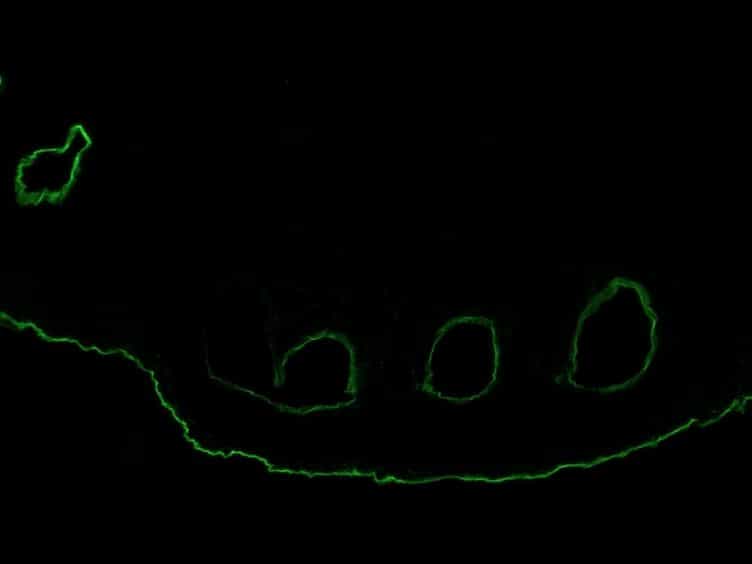
We describe a case of IgA vasculitis without typical skin rash concomitated with c-ANCA positivity in a 6-year-old boy who presented with persistent severe generalized colicky abdominal pain, recurrent episodes of vomiting, non-pitting edema of both hands and feet, both knees and ankles arthritis with no associated skin rash following a history of an upper respiratory tract infection 2 weeks before presentation. Initially, he had normal laboratory findings apart from sub-nephrotic range proteinuria and microscopic hematuria in his urine analysis. Two weeks later, he started to have hypertension, gross hematuria, nephrotic range proteinuria, marked elevation of serum urea and creatinine associated with positive serum C-ANCA. Renal biopsy revealed heavy IgA mesangial deposition with marked crescent formation involving more than 89% of the glomeruli (grade V). Aggressive therapeutic measures were initiated including IV pulsed steroid therapy and IV pulsed cyclophosphamide for 5 cycles followed by oral steroid and mycophenolate with close monitoring of the patient who showed marked improvement. Up to our knowledge, this is the first reported case of IgA-vasculitis-associated nephritis with bowel angina symptoms, arthritis, and edema but without typical skin rashes.

Related Concept Videos
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis
 01:19
Pericarditis II: Clinical Features and Diagnostic Tests
 01:27
Myocarditis II: Clinical Features and Diagnostic Tests
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:22
Pericarditis I: Introduction
 01:29
Autoimmune Disorders
Concept and Mechanism of Autoimmune Diseases
The immune...