Related Experiment Video
Updated: Oct 1, 2025


Assessment of Vascular Function in Patients With Chronic Kidney Disease
Published on: June 16, 2014
The relationship of endothelial function and arterial stiffness with subclinical target organ damage in essential
Yancui Sun1, Fei Liu1, Ying Zhang1
1Department of Cardiology, First Affiliated Hospital of Dalian Medical University, Dalian, Liaoning Province, China.

Insights
Essential hypertension patients with high brachial-ankle pulse wave velocity (baPWV) and low brachial artery flow-mediated dilation (FMD) face increased subclinical target organ damage (STOD) risk, particularly those under 65.
Area of Science:
- Cardiovascular Medicine
- Hypertension Research
- Vascular Biology
Background:
- Essential hypertension is a major risk factor for cardiovascular disease.
- Subclinical target organ damage (STOD) precedes overt cardiovascular events.
- Arterial stiffness (baPWV) and endothelial dysfunction (FMD) are key vascular parameters.
Purpose of the Study:
- To investigate the association of brachial-ankle pulse wave velocity (baPWV) and brachial artery flow-mediated dilation (FMD) with STOD in hypertensive patients.
- To examine the combined effect and interaction of baPWV and FMD on STOD risk.
Main Methods:
- Cross-sectional study of 4618 essential hypertension patients.
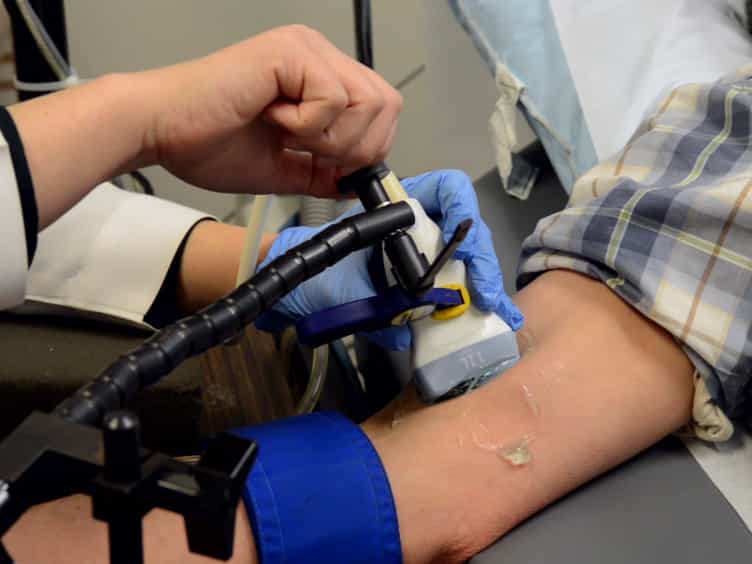
- Measurements included baPWV (arterial stiffness) and FMD (endothelial function).
- STOD indicators: left ventricular hypertrophy (LVH), urine albumin-creatinine ratio (UACR), carotid intima-media thickness (CIMT).
Main Results:
- Higher baPWV and lower FMD were independently associated with increased STOD risk.
- Significant associations were more pronounced in patients younger than 65.
- Interaction analysis revealed a progressively higher STOD risk with increasing baPWV across FMD quartiles.
Conclusions:
- BaPWV and FMD are significant independent predictors of STOD in essential hypertension.
- The combination of elevated baPWV and reduced FMD identifies high-risk patients.
- Risk stratification for STOD can be improved by considering both baPWV and FMD, especially in younger hypertensive individuals.
Abstract:
This study aimed to explore whether brachial-ankle pulse wave velocity (baPWV) and brachial artery flow-mediated dilation (FMD) or the interaction of both parameters are associated with subclinical target organ damage (STOD) indices in patients with essential hypertension. A total of 4618 patients registered from January 2015 to October 2020 were included. baPWV and FMD were measured to evaluate arterial stiffness and endothelial dysfunction. Whereas left ventricular hypertrophy (LVH), urine albumin-creatinine ratio (UACR), and carotid intima-media thickness (CIMT) were obtained as STOD indicators. On multivariable logistic regression analysis with potential confounders, higher quartiles of baPWV and FMD were significantly associated with an increased risk of STOD. In patients <65 years of age, the odds ratio (OR) of LVH, UACR, and CIMT ≥.9 mm for the fourth versus the first quartile of baPWV were 1.765 (1.390-2.240), 2.832 (2.014-3.813), and 3.075 (2.315-4.084), respectively. In interaction analysis, an increase in baPWV shows a progressively higher risk of STOD across the quartiles of FMD. Also, the estimated absolute risks of LVH, UACR, and CIMT ≥.9 mm for the first to fourth quartile of baPWV increased from 1.88 to 2.75, 2.35 to 4.44, and 3.10 to 6.10, respectively, in patients grouped by FMD quartiles. The addition of baPWV to FMD slightly improved risk prediction for STOD. BaPWV and FMD were independently associated with an increased risk of STOD in patients with essential hypertension especially among patients <65 years of age. Patients with elevated baPWV and decreased FMD parameters are at increased risk of STOD.
Related Concept Videos
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:29
Hypertension II: Pathophysiology
 01:18
Hypertension and Regulation of Blood Pressure
 01:28
Hypertension I: Introduction
 01:30
Coronary Artery Disease I: Introduction
 01:26
Coronary Artery Disease II: Pathophysiology