Related Experiment Video
Updated: Oct 1, 2025

Author Spotlight: Simulating Pediatric Cardiac Surgery Using a Neonatal Piglet Model
Published on: May 26, 2023
Impact of Continuous Renal Replacement Therapy on Bivalirudin Dosing in Pediatric Extracorporeal Membrane Oxygenation
Michael A Lahart1,2, Emily L Burns2,3, Madison M Streb4
1From the Department of Pharmacy, St. Louis Children's Hospital, St. Louis, MO.

Insights
Continuous renal replacement therapy (CRRT) does not affect bivalirudin dosing in pediatric extracorporeal membrane oxygenation (ECMO) patients. Younger age and lower weight were associated with higher bivalirudin doses.
Area of Science:
- Pediatric critical care medicine
- Pharmacology and therapeutics
- Nephrology
Background:
- Bivalirudin is increasingly used for anticoagulation in pediatric extracorporeal membrane oxygenation (ECMO).
- Optimal bivalirudin dosing in pediatric ECMO patients also requiring continuous renal replacement therapy (CRRT) is not well-established.
- Understanding factors influencing bivalirudin dosing is crucial for patient safety and treatment efficacy.
Purpose of the Study:
- To investigate the impact of CRRT on bivalirudin dosing requirements in pediatric ECMO patients.
- To identify potential correlations between CRRT, patient age, weight, and bivalirudin dosage.
- To provide evidence-based guidance for bivalirudin anticoagulation in this complex patient population.
Main Methods:
- Retrospective analysis of pediatric patients (≤18 years) on ECMO and bivalirudin for ≥24 hours (January 2019 - May 2020).
- Bivalirudin doses were recorded for 144 hours from initiation of bivalirudin or CRRT.
- Statistical analysis to compare bivalirudin dosing between patients with and without CRRT, considering age and weight.
Main Results:
- Eleven out of thirty-one (35%) pediatric ECMO patients required concomitant CRRT.
- No significant difference in bivalirudin mean dosing was observed between patients with and without CRRT (0.13 mg/kg/hr vs. 0.15 mg/kg/hr, p=0.13).
- Younger age (p<0.001) and lower weight (p<0.001) were significantly associated with higher bivalirudin dosing requirements.
Conclusions:
- Concomitant CRRT does not appear to significantly alter bivalirudin dosing needs in pediatric ECMO patients.
- Bivalirudin dosage adjustments in pediatric ECMO should primarily consider patient age and weight.
- Further research may refine dosing strategies for bivalirudin in critically ill children undergoing ECMO and CRRT.
Abstract:
There is an increasing interest in the use of bivalirudin for pediatric extracorporeal membrane oxygenation (ECMO) anticoagulation. However, dosing is not well described in those requiring continuous renal replacement therapy (CRRT). We aimed to determine whether CRRT affects bivalirudin dosing in pediatric ECMO patients. Children ≤18 years of age placed on ECMO and anticoagulated with bivalirudin for ≥24 hours from January 2019 to May 2020 were included. Bivalirudin doses were collected for 144 hours from initiation of bivalirudin or CRRT. Analysis was performed to determine whether CRRT, age, or weight affected bivalirudin dosing. Thirty-one children were included, and 11 (35%) required concomitant CRRT. There was no difference in age (median 9.1 versus 3.2 months, p = 0.15) or days on ECMO (median 11 versus 9, p = 0.7) between those who did or did not receive CRRT. The mean bivalirudin dosing was similar in patients who did or did not require CRRT (median and IQR: 0.13 mg/kg/hour [0.08-0.26] versus 0.15 mg/kg/hour [0.11-0.22], respectively, p = 0.13). Younger age ( p < 0.001) and lower weight ( p < 0.001) were associated with higher bivalirudin dosing. In our study, bivalirudin dosing did not differ if the patient required CRRT while on ECMO.

Related Concept Videos
 01:30
Continuous Renal Replacement Therapy
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:24
Hemodialysis II: Procedure and Complications
 01:15
Renal Drug Excretion: Overview
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules...
 01:06
Renal Drug Clearance: Overview
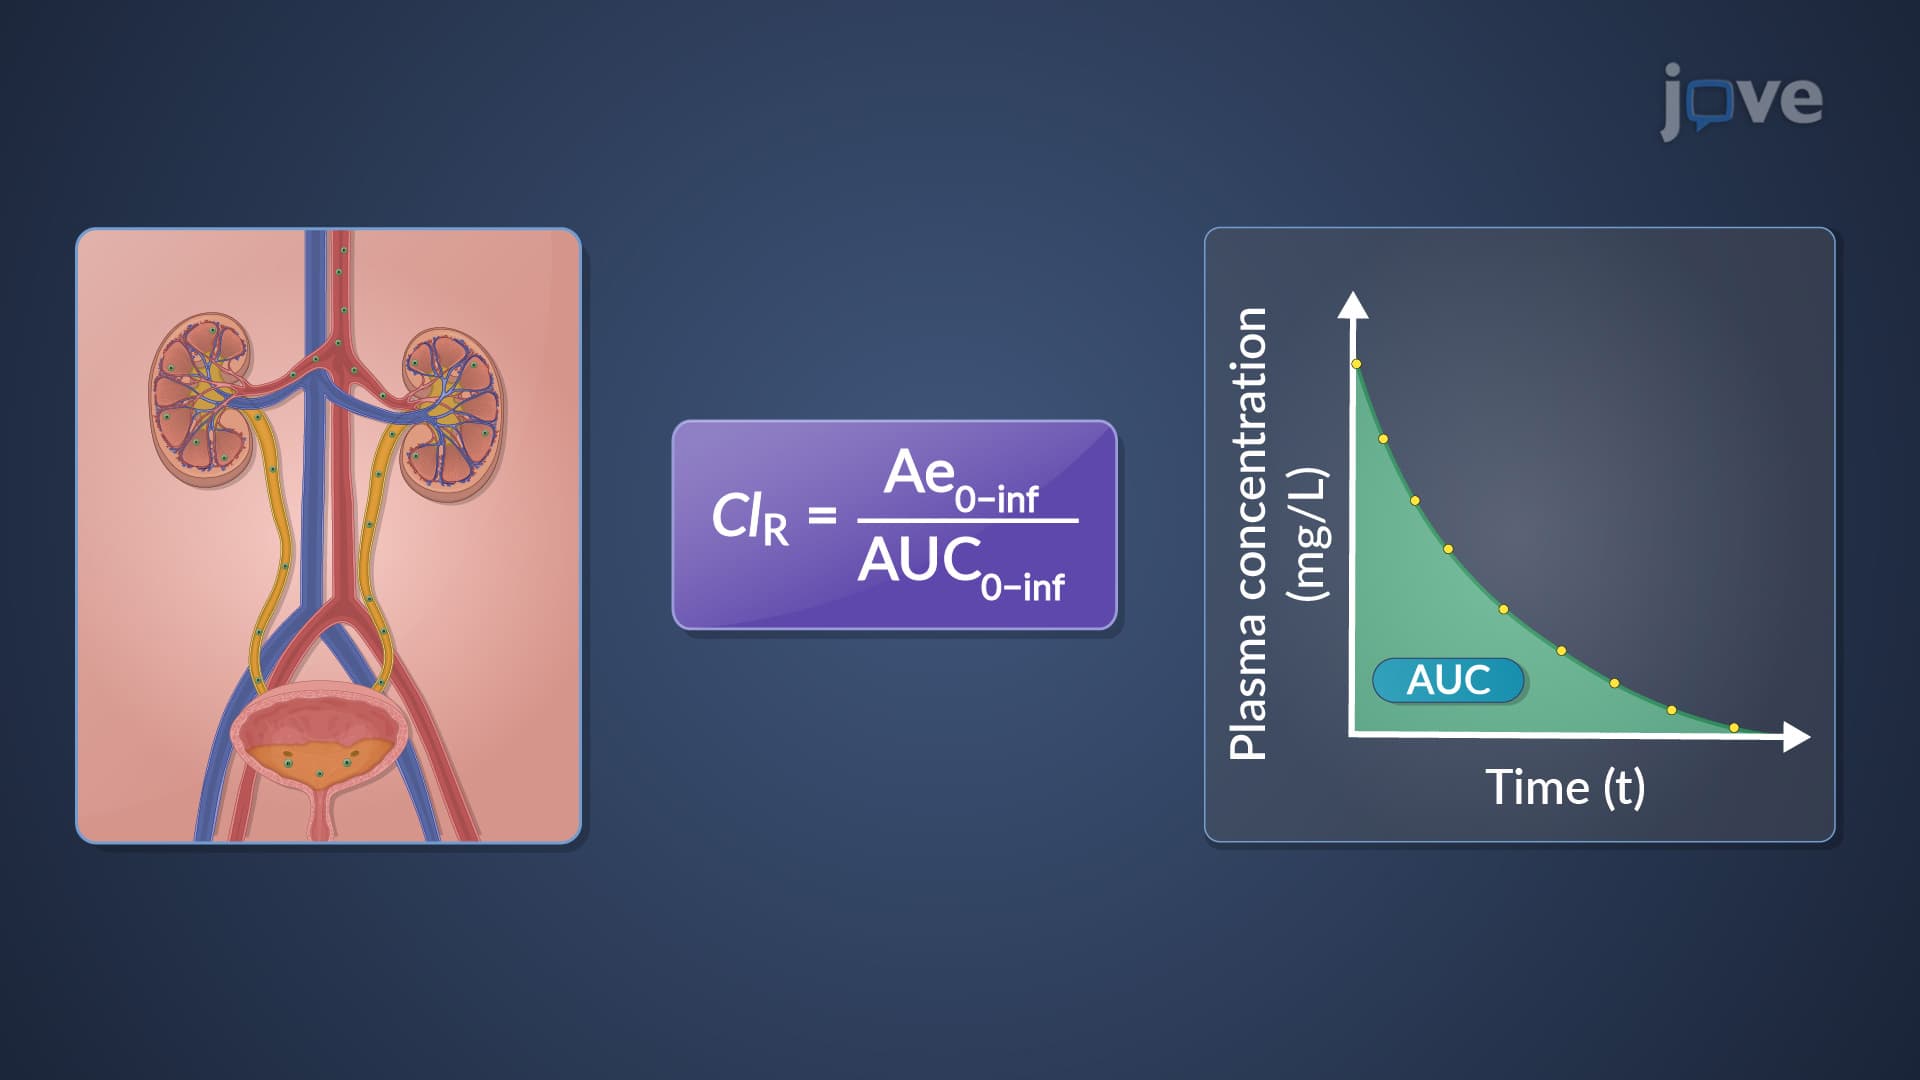
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...