Related Experiment Video
Updated: Oct 1, 2025


Hydra, a Computer-Based Platform for Aiding Clinicians in Cardiovascular Analysis and Diagnosis
Published on: September 26, 2018
Risk Stratification by Cross-Classification of Central and Brachial Systolic Blood Pressure
Yi-Bang Cheng1, Lutgarde Thijs2, Lucas S Aparicio3
1Department of Cardiovascular Medicine, Shanghai Key Laboratory of Hypertension, Shanghai Institute of Hypertension, State Key Laboratory of Medical Genomics, National Research Centre for Translational Medicine, Ruijin Hospital, Shanghai Jiaotong University School of Medicine, China (Y.-B.C., Q.-F.H., C.-S.S., J.-G.W., Y.L.).

Insights
Central hypertension significantly increases cardiovascular and cerebrovascular risk, regardless of brachial blood pressure. Controlling central hypertension is crucial for better health outcomes.
Area of Science:
- Cardiovascular Medicine
- Hypertension Research
- Arterial Properties
Background:
- Debate exists on whether central systolic blood pressure (cSBP) or brachial systolic blood pressure (bSBP) is more closely linked to cardiovascular risk.
- Uncertainty regarding thresholds for differentiating central normotension from hypertension complicates risk assessment.
Purpose of the Study:
- To determine outcome-driven thresholds for central systolic blood pressure (cSBP).
- To investigate if cross-classifying cSBP and bSBP enhances cardiovascular risk stratification.
- To clarify the independent contribution of central hypertension to cardiovascular and cerebrovascular events.
Main Methods:
- A person-level meta-analysis of 5576 individuals from the International Database of Central Arterial Properties for Risk Stratification.
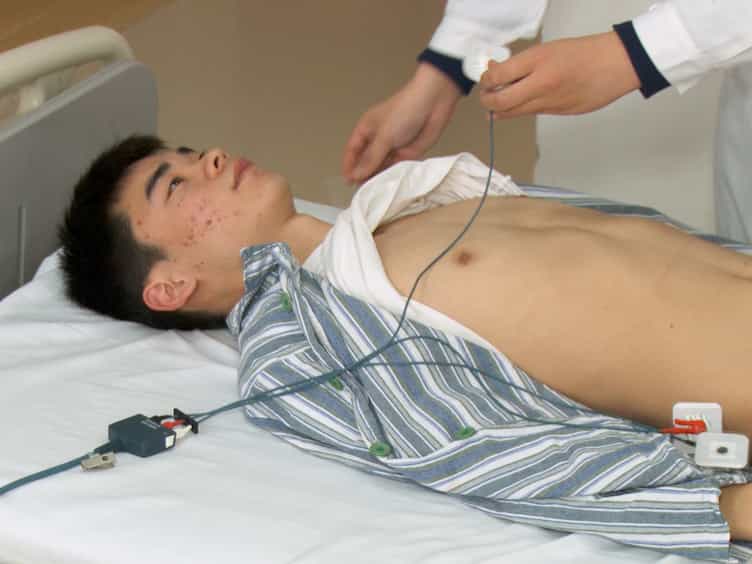
- Central systolic blood pressure (cSBP) was tonometrically estimated from the radial pulse wave.
- Outcome-driven thresholds for cSBP were derived and compared with established brachial systolic blood pressure (bSBP) guidelines.
Main Results:
- cSBP thresholds of 110.5, 120.2, 130.0, and 149.5 mm Hg corresponded to 5-year cardiovascular risks equivalent to bSBP thresholds of 120, 130, 140, and 160 mm Hg, respectively.
- Isolated central hypertension (3.7% of participants) showed a multivariable hazard ratio of 2.28 for cardiovascular events, compared to concordant normotension.
- Central hypertension, independent of brachial blood pressure, elevated cardiovascular and cerebrovascular risk.
Conclusions:
- Central hypertension is a significant independent predictor of cardiovascular and cerebrovascular events.
- The findings underscore the importance of monitoring and controlling central blood pressure for comprehensive cardiovascular risk management.
- Established bSBP thresholds may not fully capture the risk associated with central arterial pressure.
Background:
Whether cardiovascular risk is more tightly associated with central (cSBP) than brachial (bSBP) systolic pressure remains debated, because of their close correlation and uncertain thresholds to differentiate cSBP into normotension versus hypertension.
Methods:
In a person-level meta-analysis of the International Database of Central Arterial Properties for Risk Stratification (n=5576; 54.1% women; mean age 54.2 years), outcome-driven thresholds for cSBP were determined and whether the cross-classification of cSBP and bSBP improved risk stratification was explored. cSBP was tonometrically estimated from the radial pulse wave using SphygmoCor software.
Results:
Over 4.1 years (median), 255 composite cardiovascular end points occurred. In multivariable bootstrapped analyses, cSBP thresholds (in mm Hg) of 110.5 (95% CI, 109.1-111.8), 120.2 (119.4-121.0), 130.0 (129.6-130.3), and 149.5 (148.4-150.5) generated 5-year cardiovascular risks equivalent to the American College of Cardiology/American Heart Association bSBP thresholds of 120, 130, 140, and 160. Applying 120/130 mm Hg as cSBP/bSBP thresholds delineated concordant central and brachial normotension (43.1%) and hypertension (48.2%) versus isolated brachial hypertension (5.0%) and isolated central hypertension (3.7%). With concordant normotension as reference, the multivariable hazard ratios for the cardiovascular end point were 1.30 (95% CI, 0.58-2.94) for isolated brachial hypertension, 2.28 (1.21-4.30) for isolated central hypertension, and 2.02 (1.41-2.91) for concordant hypertension. The increased cardiovascular risk associated with isolated central and concordant hypertension was paralleled by cerebrovascular end points with hazard ratios of 3.71 (1.37-10.06) and 2.60 (1.35-5.00), respectively.
Conclusions:
Irrespective of the brachial blood pressure status, central hypertension increased cardiovascular and cerebrovascular risk indicating the importance of controlling central hypertension.
More Related Videos
Related Concept Videos
 01:23
Assessment of blood pressure in brachial artery(two-step method)
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:15
Assessment of blood pressure in brachial artery(one-step method)
Prepare for the Procedure:
 01:21
Sites for measruring blood pressure
The Brachial Artery: Primary Site for Blood Pressure Measurement
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:28
Hypertension I: Introduction