Related Experiment Video
Updated: Oct 1, 2025
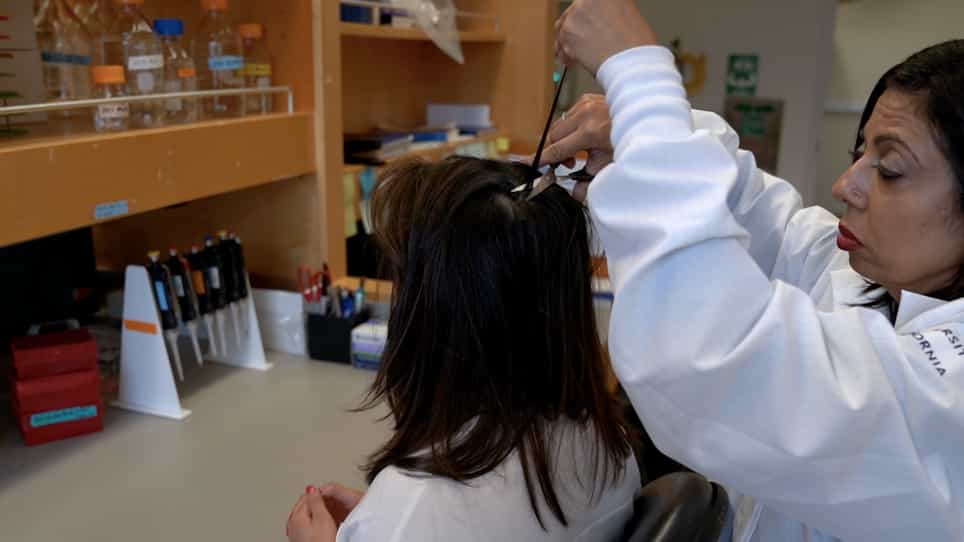

Validated LC-MS/MS Panel for Quantifying 11 Drug-Resistant TB Medications in Small Hair Samples
Published on: May 19, 2020
Prediction of lung exposure to anti-tubercular drugs using plasma pharmacokinetic data: Implications for dose
Morris Muliaditan1, Donato Teutonico2, Fatima Ortega-Muro3
1Clinical Pharmacology & Therapeutics Group, University College London, London, UK.

Abstract:
The development of novel candidate molecules for tuberculosis remains challenging, as drug distribution into the target tissue is not fully characterised in preclinical models of infection. Often antitubercular human dose selection is derived from pharmacokinetic data in plasma. Here, we explore whether whole-body physiologically-based pharmacokinetic (PBPK) modelling enables the prediction of lung exposure to anti-tubercular drugs in humans. Whole-body PBPK models were developed for rifampicin, isoniazid, pyrazinamide, and ethambutol using plasma data in mice as basis for the prediction of lung exposure. Model parameters were subsequently used to extrapolate disposition properties from mouse and determine lung:plasma ratio in humans. Model predictions were compared to biopsy data from patients. Predictions were deemed adequate if they fell within two-fold range of the observations. The concentration vs time profiles in lung were adequately predicted in mice. Isoniazid and pyrazinamide lung exposures were predicted to be comparable to plasma levels, whereas ethambutol lung exposure was predicted to be higher than in plasma. Lung:plasma ratio in humans could be reasonably predicted from preclinical data, but was highly dependent on the distribution model. This analysis showed that plasma pharmacokinetics may be used in conjunction with PBPK modelling to derive lung tissue exposure in mice and humans during early lead optimisation phase. However, the impact of uncertainty in predicted tissue exposure due to distribution should be always investigated through a sensitivity analysis when only plasma data is available. Despite these limitations, insight into lung tissue distribution represents a critical step for the dose rationale in tuberculosis patients.

Related Concept Videos
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the...
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:26
Pharmacokinetic Models: Comparison and Selection Criterion
Physiological models take a detailed approach by considering specific molecular processes. They can predict drug distribution, metabolism, and elimination changes, providing a comprehensive understanding of how drugs interact with the body.
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 00:59
Model-Independent Approaches for Pharmacokinetic Data: Noncompartmental Analysis
One important characteristic of noncompartmental analyses is that drug exposure increases proportionally with increasing doses. This...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories: