Related Experiment Video
Updated: Sep 30, 2025
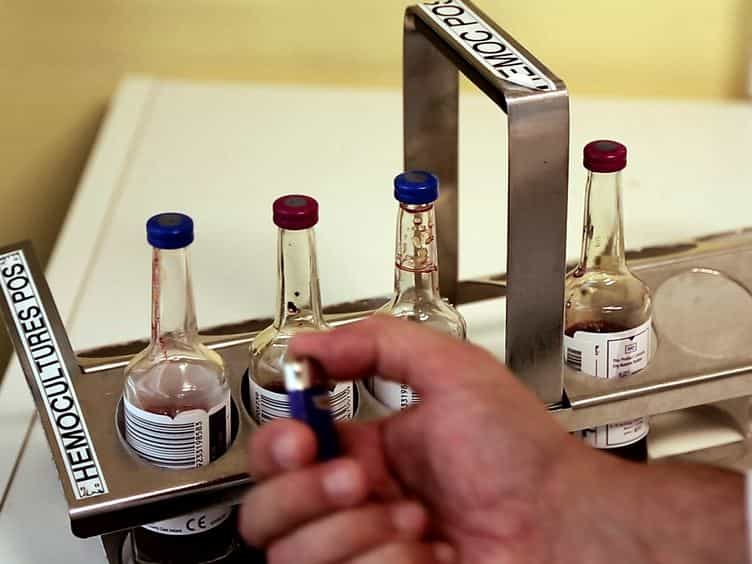

Preparation of a Blood Culture Pellet for Rapid Bacterial Identification and Antibiotic Susceptibility Testing
Published on: October 15, 2014
Time to positivity of blood cultures in neonatal late-onset bacteraemia
Sagori Mukhopadhyay1,2,3, Sara M Briker4,5, Dustin D Flannery4,2,3
1Division of Neonatology, Children's Hospital of Philadelphia, Philadelphia, Pennsylvania, USA mukhopadhs@email.chop.edu.

Insights
Stopping empiric antibiotics at 36 hours for late-onset infant infections is feasible, avoiding unnecessary antibiotic exposure. However, longer durations are advised if antibiotics were previously given or if treating coagulase-negative staphylococci (CoNS).
Area of Science:
- Neonatal Medicine
- Infectious Diseases
- Clinical Microbiology
Background:
- Late-onset bacteraemia in infants poses diagnostic challenges.
- Timely identification of bloodstream infections is crucial for appropriate treatment.
- Current practices may involve prolonged empiric antibiotic use.
Purpose of the Study:
- To determine the time to positivity (TTP) of blood cultures in infants with late-onset bacteraemia.
- To identify predictors associated with a TTP exceeding 36 hours.
- To inform optimal duration of empiric antibiotic therapy.
Main Methods:
- Retrospective cohort study involving 16 birth centers across two healthcare systems.
- Analysis of blood cultures from infants with positive results obtained >72 hours after birth.
- Multivariable analysis to identify factors associated with TTP >36 hours.
Main Results:
- The median TTP for 428 bacterial cultures was 23.5 hours, with 85% positive within 36 hours.
- Excluding coagulase-negative staphylococci (CoNS), 93.5% of cultures were positive by 36 hours.
- CoNS isolation and antibiotic pretreatment were significantly associated with TTP >36 hours.
Conclusions:
- Empiric antibiotic use for late-onset infections (excluding CoNS) can potentially cease at 36 hours.
- Consider extending antibiotic duration to 48 hours if pretreatment occurred or if treating CoNS.
- This approach could significantly reduce antibiotic exposure in neonates.
Objective:
To determine the time to positivity (TTP) of blood cultures among infants with late-onset bacteraemia and predictors of TTP >36 hours.
Design:
Retrospective cohort study.
Setting:
16 birth centres in two healthcare systems.
Patients:
Infants with positive blood cultures obtained >72 hours after birth.
Outcome:
The main outcome was TTP, defined as the time interval from specimen collection to when a neonatal provider was notified of culture growth. TTP analysis was restricted to the first positive culture per infant. Patient-specific and infection-specific factors were analysed for association with TTP >36 hours.
Results:
Of 10 235 blood cultures obtained from 3808 infants, 1082 (10.6%) were positive. Restricting to bacterial pathogens and the first positive culture, the median TTP (25th-75th percentile) for 428 cultures was 23.5 hours (18.4-29.9); 364 (85.0%) resulted in 36 hours. Excluding coagulase-negative staphylococci (CoNS), 275 of 294 (93.5%) cultures were flagged positive by 36 hours. In a multivariable model, CoNS isolation and antibiotic pretreatment were significantly associated with increased odds of TTP >36 hours. Projecting a 36-hour empiric duration at one site and assuming that all negative evaluations were associated with an empiric course of antibiotics, we estimated that 1164 doses of antibiotics would be avoided in 629 infants over 10 years, while delaying a subsequent antibiotic dose in 13 infants with bacteraemia.
Conclusions:
Empiric antibiotic administration in late-onset infection evaluations (not targeting CoNS) can be stopped at 36 hours. Longer durations (48 hours) should be considered when there is pretreatment or antibiotic therapy is directed at CoNS.
Related Concept Videos
 01:26
Urine Studies II: Urine Culture and Sensitivity Test
 01:20
Sputum Studies II: Culture and Sensitivity
Sputum culture and sensitivity is a medical procedure used to diagnose bacterial infections in the respiratory tract and select the most appropriate antibiotics for treatment. This process involves analyzing sputum samples of thick and opaque secretions produced in the lungs and airways. These samples are collected from patients and then sent to the laboratory for analysis.
The test can identify various pathogens responsible for respiratory infections, including Streptococcus,...