Related Experiment Video
Updated: Sep 30, 2025
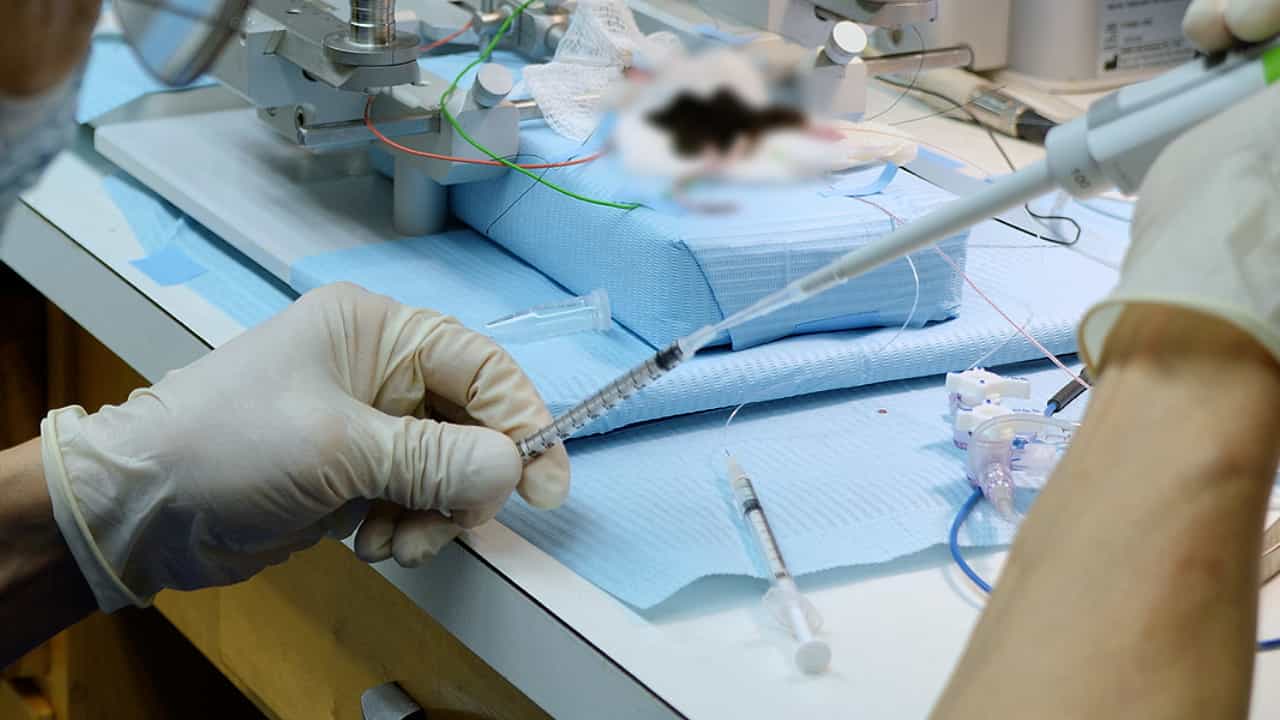
Author Spotlight: A Unique Mouse Model of Asphyxia-Induced Cardiac Arrest
Published on: April 14, 2023
SSEP N20 and P25 amplitudes predict poor and good neurologic outcomes after cardiac arrest
Sarah Benghanem1,2,3,4, Lee S Nguyen5, Martine Gavaret6,7,8
1Medical ICU, Cochin Hospital, AP-HP, 27 rue du Faubourg Saint-Jacques, 75014, Paris, France. sarah.benghanem@aphp.fr.

Background:
To assess in comatose patients after cardiac arrest (CA) if amplitudes of two somatosensory evoked potentials (SSEP) responses, namely, N20-baseline (N20-b) and N20-P25, are predictive of neurological outcome.
Methods:
Monocentric prospective study in a tertiary cardiac center between Nov 2019 and July-2021. All patients comatose at 72 h after CA with at least one SSEP recorded were included. The N20-b and N20-P25 amplitudes were automatically measured in microvolts (µV), along with other recommended prognostic markers (status myoclonus, neuron-specific enolase levels at 2 and 3 days, and EEG pattern). We assessed the predictive value of SSEP for neurologic outcome using the best Cerebral Performance Categories (CPC1 or 2 as good outcome) at 3 months (main endpoint) and 6 months (secondary endpoint). Specificity and sensitivity of different thresholds of SSEP amplitudes, alone or in combination with other prognostic markers, were calculated.
Results:
Among 82 patients, a poor outcome (CPC 3-5) was observed in 78% of patients at 3 months. The median time to SSEP recording was 3(2-4) days after CA, with a pattern "bilaterally absent" in 19 patients, "unilaterally present" in 4, and "bilaterally present" in 59 patients. The median N20-b amplitudes were different between patients with poor and good outcomes, i.e., 0.93 [0-2.05]µV vs. 1.56 [1.24-2.75]µV, respectively (p < 0.0001), as the median N20-P25 amplitudes (0.57 [0-1.43]µV in poor outcome vs. 2.64 [1.39-3.80]µV in good outcome patients p < 0.0001). An N20-b > 2 µV predicted good outcome with a specificity of 73% and a moderate sensitivity of 39%, although an N20-P25 > 3.2 µV was 93% specific and only 30% sensitive. A low voltage N20-b < 0.88 µV and N20-P25 < 1 µV predicted poor outcome with a high specificity (sp = 94% and 93%, respectively) and a moderate sensitivity (se = 50% and 66%). Association of "bilaterally absent or low voltage SSEP" patterns increased the sensitivity significantly as compared to "bilaterally absent" SSEP alone (se = 58 vs. 30%, p = 0.002) for prediction of poor outcome.
Conclusion:
In comatose patient after CA, both N20-b and N20-P25 amplitudes could predict both good and poor outcomes with high specificity but low to moderate sensitivity. Our results suggest that caution is needed regarding SSEP amplitudes in clinical routine, and that these indicators should be used in a multimodal approach for prognostication after cardiac arrest.
More Related Videos
 06:18
A Bedside, Single Burr Hole Approach to Multimodality Monitoring in Severe Brain Injury
Published on: March 26, 2019
 08:28
Methods for ECG Evaluation of Indicators of Cardiac Risk, and Susceptibility to Aconitine-induced Arrhythmias in Rats Following Status Epilepticus
Published on: April 5, 2011
Related Concept Videos
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:23
Cardiopulmonary Resuscitation III: AED Use