Related Experiment Video
Updated: Sep 29, 2025


Signal Acquisition, Score Interpretation, and Economics of a Non-Invasive Point-of-Care Test for Coronary Artery Disease
Published on: August 9, 2024
Diagnostic efficacy of CCTA and CT-FFR based on risk factors for myocardial ischemia
Gao Yongguang1, Shi Yibing2, Xia Ping1
1Department of Radiology, Xuzhou Central Hospital, 199 Jiefang Road, Xuzhou, Jiangsu, China.

Insights
Coronary artery computed tomography angiography (CCTA) combined with computed tomography-derived fractional flow reserve (CT-FFR) can diagnose myocardial ischemia. Plaque volume, length, and lumen stenosis are key predictors of ischemia.
Area of Science:
- Cardiology
- Medical Imaging
- Computational Physiology
Background:
- Coronary artery computed tomography angiography (CCTA) assesses coronary artery stenosis.
- Fractional flow reserve (FFR) diagnoses hemodynamic abnormalities.
- Simultaneous noninvasive assessment of both anatomical and functional significance of coronary lesions remains an area for investigation.
Purpose of the Study:
- To investigate the diagnostic efficacy of CCTA and CT-derived FFR (CT-FFR) in identifying myocardial ischemia.
- To explore the relationship between coronary plaque characteristics and myocardial ischemia.
Main Methods:
- Patients undergoing CCTA were selected for CT-FFR analysis.
- Vascular characteristics including plaque volume, plaque length, and lumen stenosis were measured.
- Logistic regression analysis was used to correlate plaque characteristics with ischemic lesions (FFR ≤ 0.8).
Main Results:
- Significant differences in total plaque volume, calcified plaque volume, plaque length, and lumen stenosis (>50%) were observed between ischemic and non-ischemic groups.
- Total plaque volume, calcified plaque volume, plaque length, and lumen stenosis >50% were identified as significant predictors of myocardial ischemia.
Conclusions:
- Coronary artery CCTA combined with CT-FFR offers simultaneous assessment of anatomical stenosis and functional blood supply.
- Plaque characteristics such as total plaque volume, calcified plaque volume, plaque length, and lumen stenosis are significant predictors of myocardial ischemia.
- This combined approach improves the diagnosis of myocardial ischemia.
Background:
Coronary artery coronary computed tomography angiography (CCTA) can observe the degree of coronary artery stenosis and fractional flow reserve (FFR) can diagnose hemodynamic abnormalities caused by coronary artery stenosis. However, noninvasive imaging examination that can both observe the above two methods at the same time has not yet been elucidated.
Objective:
To investigate the diagnostic efficacy of CCTA and computed tomography-derived fractional flow reserve (CT-FFR) based on different risk factors for myocardial ischemia.
Methods:
Patients undergoing CCTA in our hospital from August 18, 2020 to April 28, 2021 were randomly selected, and the data were subjected to CT-FFR analysis. Vascular characteristics were measured, including total plaque volume, calcified plaque volume, non-calcified plaque volume, plaque length, and lumen stenosis, and the patients were categorized into a non-ischemia group (FFR > 0.8) and an ischemia group (FFR ≤ 0.8). Plaque characteristics were compared between the two groups, and logistic regression analysis was employed to explore the correlations between plaque characteristics and ischemic lesions.
Results:
From a total of 122 patients enrolled in the study, there were 218 vascular branches with FFR > 0.8 and 174 vascular branches with FFR ≤ 0.8. There were significant group differences in total plaque volume, calcified plaque volume, plaque length, and lumen stenosis > 50% (n). The obtained data were as follows: non-ischemic group 10.57 (4.80, 259.65), ischemic group 14.87 (3.39, 424.45), Z = 9.772, p = 0.002, non-ischemic group 10.57 (0, 168.77), ischemic group 14.87 (0, 191.00), Z = 2.503, p ≤ 0.001), non-ischemic group 8.17 (37.05, 40.53), ischemic group 8.38 (56.66, 86.47), Z = 5.923, p = 0.016, and lumen stenosis > 50%, non-ischemic group 46, ischemic group 90, x2 = 14.77, p ≤ 0.001. The regression analysis results indicated that total plaque volume, calcified plaque volume, plaque length and lumen stenosis > 50% were risk factors for myocardial ischemia, with ORs and p values of (2.311, p = 0.002), (1.021, p = 0.004), (2.159, p < 0.001), and (0.181, p < 0.001), respectively.
Conclusion:
Total plaque volume, calcified plaque volume, plaque length and lumen stenosis > 50% are predictors for myocardial ischemia. Coronary artery CCTA combined with CT-FFR could simultaneously observe the anatomical stenosis and evaluate myocardial blood supply at the functional level. Thus, myocardial ischemia could be better diagnosed.
More Related Videos
 04:40
Identifying Coronary Artery Calcification on Non-gated Computed Tomography Scans
Published on: August 28, 2018
 18:11
A Research Method For Detecting Transient Myocardial Ischemia In Patients With Suspected Acute Coronary Syndrome Using Continuous ST-segment Analysis
Published on: December 28, 2012
Related Concept Videos
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:28
Imaging Studies for Cardiovascular System V: CT
 01:30
Dysrhythmias V: Evaluating Dysrhythmias
 01:21
Imaging Studies for Cardiovascular System IV: CMRI
 01:26
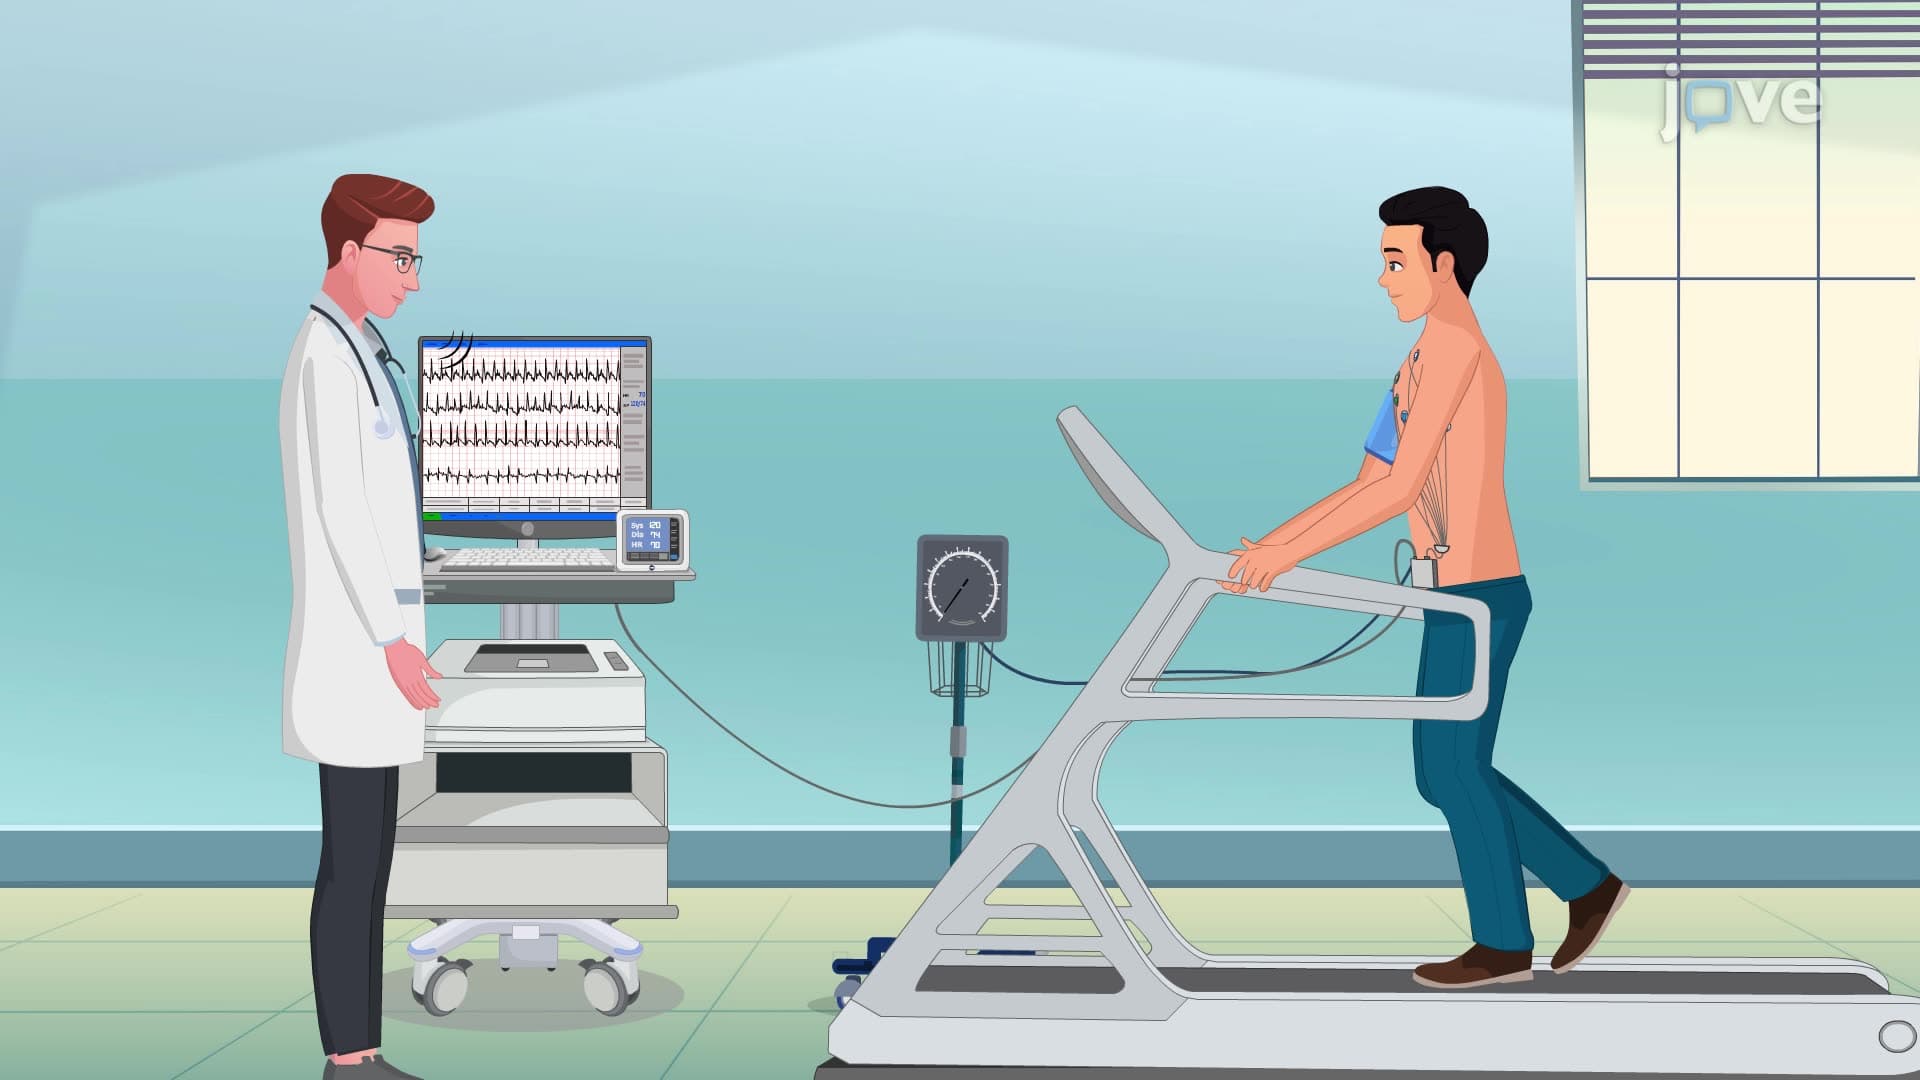
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes