Abnormal exercise adaptation after varying severities of COVID-19: A controlled cross-sectional analysis of 392 survivors

Fabrício Braga1,2, Fernanda Domecg1,3, Marcelo Kalichsztein2
1Laboratório de Performance Humana, Rio de Janeiro, Brazil.

Abstract:
The multisystem impairment promoted by COVID-19 may be associated with a reduction in exercise capacity. Cardiopulmonary abnormalities can change across the acute disease severity spectrum. We aimed to verify exercise physiology differences between COVID-19 survivors and SARS-CoV-2-naïve controls and how illness severity influences exercise limitation. A single-centre cross-sectional analysis of prospectively collected data from COVID-19 survivors who underwent cardiopulmonary exercise testing (CPET) in their recovery phase (x = 50[36;72] days). Patients with COVID-19 were stratified according to severity as mild [M-Cov (outpatient)] vs severe/critical [SC-Cov(inpatients)] and were compared with SARS-CoV-2-naïve controls (N-Cov). Collected information included demographics, anthropometrics, previous physical exercise, comorbidities, lung function test and CPET parameters. A multivariate logistic regression analysis was performed to identify low aerobic capacity (LAC) predictors post COVID-19. Of the 702 included patients, 310 (44.2%), 305 (43.4%) and 87 (12.4%) were N-Cov, M-Cov and SC-Cov, respectively. LAC was identified in 115 (37.1%), 102 (33.4%), and 66 (75.9%) of N-CoV, M-CoV and SC-CoV, respectively (p < 0.001). SC-Cov were older, heavier with higher body fat, more sedentary lifestyle, more hypertension and diabetes, lower forced vital capacity, higher prevalence of early anaerobiosis, ventilatory inefficiency and exercise-induced hypoxia than N-Cov. M-Cov had lower weight, fat mass, and coronary disease prevalence and did not demonstrate more CEPT abnormalities than N-Cov. After adjustment for covariates, SC-Cov was an independent predictor of LAC (OR = 2.7; 95% CI, 1.3-5.6). Almost two months after disease onset, SC-CoV presented several exercise abnormalities of oxygen uptake, ventilatory adaptation and gas exchange, including a high prevalence of LAC.Highlights Weeks after the acute disease phase, one-third of mild and three-quarters of severe and critical patients with COVID-19 presented a reduced aerobic capacity. Previous studies including SARS-CoV-1 survivors observed much lower values.A severe or critical COVID-19 case was an independent predictor for low aerobic capacity.In our sample, pre-COVID-19 exercise significantly reduced the odds of post-COVID-19 low aerobic capacity. Even severe or critical patients who exercised regularly had a prevalence of low aerobic capacity 2.5 times lower than those who did not have this routine before sickening.
More Related Videos
 07:26
Conducting Maximal and Submaximal Endurance Exercise Testing to Measure Physiological and Biological Responses to Acute Exercise in Humans
Published on: October 17, 2018
 07:10
Home-Based Prescribed Pulmonary Exercise in Patients with Stable Chronic Obstructive Pulmonary Disease
Published on: August 24, 2019
Related Concept Videos
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
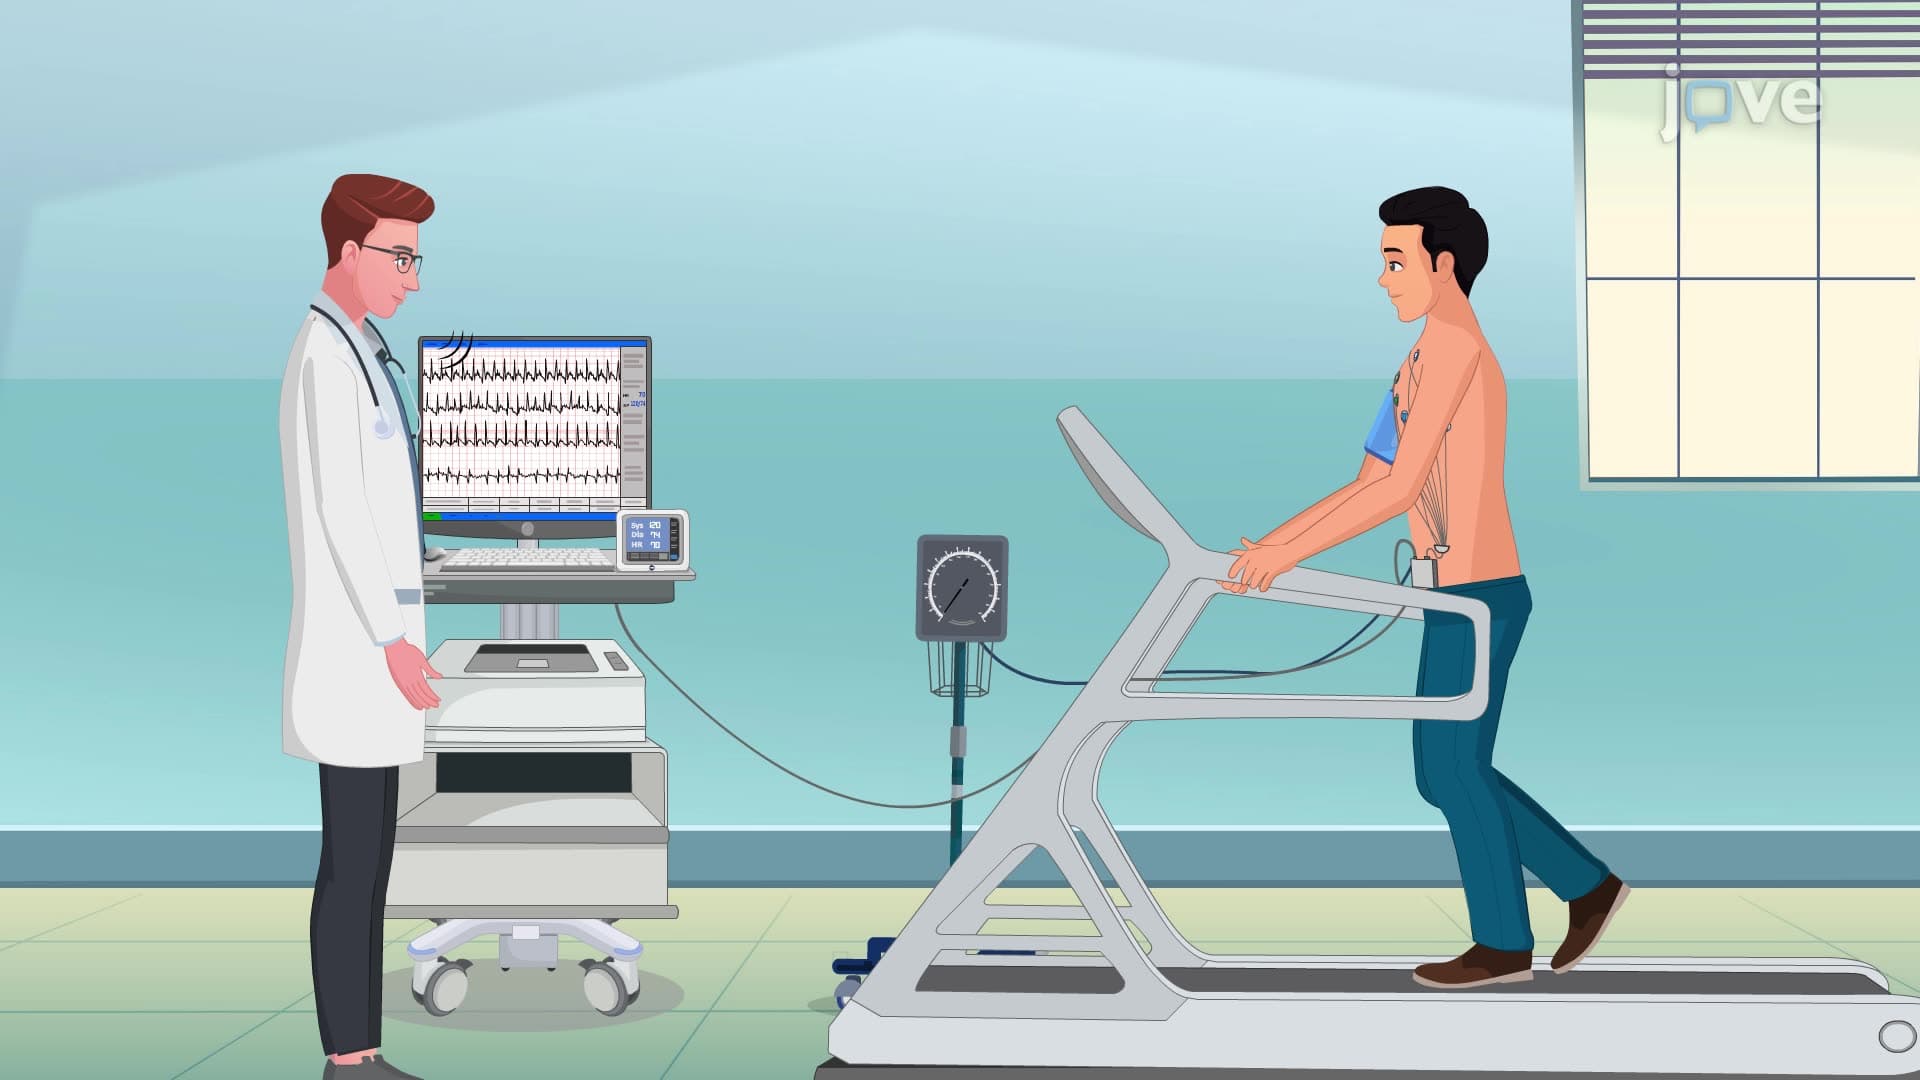 01:26
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...