Related Experiment Video
Updated: Sep 29, 2025
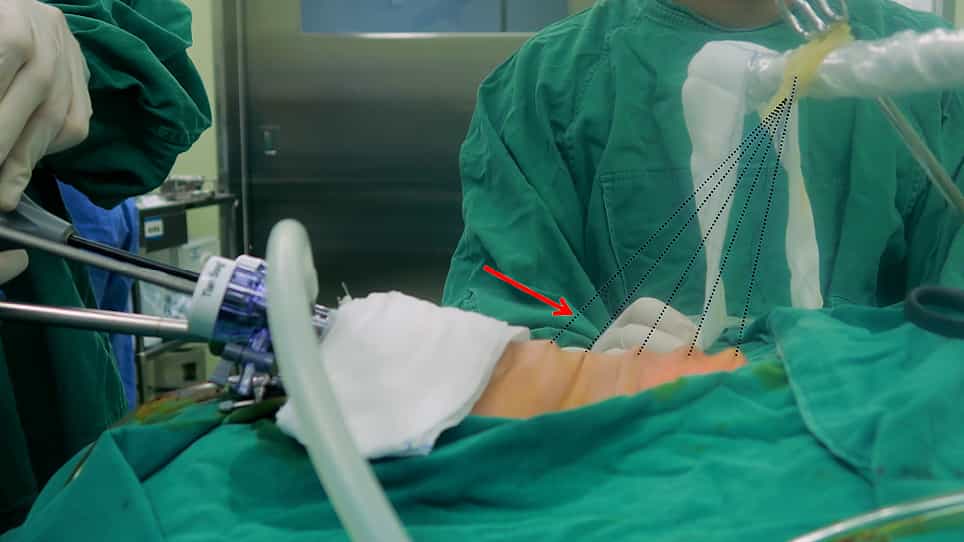

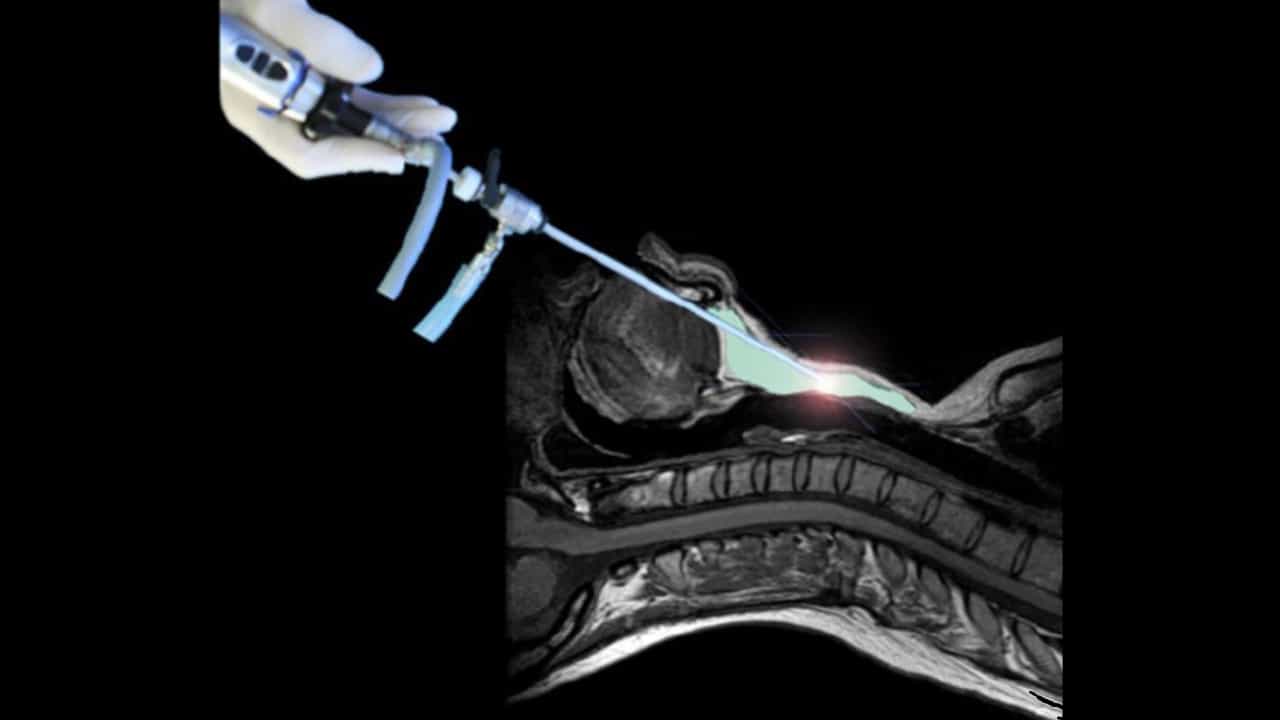
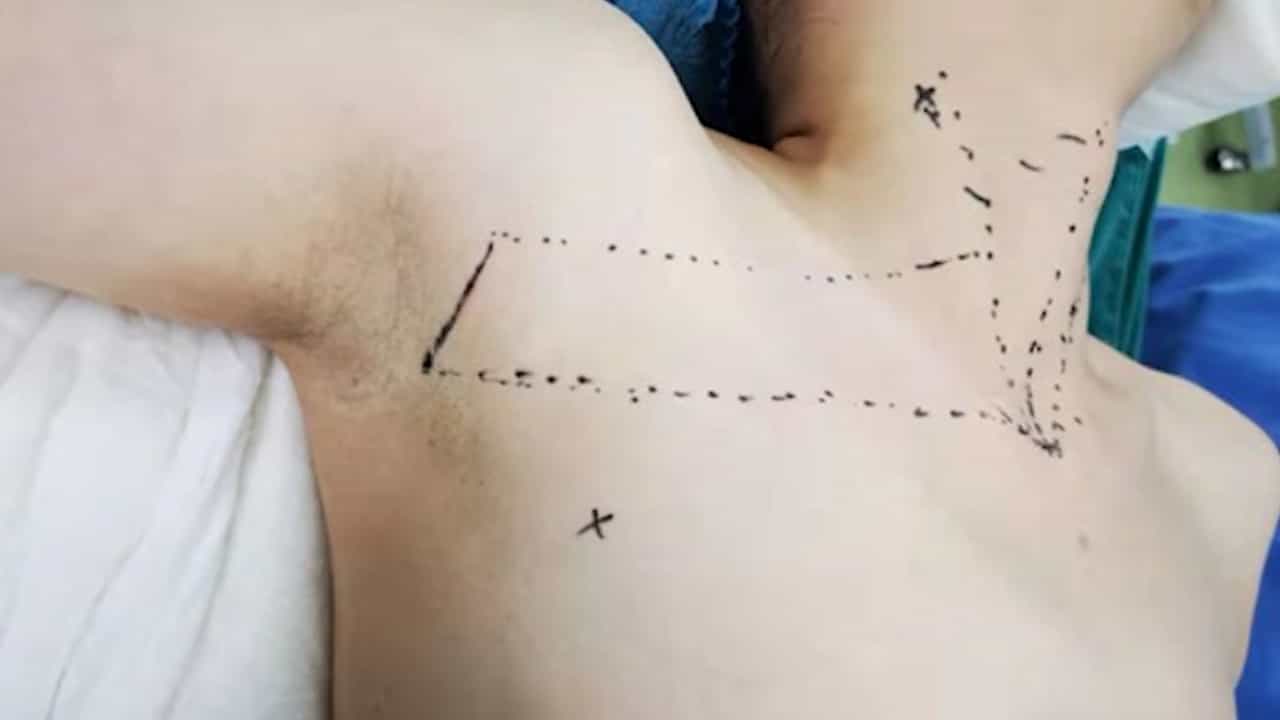
Transoral Endoscopic Thyroidectomy Vestibular Approach for Thyroid Lobectomy
Published on: May 12, 2023
Comparison Between Transoral Endoscopic Thyroidectomy Vestibular Approach (TOETVA) and Conventional Open
Haiqing Sun1, Xiaojie Wang1, Guibin Zheng1
1Department of Thyroid Surgery, The Affiliated Yantai Yuhuangding Hospital of Qingdao University, Yantai, China.

Background:
Use of the novel transoral endoscopic thyroidectomy vestibular approach (TOETVA) is increasing worldwide. Although several studies have compared safety and efficacy of TOETVA and other approaches, most focused on comparisons in the context of unilateral thyroidectomy. Therefore, the present study aimed to compare the safety and surgical completeness of TOETVA with conventional open thyroidectomy (COT) in patients with papillary thyroid carcinoma (PTC) undergoing total thyroidectomy and central neck dissection.
Methods:
The medical records of patients who underwent TOETVA or COT by a single surgeon between June 2017 and October 2021 were retrospectively reviewed. All patients were diagnosed with PTC and underwent total thyroidectomy with central neck dissection. Propensity score-matching (PSM) was used to reduce potential selection bias and to adjust for differences in baseline clinicopathological characteristics.
Results:
After PSM, 84 (TOETVA: 28; COT: 56) patients remained in the study population. There were no significant differences in sex, mean age, combined thyroiditis, tumor size, capsule invasion, tumor multifocality in the same lobe, or tumor location between the groups. Operative time was longer (190.54 ± 28.26 vs. 123.93 ± 29.78 min, P<0.001), while postoperative drainage volume (161.07 ± 225.30 vs. 71.16 ± 28.56 ml, P=0.045) was greater, in the TOETVA group than in the COT group. The groups exhibited no significant differences in the mean number of central lymph nodes retrieved (9.39 ± 4.01 vs. 10.71 ± 5.17, P=0.202), mean number of metastatic central lymph nodes (1.36 ± 1.93 vs. 1.77 ± 2.31, P=0.421), postoperative mean thyroglobulin levels (0.08 ± 0.24 vs. 0.10 ± 0.27, P=0.686), rate of transient hypoparathyroidism (TOETVA: 67.9% vs. COT: 66.1%, P=0.870), rate of transient vocal cord palsy (TOETVA: 0% vs. COT: 1.8%, P=1.000), or other complications (TOETVA: 3.6% vs. COT: 0%, P=0.333).
Conclusions:
TOETVA is a safe approach in select patients with PTC and exhibits similar efficacy to COT in terms of surgical completeness.