Related Experiment Video
Updated: Sep 29, 2025

Management of the Uncinate Process in No-Touch Laparoscopic Pancreaticoduodenectomy
Published on: May 5, 2023
Case 300: Ruptured Mucinous Cystadenoma of the Pancreas
Isha Sharma1, Chandan Kakkar1, Vikram Narang1
1From the Departments Radiodiagnosis and Imaging (I.S. C.K., K.S.), Pathology (V.N.), and Gastrosurgery (S.S.V.), Dayanand Medical College and Hospital, Tagore Nagar, Ludhiana Punjab, India 141001.

Abstract:
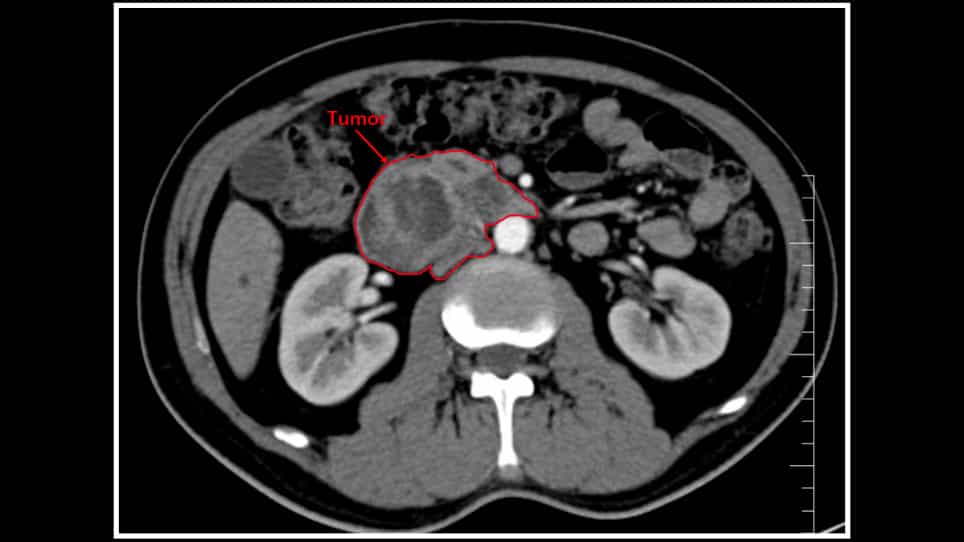
History Part one of this case appeared 4 months previously and may contain larger images. A 40-year-old woman presented to the outpatient department of our hospital with a 2-year history of abdominal pain, which had worsened in the past few days. There were no other constitutional symptoms; in particular, there was no weight loss or loss of appetite. The serum amylase and serum lipase levels were always within normal limits, even during the current episode. There was no history of pancreatitis, alcohol abuse, drug use, or trauma. The patient was evaluated at an outside clinic 2 years ago and underwent imaging, including US and dedicated pancreatic CT, which revealed a complex multiseptated noncalcified pancreatic cystic lesion. After CT, the patient underwent endoscopic US, which showed the lesion was suspected to be an infected parasitic cyst; fine-needle aspiration and cytology were not attempted due to the risk of iatrogenic rupture. The patient was advised to undergo surgical resection but declined the procedure and was lost to follow-up for 2 years before her current visit to our facility. On clinical examination, there were no clinically important findings, aside from mild to moderate pain on deep palpation and some shifting dullness that was suggestive of ascites. The patient always remained hemodynamically stable. US-guided ascitic fluid analysis was performed, which revealed amylase levels of 869 IU/L (normal range, 4-234 IU/L). Considering prior CT and endoscopic US reports, the patient was further evaluated with a pancreatic MRI protocol for lesion characterization and to explain the new-onset abdominal pain.
Related Concept Videos
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include: