Related Experiment Video
Updated: Sep 29, 2025


Competing-Risk Nomogram for Predicting Cancer-Specific Survival in Multiple Primary Colorectal Cancer Patients after Surgery
Published on: September 27, 2024
Chemotherapy predictors and a time-dependent chemotherapy effect in metastatic esophageal cancer
Lauren Midthun1, Sungjin Kim2, Andrew Hendifar3
1Department of Medicine, Division of Hematology and Oncology, Cedars-Sinai Medical Center, Los Angeles, CA 90048, United States.

Background:
Chemotherapy has long been shown to confer a survival benefit in patients with metastatic esophageal cancer. However, not all patients with metastatic disease receive chemotherapy.
Aim:
To evaluate a large cancer database of metastatic esophageal cancer cases to identify predictors of receipt to chemotherapy and survival.
Methods:
We interrogated the National Cancer Database (NCDB) between 2004-2015 and included patients with M1 disease who had received or did not receive chemotherapy. A logistic regression model was used to examine the associations between chemotherapy and potential confounders and a Cox proportional hazards model was employed to examine the effect of chemotherapy on overall survival (OS). Propensity score analyses were further performed to balance measurable confounders between patients treated with and without chemotherapy.
Results:
A total of 29182 patients met criteria for inclusion in this analysis, with 21911 (75%) receiving chemotherapy and 7271 (25%) not receiving chemotherapy. The median follow-up was 69.45 mo. The median OS for patients receiving chemotherapy was 9.53 mo (9.33-9.72) vs 2.43 mo (2.27-2.60) with no chemotherapy. Year of diagnosis 2010-2014 [odds ratio (OR): 1.29, 95% confidence interval (CI): 1.17-1.43, P value < 0.001], median income > $46000 (OR: 1.49, 95%CI: 1.27-1.75, P value < 0.001), and node-positivity (OR: 1.35, 95%CI: 1.20-1.52, P < 0.001) were independent predictors of receiving chemotherapy, while female gender (OR: 0.86, 95%CI: 0.76-0.98, P = 0.019), black race (OR: 0.76, 95%CI: 0.67-0.93, P = 0.005), uninsured status (OR: 0.41, 95%CI: 0.33-0.52, P < 0.001), and high Charlson Comorbidity Index (CCI) (OR for CCI ≥ 2: 0.61, 95%CI: 0.50-0.74, P < 0.001) predicted for lower odds of receiving chemotherapy. Modeling the effect of chemotherapy on OS using a time-dependent coefficient showed that chemotherapy was associated with improved OS up to 10 mo, after which there is no significant effect on OS. Moreover, uninsured status [hazard ratio (HR): 1.20, 95%CI: 1.09-1.31, P < 0.001], being from the geographic Midwest (HR: 1.07, 95%CI: 1.01-1.14, P = 0.032), high CCI (HR for CCI ≥ 2: 1.16, 95%CI: 1.07-1.26, P < 0.001), and higher tumor grade (HR for grade 3 vs grade 1: 1.28, 95%CI: 1.14-1.44, P < 0.001) and higher T stage (HR for T1 vs T4: 0.89, 95%CI: 0.84-0.95, P < 0.001) were independent predictors of worse OS on multivariable analyses.
Conclusion:
In this large, retrospective NCDB analysis, we identified several socioeconomic and clinicopathologic predictors for receiving chemotherapy and OS in patients with metastatic esophageal cancer. The benefit of chemotherapy on OS is time-dependent and favors early initiation. Focused outreach in lower income and underinsured patients is critical as receipt of chemotherapy is associated with improved OS.


Related Concept Videos
 01:27
Chemotherapy-Induced Nausea and Vomiting: 5-HT3 Receptor Antagonists
 02:57
Targeted Cancer Therapies
There are several types of targeted therapies against...
 02:50
Combination Therapies and Personalized Medicine
The combination of the drug acetazolamide and sulforaphane is a good example of combination therapy to treat cancer. The cells in the interior of a large tumor often die due to the hypoxic and...
 01:20
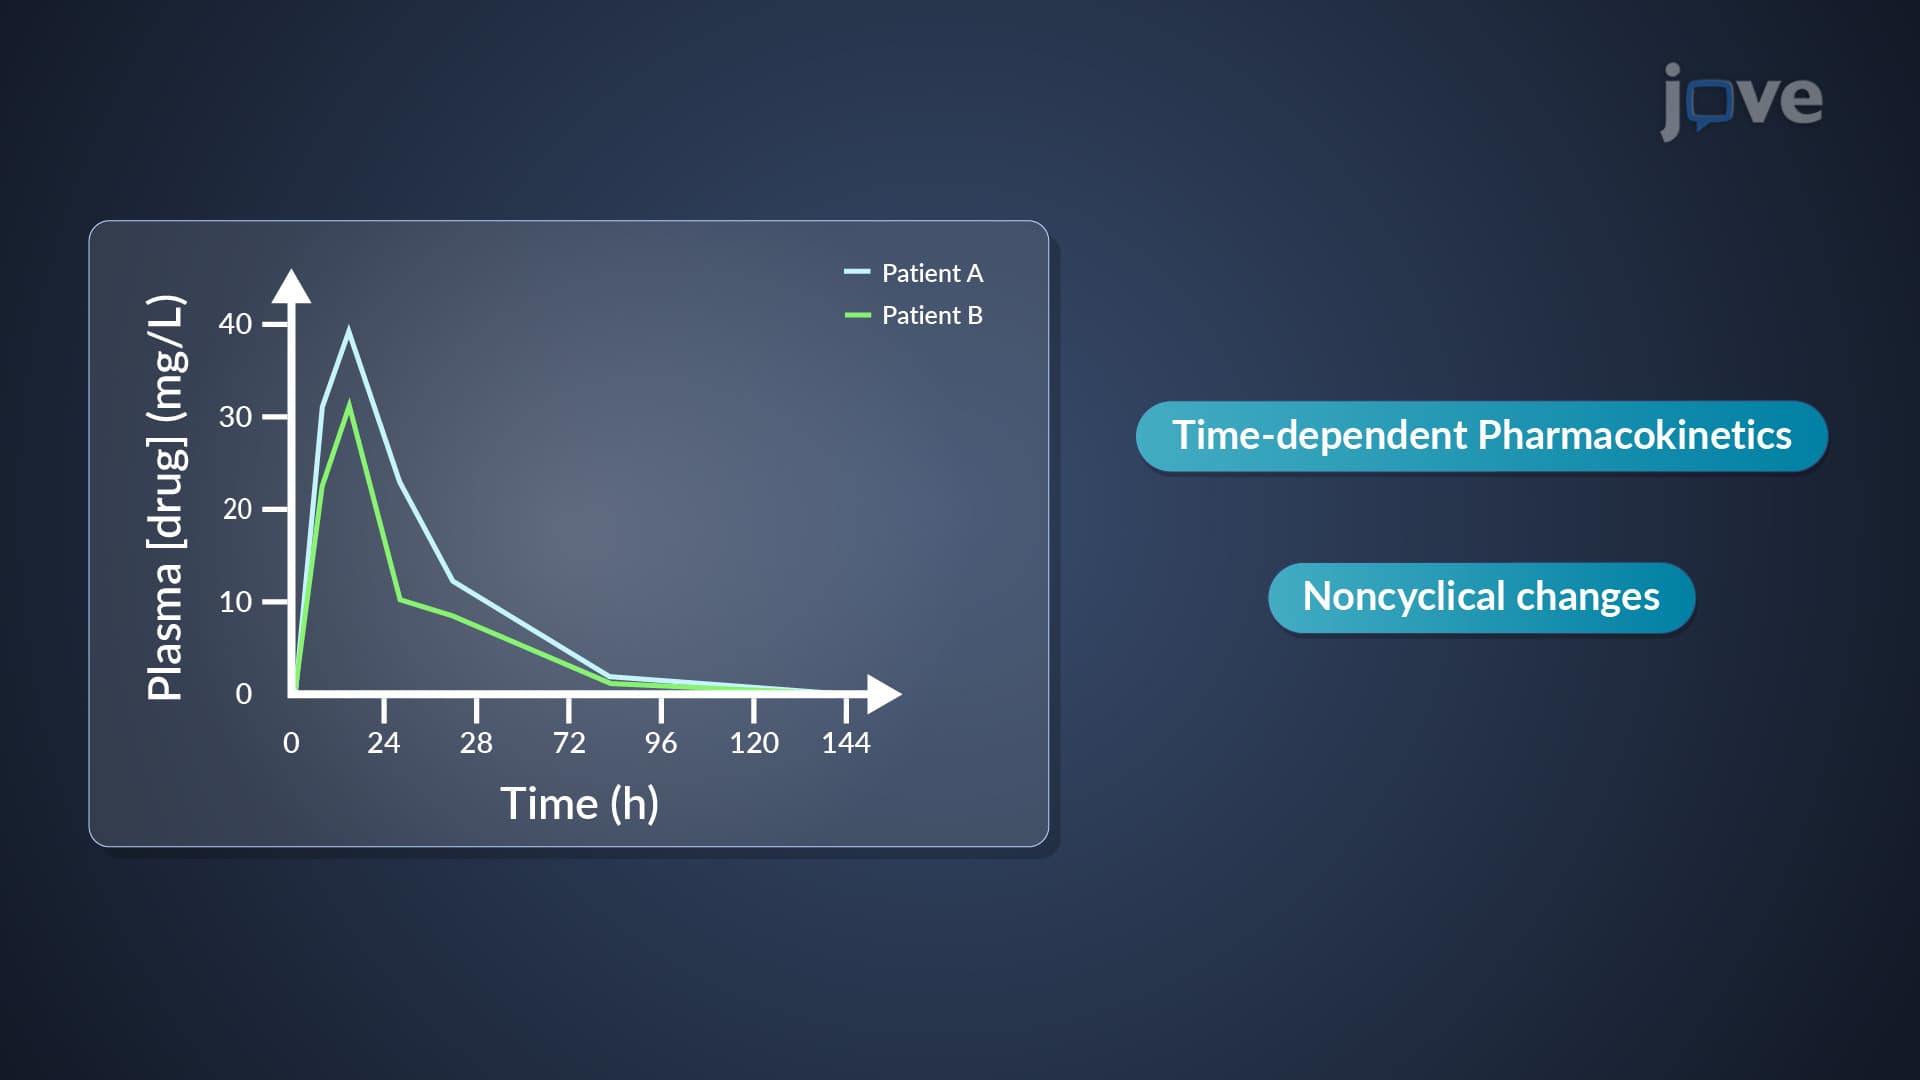
Chronopharmacokinetics: Time-Dependent Pharmacokinetics
Time-dependent pharmacokinetics refers to non-cyclical changes in drug rate processes over a period of time. It can lead to nonlinear pharmacokinetics, where the relationship between drug concentration and time is not proportional. Non-cyclical...