Related Experiment Video
Updated: Sep 29, 2025
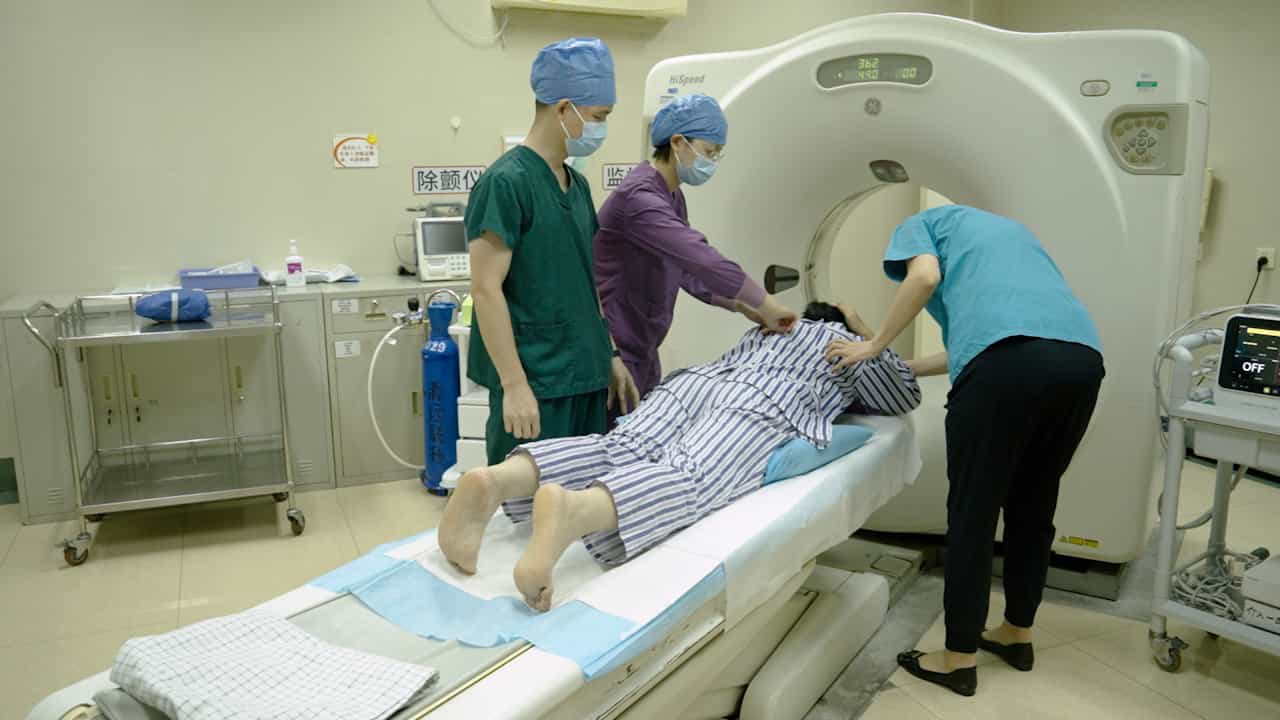
Improved Home Blood Pressure Control by CT-guided Ozone-mediated Renal Denervation for Patients with Resistant Hypertension
Published on: June 6, 2025
Effect of Baseline Antihypertensive Treatments on Stroke Severity and Outcomes in the BP TARGET Trial
Benjamin Maïer1,2,3,4, Benjamin Gory5,6, Bertrand Lapergue7
1Interventional Neuroradiology Department, Hôpital Fondation Ophtalmologique Adolphe de Rothschild, Paris, France (B.M., J.-P.D., R.B., M.P., M.M.).

Background:
Acute ischemic stroke (AIS) patients with a history of hypertension experience worse outcomes, which may be explained by a deleterious impact of the renin-angiotensin system (RAS) overactivation. We sought to investigate whether prestroke antihypertensive treatments (AHT) influenced baseline stroke severity and neurological outcomes, in patients with AIS successfully treated by endovascular therapy.
Methods:
We performed a post hoc analysis of the BP TARGET trial (Blood Pressure Target in Acute Stroke to Reduce Hemorrhage After Endovascular Therapy) and included hypertensive patients with available data regarding AHT at admission, categorized as RAS inhibitors (ACE [angiotensin-converting enzyme] inhibitors, ARBs [angiotensin 2 receptor blockers], and β-blockers) and non-RAS inhibitors (calcium channel blockers and diuretics). Associations of each AHT with National Institutes of Health Stroke Scale (NIHSS) score at baseline were investigated in linear mixed model adjusted for the number of treatments and center. Associations of each AHT with 24-hour NIHSS change, intracranial hemorrhage were performed using linear mixed model adjusted for baseline NIHSS, the number of treatments, center, age, and sex and adjusted for age, sex, diabetes, and current smoking for favorable outcome. All analyses were performed on cases-available data regarding the low number of missing data.
Results:
Overall, 203 patients with at least one AHT were included. Patients under non-RAS inhibitor treatments had a higher NIHSS score at baseline (adjusted mean difference=3.28 [95% CI, 1.33-5.22]; P=0.001). Conversely, patients under RAS inhibitor treatments had a lower baseline NIHSS score (adjusted mean difference=-2.81 [95% CI, -5.37 to -0.25]; P=0.031). Intracranial hemorrhage occurrence was significantly more frequent in patients under non-RAS inhibitor treatments (adjusted odds ratio of 2.48 [95% CI, 1.12-5.47]; P=0.025). Conversely, the use of RAS inhibitor treatments before AIS was not associated with higher odds of radiographic intracranial hemorrhage. Patients with non-RAS inhibitor treatments had less improvement of NIHSS at 24 hours compared with patients without (adjusted mean difference, 2.83 [95% CI, -0.16 to 5.81]; P=0.063). Baseline RAS inhibitor or noninhibitor treatments were not associated with favorable outcome.
Conclusions:
We showed an opposite effect of baseline AHT, based on their effect on the RAS. Patients treated with RAS inhibitor agents before AIS exhibited less severe AIS compared with patients under non-RAS inhibitor treatments, developed less intracranial hemorrhage at 24 hours and had a trend toward better NIHSS score at 24 hours.
Registration:
URL: https://www.
Clinicaltrials:
gov; Unique identifier: NCT03160677.

Related Concept Videos
 01:28
Hypertension IV: Drug Therapy and Lifestyle Modifications
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:18
Treatment for Pulmonary Arterial Hypertension: Endothelin Receptor Antagonists
ETs are synthesized through a complex sequence of enzymatic steps, primarily involving an enzyme referred to as endothelin-converting enzyme...
 01:23
Hypertension V: Nursing Management
 01:22
Heart Failure Drugs: β-Blockers
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System