Related Experiment Video
Updated: Sep 29, 2025


Expired CO2 Measurement in Intubated or Spontaneously Breathing Patients from the Emergency Department
Published on: January 29, 2011
Cardiorespiratory impact of intrathoracic pressure overshoot during artificial carbon dioxide pneumothorax: a
Yunqin Ren1, Xing Zhu1, Hong Yan1
1Department of Anesthesiology, Daping Hospital, Army Medical University, 10 ChangjiangZhilu, Yuzhong District, 400042, Chongqing, China.

Background:
The aim of this study is to evaluate cardiovascular and respiratory effects of intrathoracic pressure overshoot (higher than insufflation pressure) in patients who underwent thoracoscopic esophagectomy procedures with carbon dioxide (CO2) pneumothorax.
Methods:
This prospective research included 200 patients who were scheduled for esophagectomy from August 2016 to July 2020. The patients were randomly divided into the Stryker insufflator (STR) group and the Storz insufflator (STO) group. We recorded the changes of intrathoracic pressure, peak airway pressure, blood pressure, heart rate and central venous pressure (CVP) during artificial pneumothorax. The differences in blood gas analysis, the administration of vasopressors and the recovery time were compared between the two groups.
Results:
We found that during the artificial pneumothorax, intrathoracic pressure overshoot occurred in both the STR group (8.9 mmHg, 38 times per hour) and the STO group (9.8 mmHg, 32 times per hour). The recorded maximum intrathoracic pressures were up to 58 mmHg in the STR group and 51 mmHg in the STO group. The average duration of intrathoracic pressure overshoot was significantly longer in the STR group (5.3 ± 0.86 s) vs. the STO group (1.2 ± 0.31 s, P < 0.01). During intrathoracic pressure overshoot, a greater reduction in systolic blood pressure (SBP) (5.6 mmHg vs. 1.1 mmHg, P < 0.01), a higher elevation in airway peak pressure (4.8 ± 1.17 cmH2O vs. 0.9 ± 0.41 cmH2O, P < 0.01), and a larger increase in CVP (8.2 ± 2.86 cmH2O vs. 4.9 ± 2.35 cmH2O, P < 0.01) were observed in the STR group than in the STO group. Vasopressors were also applied more frequently in the STR group than in the STO group (68% vs. 43%, P < 0.01). The reduction of SBP caused by thoracic pressure overshoot was significantly correlated with the duration of overshoot (R = 0.76). No obvious correlation was found between the SBP reduction and the maximum pressure overshoot.
Conclusions:
Intrathoracic pressure overshoot can occur during thoracoscopic surgery with artificial CO2 pneumothorax and may lead to cardiovascular adverse effects which highly depends on the duration of the pressure overshoot.
Trial Registration:
Clinicaltrials.gov ( NCT02330536 ; December 24, 2014).
More Related Videos
 06:22
Surfactant Depletion Combined with Injurious Ventilation Results in a Reproducible Model of the Acute Respiratory Distress Syndrome ARDS
Published on: April 7, 2021
 08:25
Combining Volumetric Capnography And Barometric Plethysmography To Measure The Lung Structure-function Relationship
Published on: January 8, 2019
Related Concept Videos
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:24
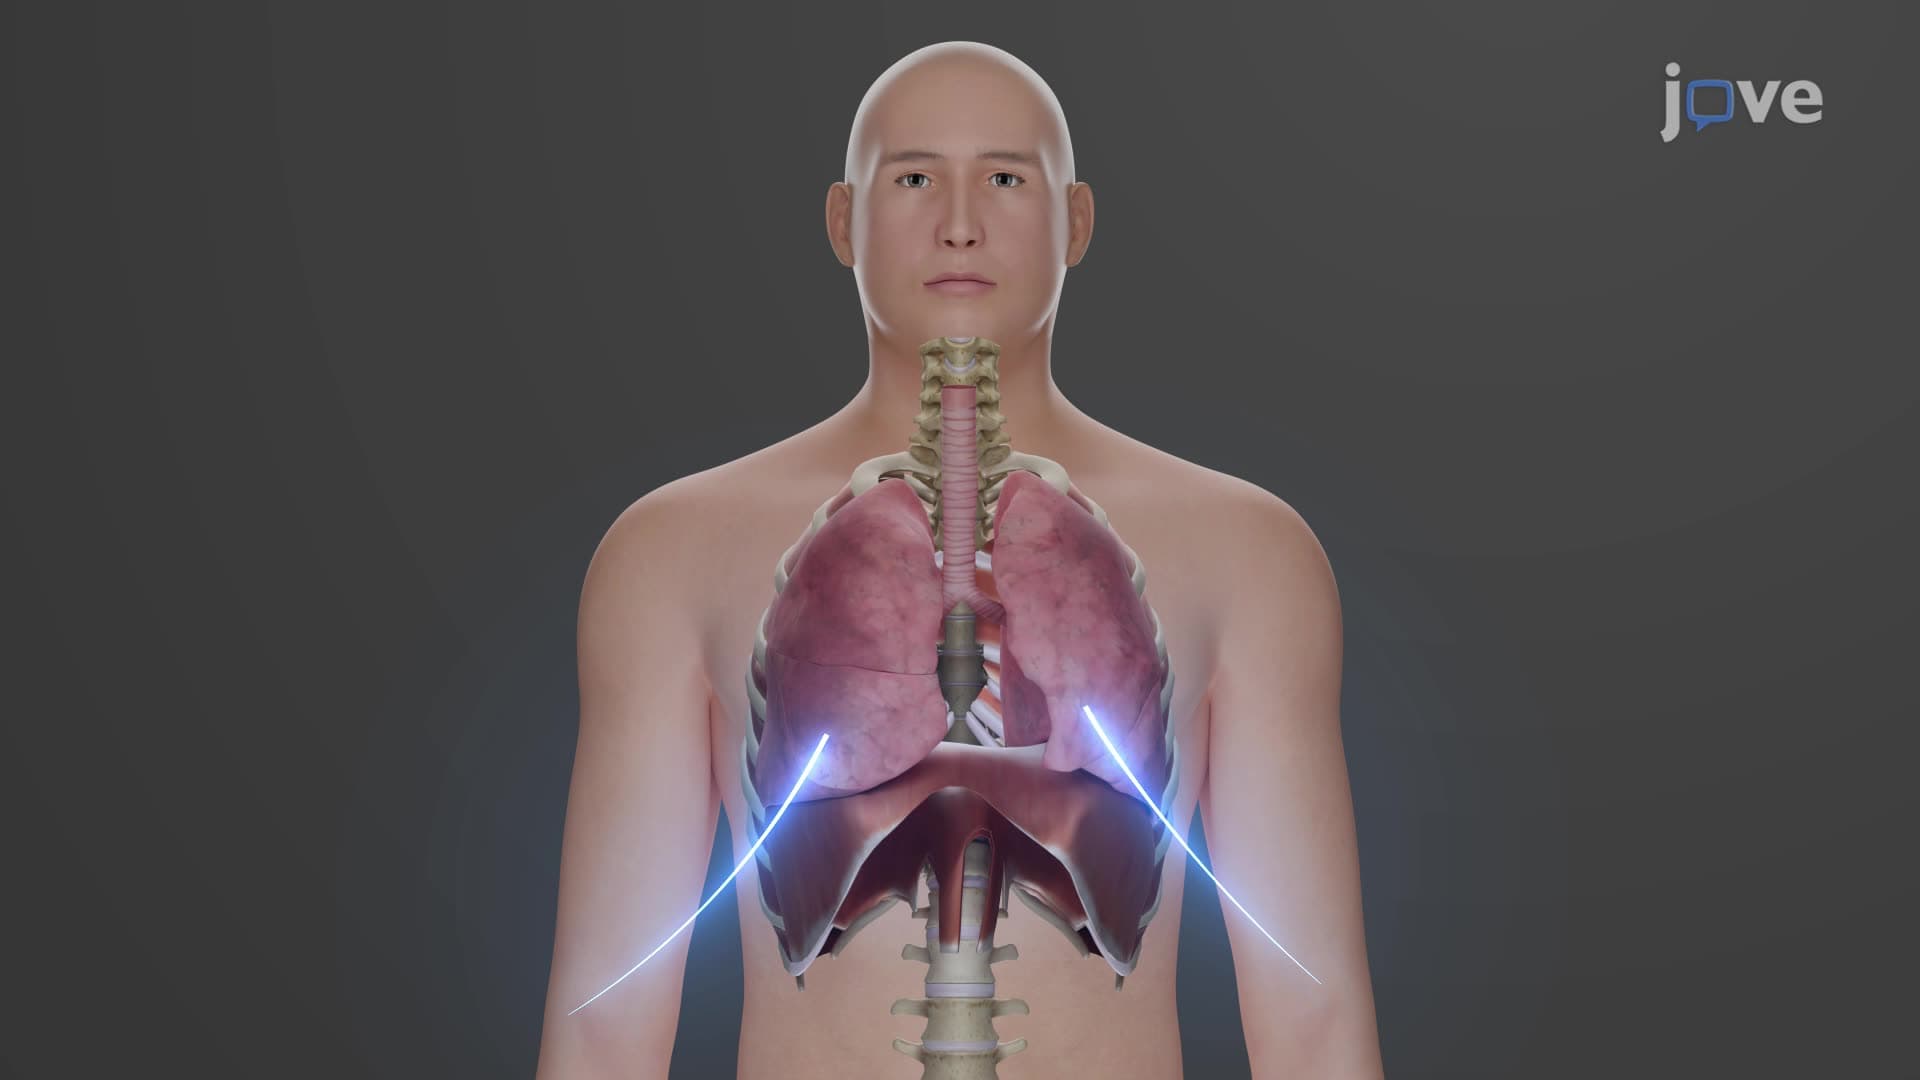
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:24
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...
 01:30
Acute Respiratory Failure-III
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management