Related Experiment Video
Updated: Sep 29, 2025
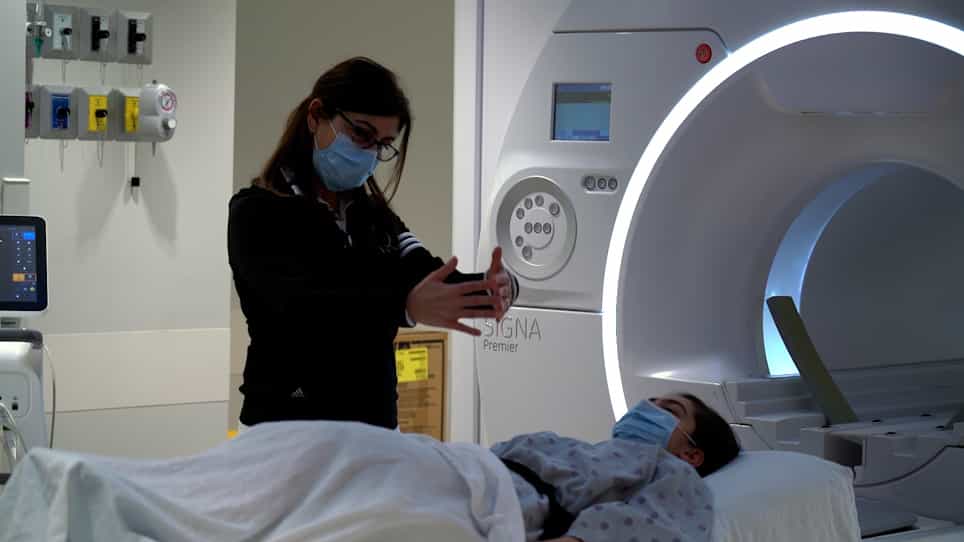

Oxygenation-sensitive Cardiac MRI with Vasoactive Breathing Maneuvers for the Non-invasive Assessment of Coronary Microvascular Dysfunction
Published on: August 17, 2022
Molecular Hallmarks of Ischemia with Non-Obstructive Coronary Arteries: The "INOCA versus Obstructive CCS" Challenge
Alice Bonanni1,2, Alessia d'Aiello1,2, Daniela Pedicino1,2
1Department of Cardiovascular and Pulmonary Sciences, Catholic University of the Sacred Heart, 00168 Rome, Italy.

Insights
Patients with Ischemia with Non-Obstructive Coronary Arteries (INOCA) show distinct gene expression profiles compared to obstructive coronary artery disease (ObCCS). Identifying these molecular hallmarks may enable early, non-invasive differential diagnosis for improved patient care.
Area of Science:
- Cardiology
- Molecular Biology
- Genomics
Background:
- Myocardial ischemia affects millions, with many lacking obstructive coronary artery disease (CAD).
- Current diagnostic and treatment guidelines for non-obstructive CAD are lacking, necessitating research into non-invasive tools.
- Understanding the biological differences in Ischemia with Non-Obstructive Coronary Arteries (INOCA) is crucial for advancing patient management.
Purpose of the Study:
- To compare the gene expression profiles of INOCA patients with microvascular dysfunction against patients with obstructive chronic coronary syndrome (ObCCS).
- To identify specific molecular hallmarks that differentiate INOCA from ObCCS.
- To explore potential non-invasive diagnostic biomarkers for these conditions.
Main Methods:
- Gene expression arrays were performed on peripheral blood mononuclear cells (PBMCs).
- PBMCs were isolated from two patient groups: INOCA (n=18) and ObCCS (n=20).
- Differential gene expression analysis was conducted to identify significant molecular variations.
Main Results:
- INOCA patients exhibited significantly reduced expression of genes involved in cell adhesion, signaling, vascular motion, and inflammation compared to ObCCS patients.
- Specific molecules with lower expression in INOCA included CD31, ICAM1, TNF, TFRC, and VEGFA.
- Conversely, INOCA patients showed increased expression of Hyaluronidase (HYAL2) compared to the ObCCS group.
Conclusions:
- Distinct molecular biomarker profiles exist between INOCA and ObCCS patients.
- These molecular differences offer potential for early and non-invasive differential diagnosis.
- Identifying these hallmarks can improve clinical management and treatment strategies within personalized medicine.
Abstract:
Up to 4 million patients with signs of myocardial ischemia have no obstructive coronary artery disease (CAD). The absence of precise guidelines for diagnosis and treatment in non-obstructive CAD encourages the scientific community to fill the gap knowledge, to provide non-invasive and less expensive diagnostic tools. The aim of our study was to explore the biological profile of Ischemia with Non-Obstructive Coronary Arteries (INOCA) patients with microvascular dysfunction compared to patients presenting with obstructive chronic coronary syndrome (ObCCS) in order to find specific hallmarks of each clinical condition. We performed a gene expression array from peripheral blood mononuclear cells (PBMCs) isolated from INOCA (n = 18) and ObCCS (n = 20) patients. Our results showed a significantly reduced gene expression of molecules involved in cell adhesion, signaling, vascular motion, and inflammation in INOCA as compared to the ObCCS group. In detail, we found lower expression of Platelet and Endothelial Cell Adhesion Molecule 1 (CD31, p < 0.0001), Intercellular Adhesion Molecule-1 (ICAM1, p = 0.0004), Tumor Necrosis Factor (TNF p = 0.0003), Transferrin Receptor (TFRC, p = 0.002), and Vascular Endothelial Growth Factor A (VEGFA, p = 0.0006) in the INOCA group compared with ObCCS. Meanwhile, we observed an increased expression of Hyaluronidase (HYAL2, p < 0.0001) in INOCA patients in comparison to ObCCS. The distinct expression of molecular biomarkers might allow an early and non-invasive differential diagnosis between ObCCS and INOCA, improving clinical management and treatment options, in the era of personalized medicine.
More Related Videos
 09:36
A Magnetic Resonance Imaging-based Computational Protocol for Analysis of Plaque Morphology and Hemodynamics in Patients with Carotid Artery Stenosis
Published on: August 12, 2025
 13:07
Optical Coherence Tomography Based Biomechanical Fluid-Structure Interaction Analysis of Coronary Atherosclerosis Progression
Published on: January 15, 2022
Related Concept Videos
 01:17
Ischemic Heart Disease: Overview
Atherosclerosis, the primary malefactor, orchestrates this dangerous condition. It manifests as the accumulation of fatty deposits, akin to insidious plaques, within arterial walls. As time elapses, these plaques metamorphose, hardening and...
 01:26
Coronary Artery Disease II: Pathophysiology
 01:30
Coronary Artery Disease III: Clinical Manifestations
 01:30
Coronary Artery Disease I: Introduction
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:30
Acute Coronary Syndrome I: Introduction