
Is Pelvic Floor Muscle Tenderness a Distinct Urologic Chronic Pelvic Pain Syndrome Phenotype? Findings from the
Priyanka Gupta1, Robert Gallop2, Theresa Spitznagle3
1Department of Urology, University of Michigan, Ann Arbor, Michigan.

Purpose:
Of women with interstitial cystitis/bladder pain syndrome and men with chronic prostatitis/chronic pelvic pain syndrome 85% have concomitant pelvic floor muscle tenderness (PFT). The significance of this finding is incompletely understood. This study examines PFT among participants in the MAPP (Multidisciplinary Approach to the Study of Chronic Pelvic Pain) Research Network and its relationship with urologic chronic pelvic pain syndrome (UCPPS) symptom severity in order to determine whether this is a phenotypic predictor in UCPPS.
Materials And Methods:
Participants in the MAPP Network Symptom Patterns Study underwent a standardized pelvic examination (PEX). Trained examiners palpated 6 locations evaluating the pelvic musculature for PFT. Participants were assigned a 0 to 6 PEX score based on the number of areas with tenderness on PEX. Using regression tree models, PEX scores were divided into low (0, 1), mid (2, 3, 4, 5) and high (6). The relationship between PFT and UCPPS symptoms was examined using several validated questionnaires.
Results:
The study cohort consisted of 562 UCCPS participants (375 females and 187 males) and 69 controls. Diagnoses included interstitial cystitis/bladder pain syndrome (397), chronic prostatitis/chronic pelvic pain syndrome (122), both (34) or no diagnosis (9). Of UCPPS participants 81% had PFT on PEX compared to 9% of controls: 107 (19%) low, 312 (56%) mid and 143 (25%) high. Participants with higher PFT scores had more severe disease burden (worse pelvic pain and urinary symptoms), worse quality of life and more widespread distribution of nonpelvic pain.
Conclusions:
UCPPS patients with more widespread PFT have severe pain and urinary symptoms, worse quality of life and a more centralized pain phenotype.
Related Concept Videos
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:26
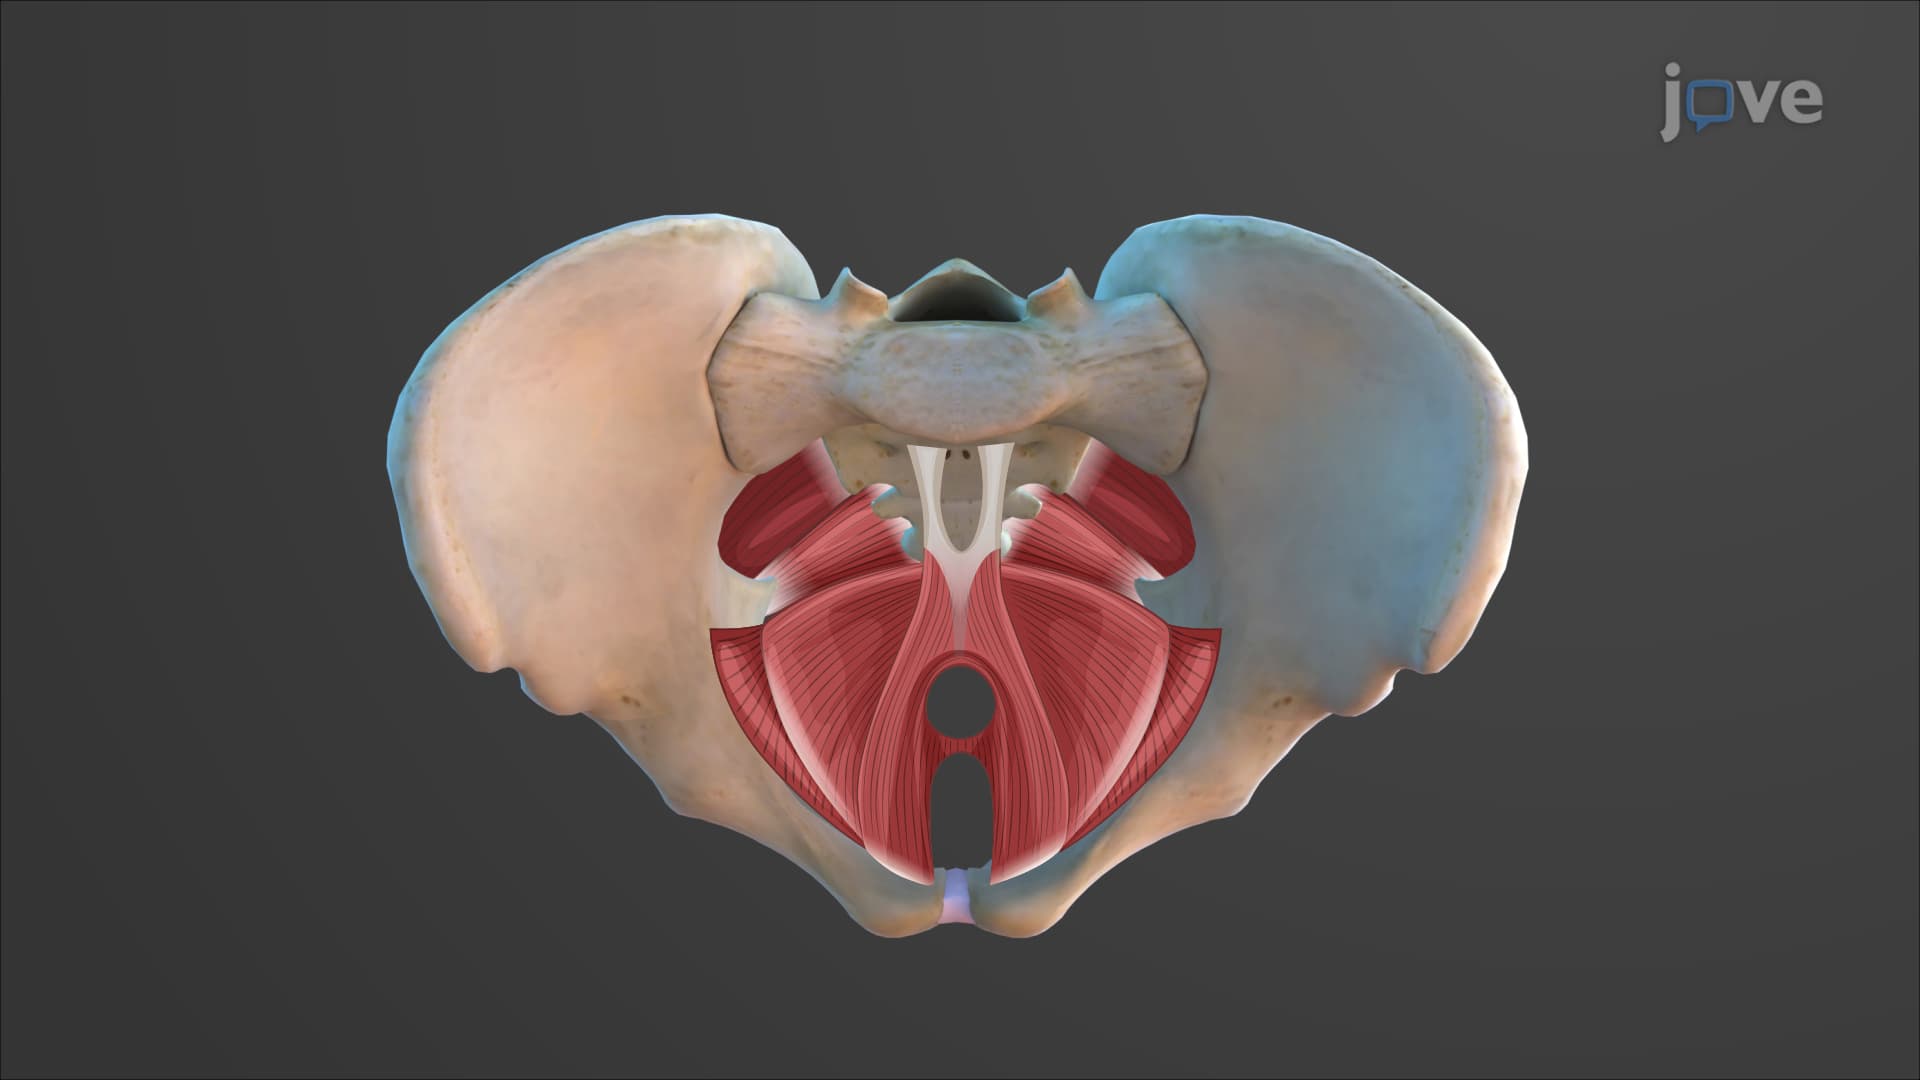
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:26
Nursing Assessment of the Genitourinary System II: Inspection and Palpation
 01:30
Irritable Bowel Syndrome II: Clinical Features and Diagnostic Evaluation
Irritable Bowel Syndrome (IBS) is classified into subtypes based on the predominant bowel habits as determined by the Bristol Stool Form Scale (BSFS). The subtypes are:
 01:19
Abdominal Regions and Quadrants
The simpler quadrants approach, which is more commonly used in medicine, subdivides the cavity with one horizontal and one vertical line that intersects at the patient's umbilicus (navel). The four...