Related Experiment Video
Updated: Sep 28, 2025


Establishment of an Extracellular Acidic pH Culture System
Published on: November 19, 2017
Influence of Medications Containing Acid Salts on Serum Bicarbonate in CKD
John Gardner1, Kunani Tuttle2, Kalani L Raphael2,3
1Pharmacy Section, Veterans Affairs Salt Lake City Healthcare System, Salt Lake City, Utah.

Background:
Many medications are formulated with acid salts. Their effect on acid-base balance in CKD is unclear.
Methods:
We calculated the acid load (meq/d) from medications prescribed to 74 United States veterans with diabetes and CKD to identify agents with high potential acid load. We also determined cross-sectional associations between the acid load from medications and acid-base parameters after adjusting for demographics, eGFR, protein intake, and other confounders.
Results:
Of the 125 medications prescribed, 31 (25%) contained an acid salt. Metformin hydrochloride (15.4 meq/d at 2550 mg/d) and gabapentin hydrochloride (13.0 meq/d at 2700 mg/d) were identified as agents with a high potential acid load. Mean daily acid load from medications was 6.6 meq/d in the overall cohort, 14.2 meq/d in the high medication acid load group (≥7.7 meq/d, n=29), and 1.6 meq/d in the low medication acid load group (<7.7 meq/d, n=45). After adjusting for potential confounders, those in the high acid load group had 1.7 meq/L lower total carbon dioxide (CO2) and 2.2 meq/L higher anion gap than those in the low acid load group. Use of gabapentin alone was not associated with differences in total CO2 or anion gap. Use of metformin alone was associated with 0.7 meq/L lower total CO2 and 1.0 meq/L higher anion gap. Use of metformin with gabapentin was associated with 1.8 meq/L lower total CO2 and 2.4 meq/L higher anion gap. The higher anion gap was not explained by higher serum lactate levels. The acid load from medications was not associated with differences in urinary ammonium, titratable acid, or pH.
Conclusions:
Medications containing acid salts, particularly metformin hydrochloride and gabapentin hydrochloride, are sources of an exogenous acid load. These agents may influence serum total CO2 levels and serum anion gap in individuals with CKD.
Clinical Trial Registry Name And Registration Number:
Investigations of the Optimum Serum Bicarbonate Level in Renal Disease, NCT01574157.


Related Concept Videos
 01:29
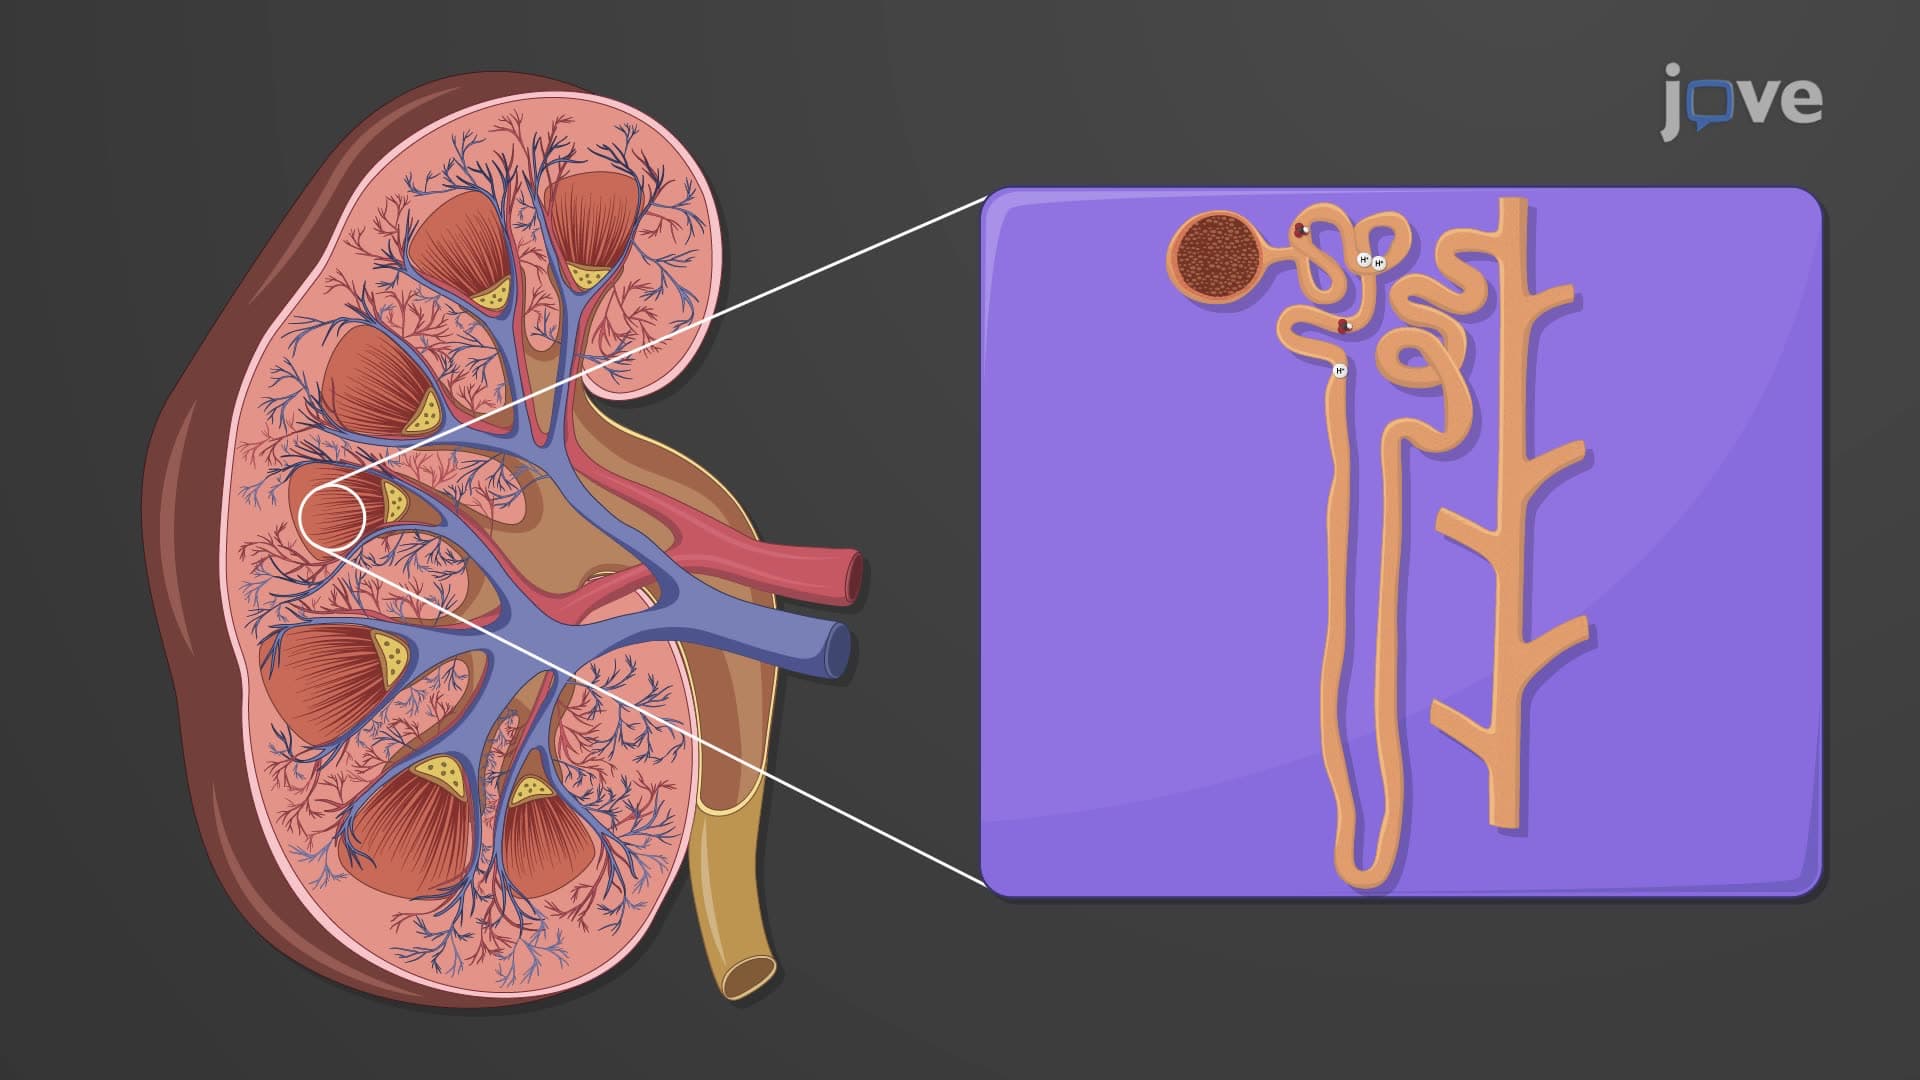
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:22
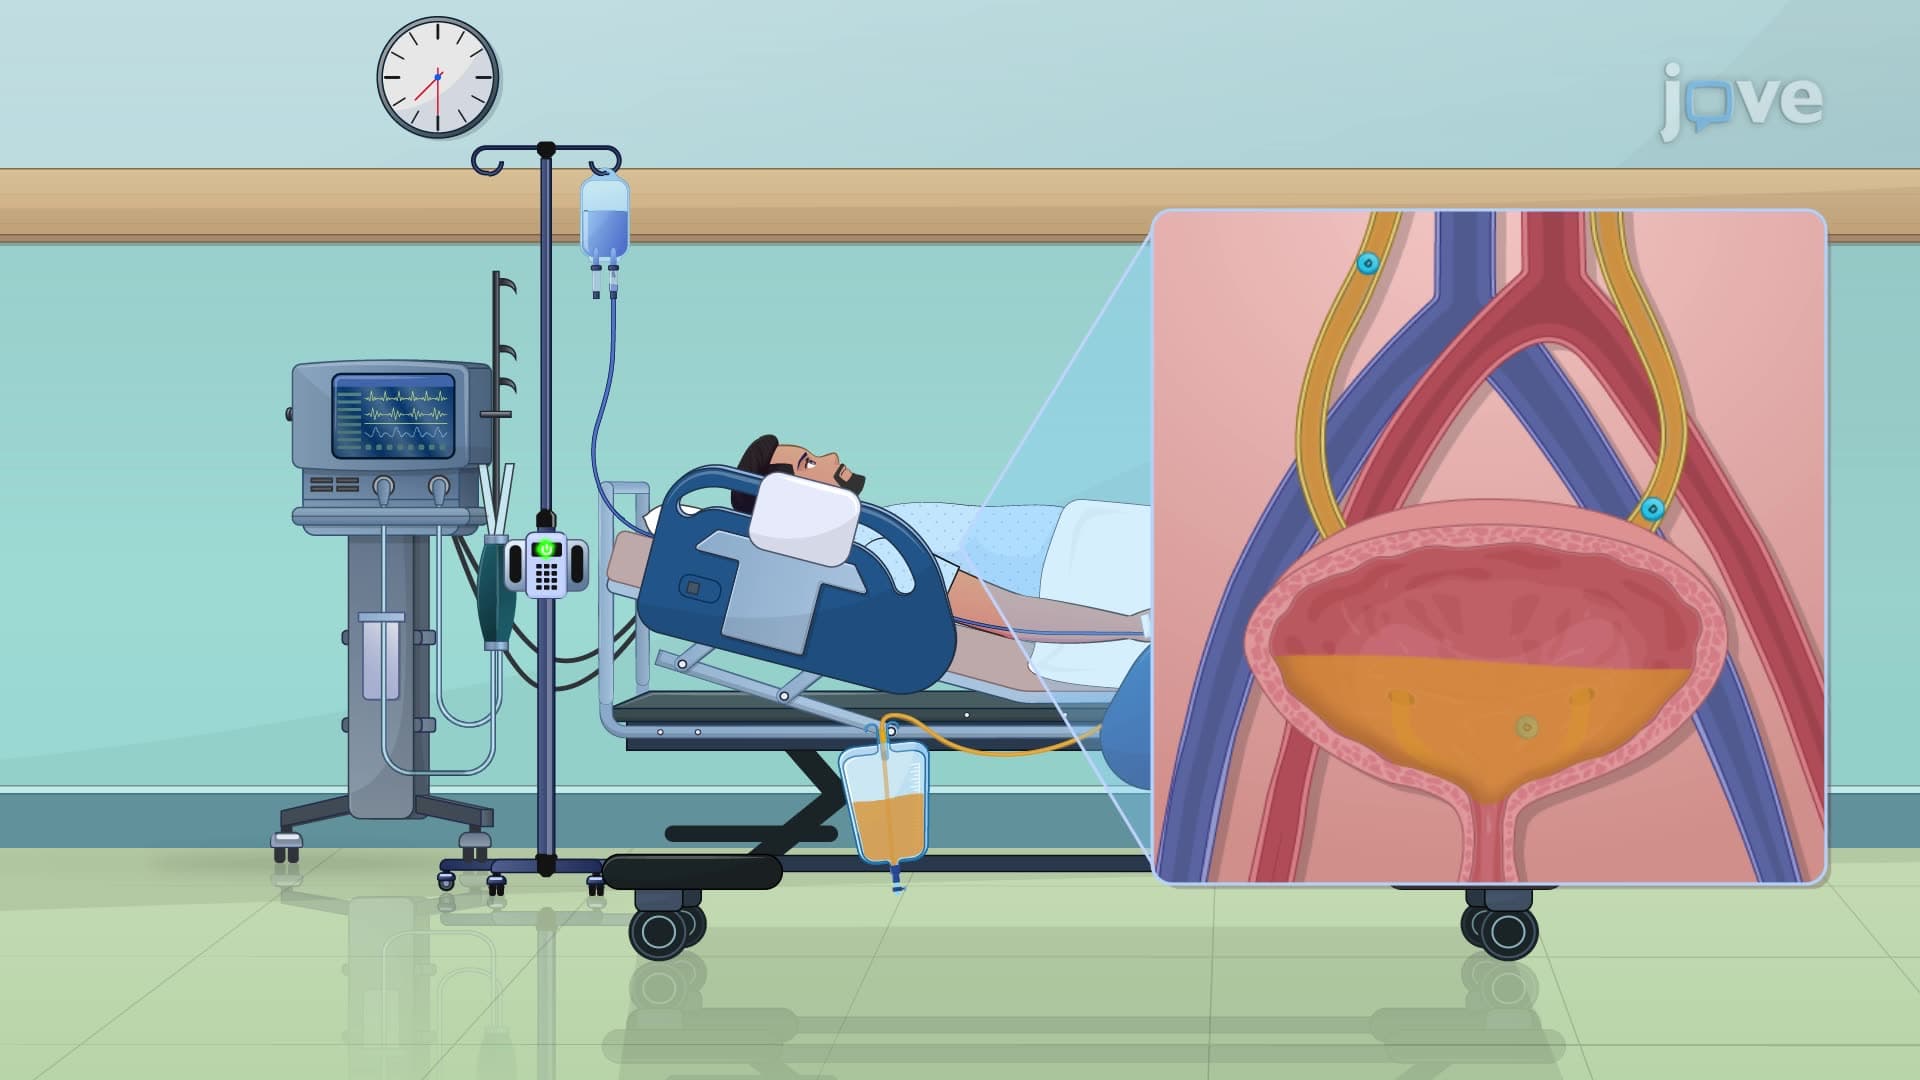
Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa
The pKa of a...
 01:22
Bicarbonate-Carbonic Acid Buffer
 01:31
Acid Suppressive Drugs for Peptic Ulcer Disease: Antacids
However, this neutralization reaction between...
 01:29
Roles of Electrolytes: Chloride and Bicarbonate
Conditions such as hypochloremia can arise from insufficient chloride reabsorption by the kidneys, often compounded by extended bouts of diarrhea, vomiting,...
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and...