Related Experiment Video
Updated: Sep 28, 2025

07:37

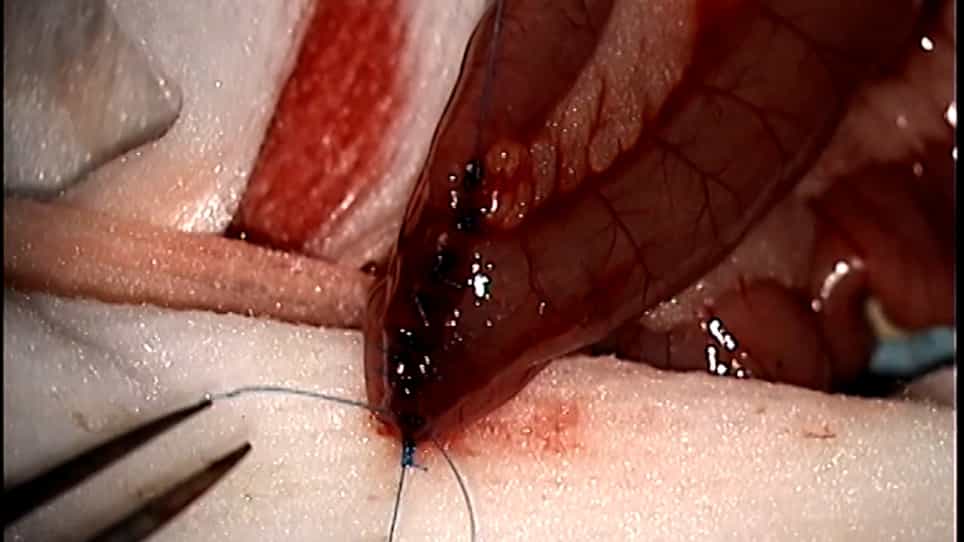
Roux-en-Y Gastric Bypass Operation in Rats
Published on: June 11, 2012
23.7K
Postprandial Hyperinsulinemic Normoglycemic Hypokalemia Response After Roux-en-Y Gastric Bypass Surgery
Arvo Haenni1,2, Inger Nilsen3,4,5
1Bariatric Clinic, Department of Surgery, Falun Hospital, Falun, Sweden. arvo.hanni@pubcare.uu.se.
Obesity Surgery
|April 5, 2022

Abstract
No abstract available in PubMed .

Related Concept Videos
 01:15
Hypoglycemia and Glucagon
363
Without prolonged fasting, healthy individuals maintain blood glucose levels above 3.5 mM due to a well-adapted neuroendocrine counterregulatory system that effectively prevents acute hypoglycemia, a potentially life-threatening condition. The primary clinical scenarios for hypoglycemia encompass diabetes treatment, inappropriate production of endogenous insulin or insulin-like substances by tumors, and the use of glucose-lowering agents in non-diabetic individuals. Notably, hypoglycemia in the...
363
 01:16
Insulin: Dosing Regimen and Adverse Effects
285
Insulin-replacement therapy usually includes both long-acting insulin (basal) and short-acting insulin (to cater to postprandial needs). In a diverse group of type 1 diabetes patients, the average daily insulin dose is typically 0.5-0.7 units/kg body weight. However, obese patients and pubertal adolescents may need more due to insulin resistance.
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
285
 01:18
Metabolic States of the Body: The Postabsorptive State
630
The postabsorptive state usually starts about four hours after a meal and lasts until the next meal is eaten. During this time, the digestive system stops absorbing nutrients, and the body uses stored energy reserves to maintain stable blood glucose levels.
Initially, glycogen stored in the liver is broken down to release glucose into the bloodstream, while glycogen in the muscles is broken down to supply glucose for energy directly within the muscle cells. As glycogen stores diminish,...
Initially, glycogen stored in the liver is broken down to release glucose into the bloodstream, while glycogen in the muscles is broken down to supply glucose for energy directly within the muscle cells. As glycogen stores diminish,...
630
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
1.5K
The pancreatic islets comprising only 1%-2% of the volume are highly vascularized and innervated mini-organs. They contain five endocrine cell types, including β cells that secrete insulin, which is synthesized as a single polypeptide chain, preproinsulin, processed to proinsulin, and finally to insulin and C-peptide. This process is complex and regulated, involving the Golgi complex, the endoplasmic reticulum, and the secretory granules of the β cell.
Insulin and C-peptide are...
Insulin and C-peptide are...
1.5K
 01:24
Glucagon-like Receptor Agonists
451
Incretins include glucagon-like peptide-1 (GLP-1) and glucose-dependent insulinotropic polypeptide (GIP), which stimulate insulin secretion post-meals. In type 2 diabetes, GIP's efficacy is reduced, making GLP-1 a viable drug target. GIP originates from preproGIP.
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by...
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by...
451
 01:06
Oral Hypoglycemic Agents: Glinides
283
Repaglinide (Prandin) and Nateglinide (Starlix), known as glinides, are oral insulin secretagogues that stimulate insulin release from pancreatic β cells by closing the ATP-sensitive potassium channels (KATP channel). Repaglinide controls insulin release from pancreatic β cells by managing potassium efflux. It shares two binding sites with sulfonylureas and also has a unique site, indicating overlapping mechanisms of action. With a rapid onset and a 4-7 hour duration, it effectively...
283