Related Experiment Video
Updated: Sep 27, 2025
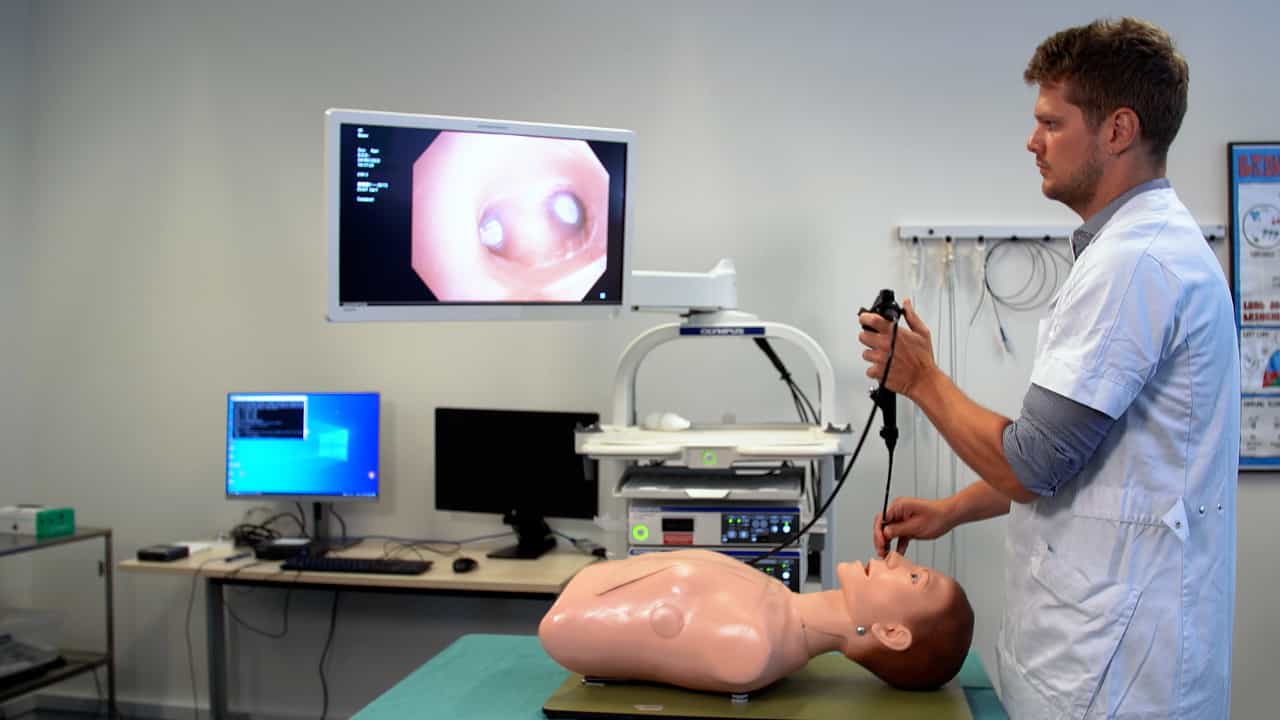

Author Spotlight: Learning Systematic Bronchoscopy in a Simulation-Base Setting
Published on: June 23, 2023
Profiling Bispebjerg Acute Cohort: Database Formation, Acute Contact Characteristics of a Metropolitan Hospital, and
Rasmus Gregersen1,2, Cathrine Fox Maule3, Henriette Husum Bak-Jensen2
1Department of Emergency Medicine, Copenhagen University Hospital - Bispebjerg and Frederiksberg, Copenhagen, Denmark.

Purpose:
To present a metropolitan cohort, Bispebjerg acute cohort (BAC), and compare patient characteristics and outcomes with patients from urban and rural hospitals in Denmark.
Patients And Methods:
We linked data from seven Danish nationwide registries and included all acute contacts to non-psychiatric hospitals in the years 2016-2018. Acute hospital contacts to Bispebjerg and Frederiksberg Hospital constituted BAC, representing a solely metropolitan/urban catchment area. Patient characteristics and outcomes were compared to the rest of Denmark in an urban cohort (UrC) and a rural cohort (RuC), stratified by visit and hospitalization contact types.
Results:
We identified 4,063,420 acute hospital contacts in Denmark and BAC constituted 8.4% (n=343,200) of them. BAC had a higher proportion of visits (65.1%) compared with UrC (52.1%) and RuC (45.3%). Patients in BAC more often lived alone (visits: BAC: 34.8%, UrC: 30.6%, RuC: 29.2%; hospitalizations: BAC: 50.8%, UrC: 36.7%, RuC: 37.2%) and had temporary CPR number (visits: BAC: 4.4%, UrC: 1.9%, RuC: 1.6%; hospitalizations: BAC: 1.5%, UrC: 0.9%, RuC: 0.8%). Visit patients in BAC were younger (BAC: 36, UrC: 42, RuC: 45 years, median), more often students (BAC: 18.0%, UrC: 14.0%, RuC: 12.5%), and had more contacts due to infectious diseases (BAC: 19.8%, UrC: 14.1%, RuC: 6.2%) but less due to injuries (BAC: 40.0%, UrC: 43.8%, RuC: 60.7%). Hospitalized patients in BAC had higher median age (BAC: 64, UrC: 61, RuC: 64 years) and fewer were in employment than in UrC (BAC: 26.1%, UrC: 32.1%, RuC: 28.1%). BAC Hospitalizations had a lower death rate within 30 days than in RuC (BAC: 3.0% [2.9-3.1%], UrC: 3.1% [3.0-3.1%], RuC: 3.4% [3.3-3.4%]), but a higher readmission-rate (BAC: 20.5% [20.3-20.8%], UrC: 17.3% [17.2-17.4%], RuC: 17.5% [17.5-17.6%]).
Conclusion:
Significant differences between BAC, urban, and rural cohorts may be explained by differences in healthcare structure and sociodemographics of the catchment areas.
More Related Videos
 09:33
Visualizing Field Data Collection Procedures of Exposure and Biomarker Assessments for the Household Air Pollution Intervention Network Trial in India
Published on: December 23, 2022
 06:55
Inverse Probability of Treatment Weighting Propensity Score using the Military Health System Data Repository and National Death Index
Published on: January 8, 2020
Related Concept Videos
 01:29
Bias in Epidemiological Studies
 01:26
Introduction to Epidemiology
 01:08
Data Collection by Observations
An astronomer viewing the motion and brightness of stars in the sky and recording the data is an example of observational data collection. A botanist recording...
 01:25
Statistical Methods for Analyzing Epidemiological Data
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...