Related Experiment Video
Updated: Aug 7, 2026


Quantification of the Immunosuppressant Tacrolimus on Dried Blood Spots Using LC-MS/MS
Published on: November 8, 2015
Case Report: Therapeutic Drug Monitoring of Polymyxin B During Continuous Renal Replacement Therapy in Two Pediatric
Caifang Xu1, Xiaofen Liu2,3, Yun Cui1
1Department of Critical Care Medicine, Shanghai Children's Hospital, Shanghai Jiao Tong University School of Medicine, Shanghai, China.

Insights
Polymyxin B dosing requires adjustment in critically ill children on continuous renal replacement therapy (CRRT). High drug clearance during CRRT necessitates increased polymyxin B doses for effective infection control.
Area of Science:
- Pharmacology
- Nephrology
- Critical Care Medicine
Background:
- Polymyxin B is a last-resort antibiotic for carbapenem-resistant bacterial infections.
- Optimal dosing strategies for polymyxin B in pediatric patients undergoing continuous renal replacement therapy (CRRT) are not well-established.
- Carbapenem-resistant organism bloodstream infections pose a significant challenge in critically ill pediatric populations.
Observation:
- Two pediatric cases with acute kidney injury requiring CRRT were treated with polymyxin B for carbapenem-resistant infections.
- Therapeutic drug monitoring (TDM) using LC-MS/MS guided dose adjustments.
- Initial doses of 1 mg/kg every 12 hours resulted in sub-target plasma concentrations.
Findings:
- Escalating doses to 2 mg/kg every 12 hours achieved target average steady-state concentrations (2.60 and 1.73 mg/L) and controlled infections.
- Polymyxin B demonstrated high clearance during CRRT (45-51%), with significantly lower concentrations compared to post-CRRT periods.
- Individual patient responses and drug exposure varied between CRRT and non-CRRT phases.
Implications:
- CRRT significantly increases polymyxin B clearance in pediatric patients.
- Adjusted or 'supplanted' dosing regimens are crucial for achieving therapeutic polymyxin B levels during CRRT.
- TDM is essential for optimizing polymyxin B therapy in critically ill children with renal replacement therapy.
Abstract:
Background: Polymyxin B has become the last choice for patient with carbapenem-resistant bacterial infection. However, the optimal dosing of polymyxin B in critically ill children receiving continuous renal replacement therapy (CRRT) remains unclear. Case Presentation: Two cases of critically ill pediatric patients (7 years old) with acute kidney injury requiring continuous renal replacement (CRRT) received polymyxin B treatment due to carbapenem-resistant organism bloodstream infections. Therapeutic drug monitoring (TDM) of polymyxin B was carried out by liquid chromatography tandem mass spectrometry (LC-MS/MS). The average steady-state plasma concentration (Css,avg) of 2-4 mg/L was set as the target level. Initial polymyxin B dose was 1 mg/kg every 12 h, and the Css,avg at 4-5th dosing were 1.76 and 1.06 mg/L for patient 1 and patient 2, respectively. TDM-guided polymyxin B dose was escalated to 2 mg/kg every 12 h for both patients, resulting in the Css,avg of 2.60 and 1.73 mg/L, and the infection was controlled subsequently. Css,avg of polymyxin B with the same dosing regimens and infusion length were different during CRRT and after termination of CRRT for both patients (2.60 mg/L vs. 4.94 mg/L with 2 mg/kg every 12 h in 2 h infusion for patient 1; and 1.73 mg/L vs. 3.53 mg/L with 2 mg/kg every 12 h in 2 h infusion for patient 2). The estimation of drug exposure (estimated by AUCss,12h at the same dose) during CRRT and cessation of CRRT showed that 45% and 51% of polymyxin B was cleared during CRRT. Conclusion: Our study showed high clearance of polymyxin B through CRRT, and supplanted dosing of polymyxin B is necessary in pediatric patients undergoing CRRT.


Related Concept Videos
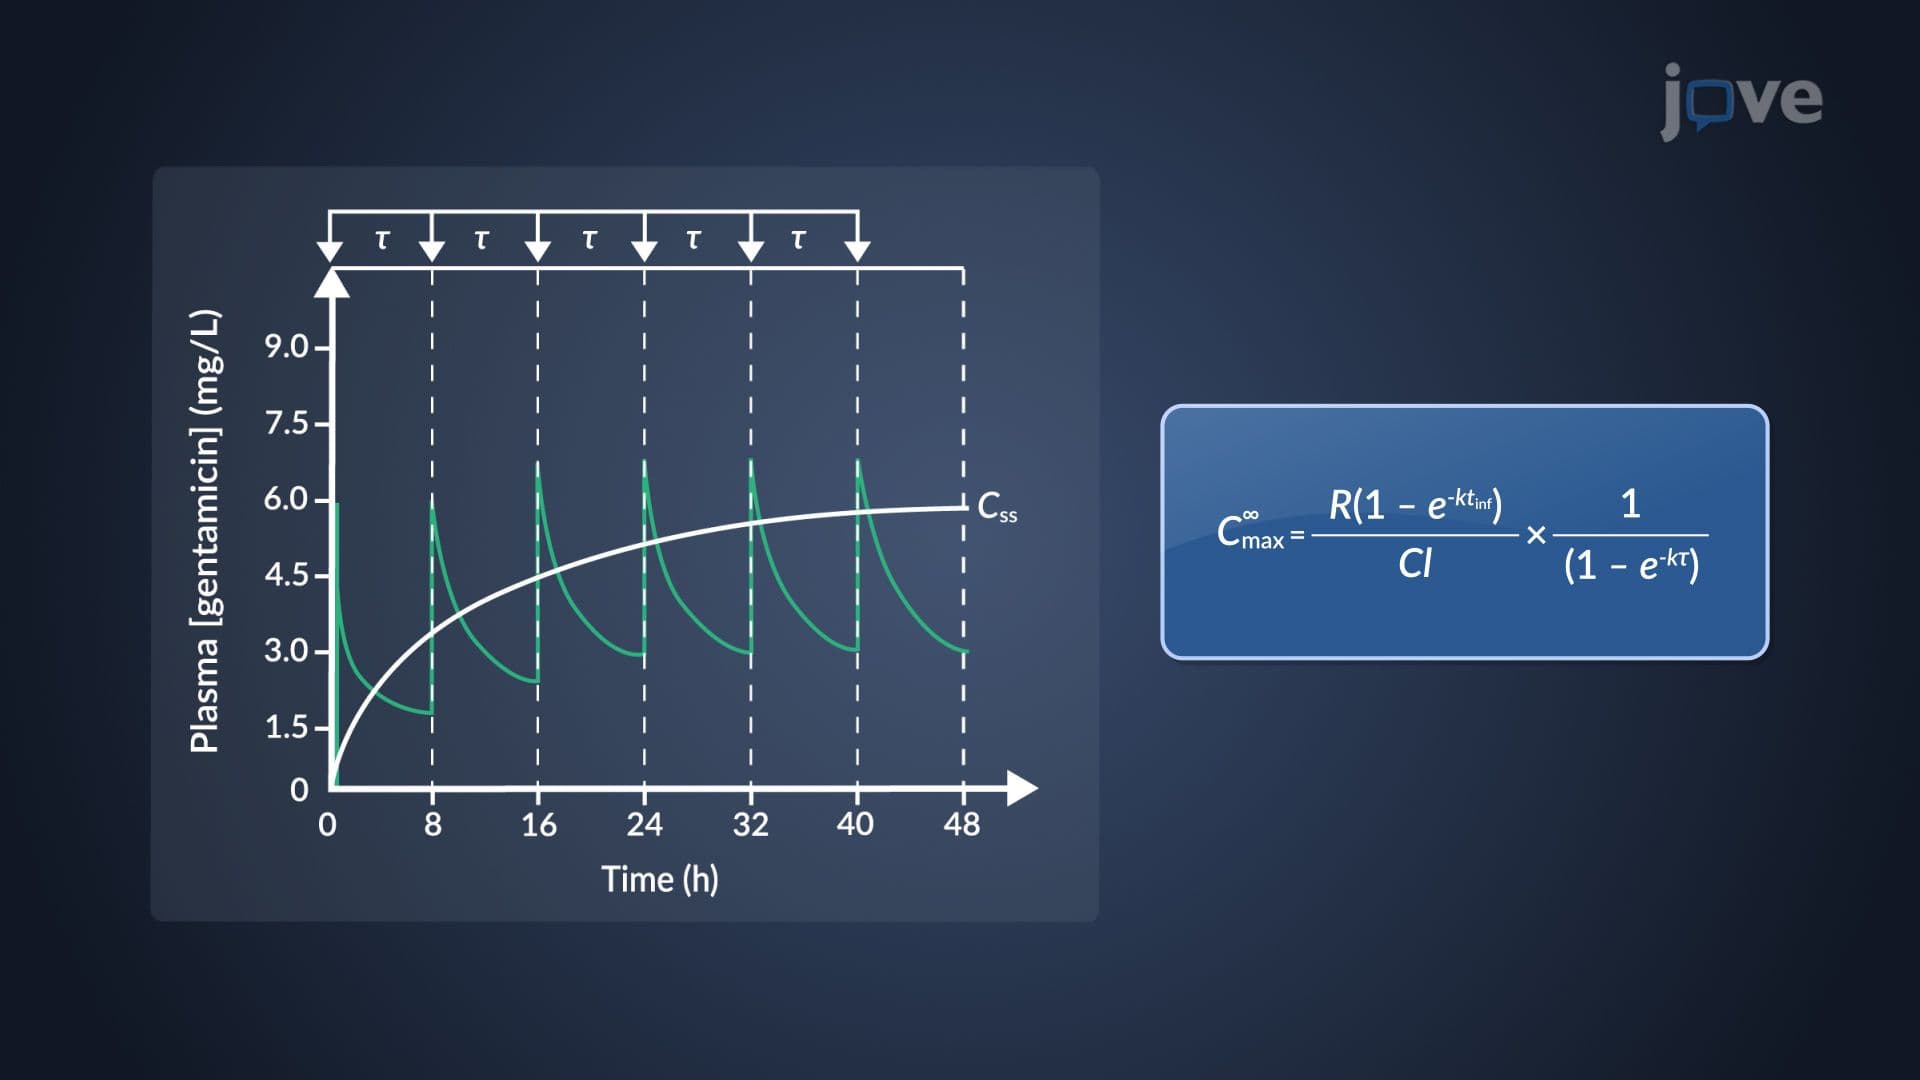 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:25
Drug Dosing in Renal Diseases: Measurement of Serum Creatinine Concentration and Clearance
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:30
Continuous Renal Replacement Therapy